
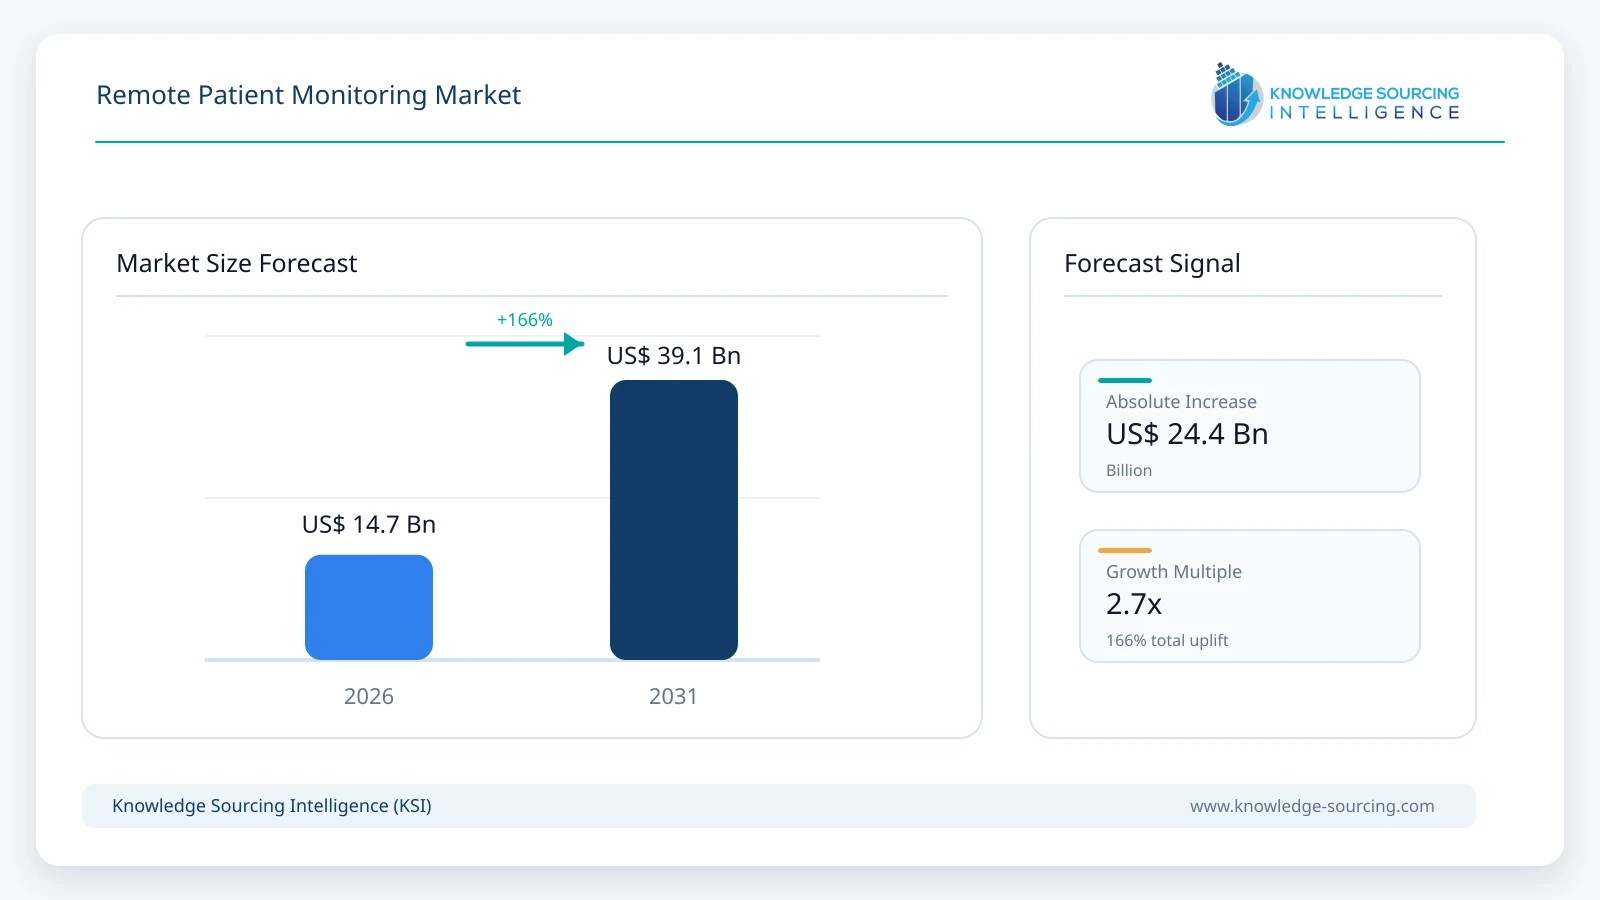
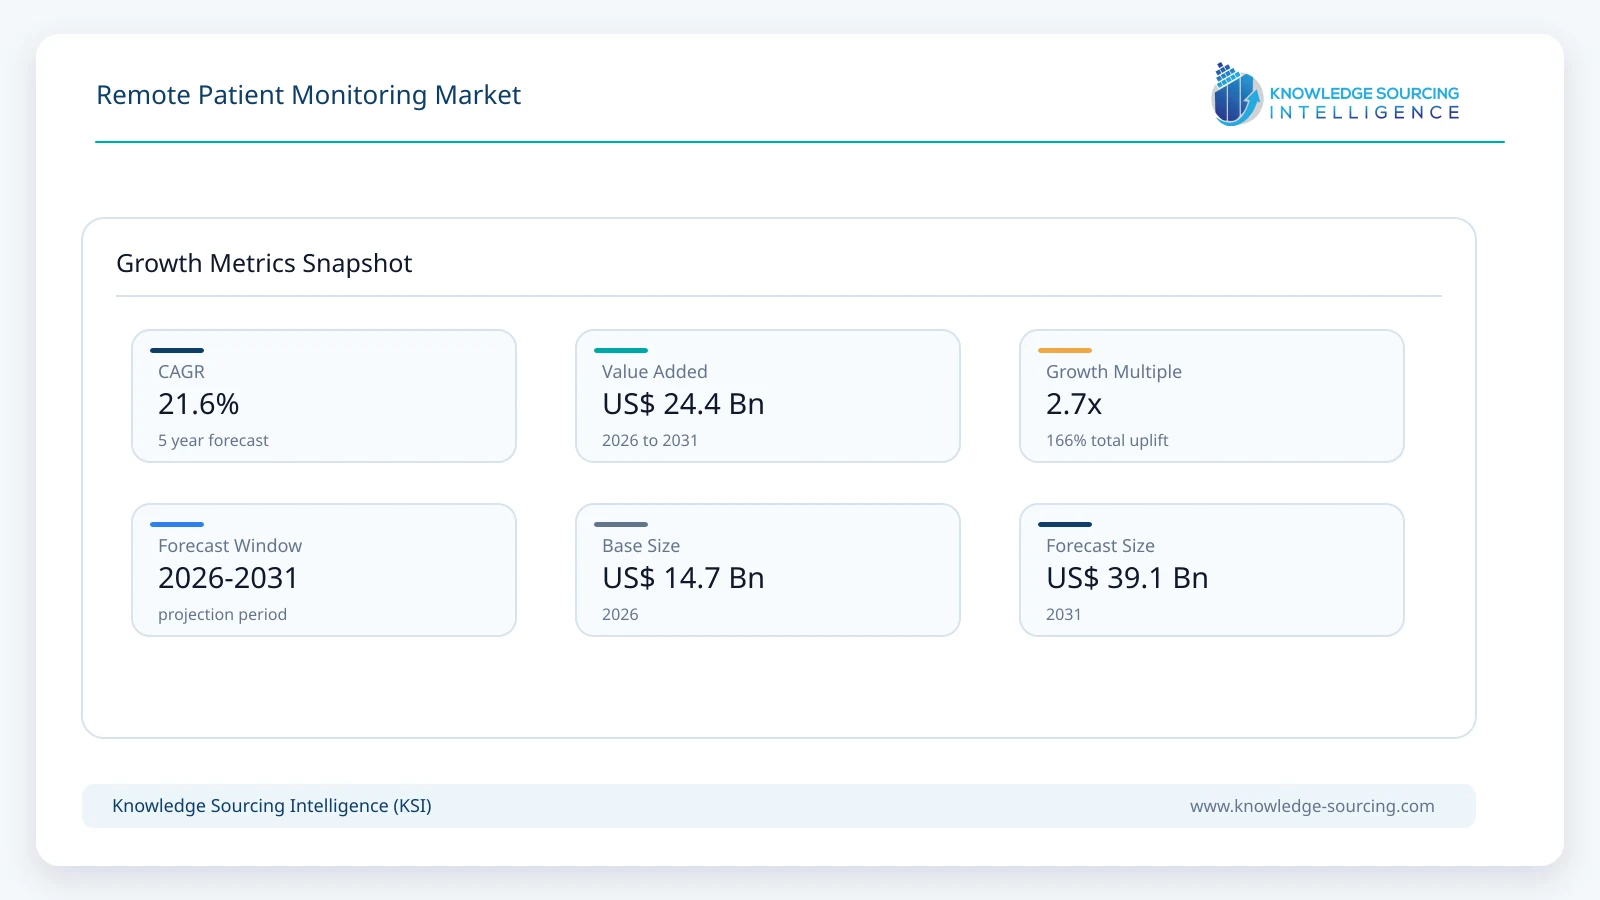
The Remote Patient Monitoring Market is set to reach USD 39.1 billion in 2031, growing at a CAGR of approximately 21.6% between 2026 and 2031, from USD 14.7 billion in 2026.
Highlights:
- 1Hypertension monitoring is estimated to represent 9.8% of overall RPM revenue in 2026, supported by recurring demand for clinician-supervised blood-pressure management.
- 2Purchasing decisions increasingly depend on integration with clinical workflows, escalation protocols and electronic health records, alongside the performance of the connected device.
- 3Recurring platform and monitoring-service contracts create opportunities to expand revenue beyond the initial supply of a sensor or connected measurement kit.
- 4Home-based monitoring broadens the reach of care teams, although sustained adoption depends on patient engagement, reliable data transmission and capacity to act on alerts.
- 5US reimbursement pathways support commercial deployment, while shorter-duration monitoring options introduced for 2026 widen the range of episodes that can qualify under the applicable rules.
- 6Competition is shifting toward connected care ecosystems that combine multiple measurements and clinical coordination within an integrated platform.
Market Overview
Remote patient monitoring connects medical measurements collected outside conventional clinical encounters with teams responsible for reviewing and acting on those measurements. The market includes connected devices, attributable software and monitoring services used within clinically managed programs. Typical measurements include blood pressure, glucose, oxygen saturation, cardiac activity and body temperature. A device becomes commercially relevant to RPM when its data can enter a defined care workflow; connectivity alone does not establish clinical use. Consequently, standalone consumer wellness products and ordinary home diagnostic purchases should not automatically be counted as RPM revenue. The study retains the supplied headline estimate of USD 14.7 billion in 2026 and USD 39.1 billion in 2031. These endpoints imply approximately 21.6% annual growth over five years. Their commercial interpretation depends on consistent treatment of hardware, software and services across the forecast period.
The principal commercial opportunity lies in converting intermittent measurement into a repeatable monitoring relationship. Providers need onboarding, device logistics, patient support, alert review and integration with existing records. Vendors that support these functions can compete for recurring contracts rather than relying only on hardware replacement. Wearable sensors can extend the frequency of observation, while connected cuffs and scales remain useful where periodic measurements fit the clinical purpose. Greater measurement frequency also creates operational costs: teams must distinguish actionable changes from missing readings, technical errors and low-priority notifications. Growth therefore depends on the economics of the full monitoring workflow. Contracts that specify clinical responsibilities, service levels and escalation ownership are more likely to support scalable deployment than arrangements centered solely on device distribution.
Within digital health, RPM provides an ongoing data relationship between patients and care teams. Its addressable revenue should be separated from unrelated video consultations and general healthcare IT expenditure.
The use of healthcare artificial intelligence can support prioritization and workflow assistance. Commercial value depends on validation, oversight and integration rather than the presence of an AI label.
Bundled contracts require careful revenue allocation. Device receipts, software fees and outsourced monitoring payments must be counted once within the market boundary; provider reimbursement cannot simply be added to supplier revenue when it finances the same service.
Market Drivers
Rising Burden of Chronic Diseases and Demand for Continuous Care
Chronic disease management creates repeated demand for measurements between appointments. Hypertension, diabetes and heart failure involve treatment decisions informed by changes over time, making them relevant use cases for connected monitoring. The business opportunity is strongest where regular data review can be embedded into an existing care pathway and funded through a sustainable contract or reimbursement mechanism. Disease prevalence establishes the potential patient pool, but it does not equal paying demand: diagnosis, treatment access, clinical eligibility, patient consent and provider capacity determine how many people can enter an RPM program. This distinction matters particularly in countries where connected devices are affordable but staff time and service funding are constrained. Vendors must therefore pair clinical relevance with accessible onboarding, dependable support and a credible operating model. Expanding a program without adequate review capacity can increase the volume of unaddressed alerts instead of improving the usefulness of monitoring.
WHO estimated that 1.4 billion adults aged 30–79 had hypertension in 2024. This demonstrates a substantial clinical need; only a portion of that population can reasonably be treated as a near-term commercial RPM opportunity.
The IDF Diabetes Atlas 2025 estimates that 589 million adults aged 20–79 had diabetes in 2024, with 853 million projected for 2050. This supports long-term demand for continuous glucose monitoring and associated clinical data services, without implying that all CGM sales belong within RPM.
Procurement increasingly requires evidence of manageable staff workload, sustained patient participation and clear responsibility for abnormal readings. These requirements favor solutions designed around a specific care pathway.
Reimbursement supports uptake where programs meet eligibility, documentation and service requirements. Payment availability alone does not establish profitability after device supply, connectivity, staffing and patient-support costs.
Major Segment Analysis
Hypertension Monitoring — By Application
Hypertension sits within Chronic Disease Management in the existing application segmentation. The scenario estimates attributable RPM revenue of USD 1.44 billion in 2026, rising to USD 3.27 billion in 2031. This represents a 17.8% CAGR over five years. Against the supplied overall market totals, its share moves from 9.8% in 2026 to 8.4% in 2031. Revenue therefore expands substantially while its relative contribution declines because the overall market forecast grows faster. This is a selected application deep dive, rather than a claim that hypertension is the largest RPM category. The calculation concerns clinician-managed hypertension programs and their attributable technology and monitoring-service revenue. It does not measure the standalone blood-pressure monitor device market, and it does not include all healthcare expenditure incurred by people who have hypertension. The figures are estimates; underlying enrollment and revenue assumptions are not independently measured market observations.
The base-year calculation assumes 4.0 million annual-equivalent monitored patients and USD 360 in attributable annual revenue per patient, giving USD 1.44 billion. The forecast assumes 8.175 million annual-equivalent monitored patients and USD 400 per patient in 2031, giving USD 3.27 billion. Annual-equivalent patients are monitored patient-months divided by twelve, so a person monitored for only three months contributes one quarter of an annual equivalent. This treatment avoids valuing every enrolled person as a full year of revenue. The implied patient-equivalent CAGR is approximately 15.4%, while revenue per patient rises about 2.1% annually. Together these assumptions produce the segment forecast. The population statistics establish clinical context, but they do not validate these commercial conversion assumptions. Enrollment, retention, net contract prices and the allocation of bundled fees are the main variables requiring further evidence.
Connected blood-pressure measurements can support longitudinal review and treatment follow-up. Commercial differentiation depends on dependable transmission, usable patient instructions and defined escalation processes, alongside measurement accuracy.
Multimorbidity requires a consistent primary-application allocation. A patient with both diabetes and hypertension must not generate duplicate recognition of the same bundled subscription in two application segments.
The revenue boundary includes attributable devices, software and contracted monitoring services once. Reimbursement receipts and vendor payments financing the same service are not additive.
If enrollment or revenue per patient is 20% below the base assumption, segment revenue falls 20% when the other input is held constant. Both inputs falling 20% would reduce revenue 36%, illustrating the sensitivity of the estimate.
Homecare Settings
The existing end-user segmentation includes hospitals and clinics, ambulatory care centers, homecare settings and others. Homecare settings remain relevant because patients can collect measurements during ordinary daily routines, reducing reliance on visits solely for data collection. However, the monitoring location and the contracting customer must be distinguished. A hospital-operated program delivered in a patient’s home should be allocated consistently under the chosen customer convention; it should not also be counted as a separate homecare purchase. Dedicated homecare organizations can use RPM to coordinate follow-up and identify changes that require review, but the commercial model must absorb installation, connectivity support, device recovery and patient training. Suppliers that simplify these practical tasks can improve retention and reduce service costs. This supports the homecare opportunity without assigning an unsupported market share or asserting that it is the fastest-growing end-user category.
For homecare operators, ease of use and technical support influence whether patients continue to submit readings after initial enrollment.
Interoperability can reduce duplicate entry and make monitoring data available within established clinical workflows, although implementation and maintenance remain important purchasing costs.
The distinction between remote physiological monitoring and remote therapy management should be maintained when evaluating platforms serving specialized home treatments.
Regional Analysis
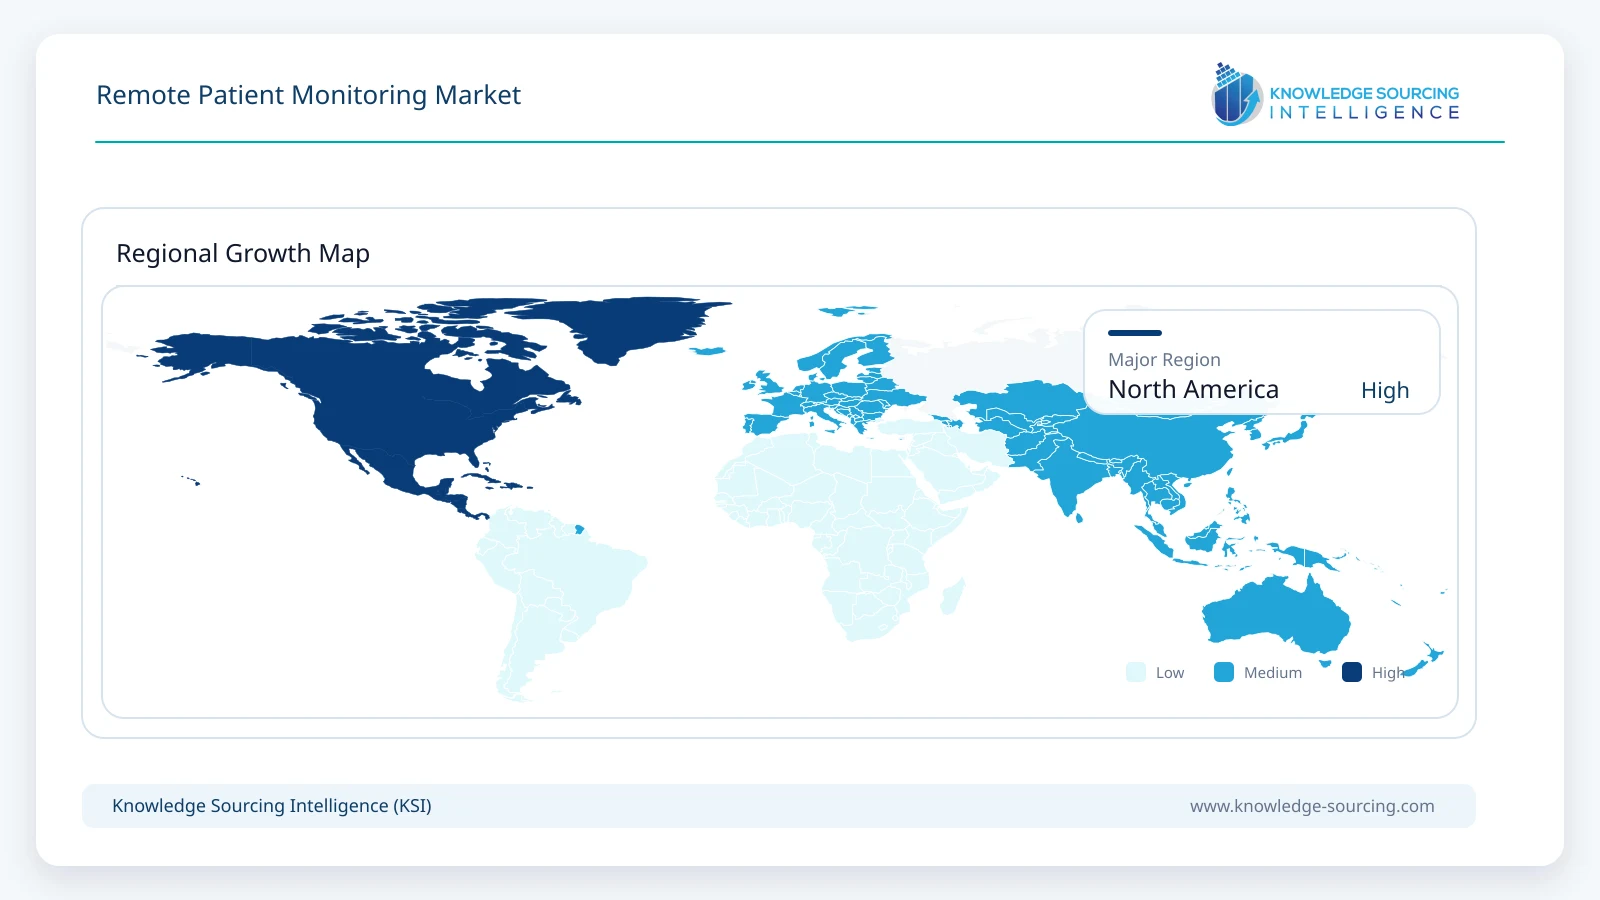
North America: the US
The United States offers an established reimbursement environment for remote physiological monitoring, making it an important commercial reference point. In 2026, CPT 99445 addresses device monitoring with 2–15 days of recordings or alerts within the applicable period, while CPT 99470 addresses shorter treatment-management time beginning at ten minutes. These options can support clinically appropriate shorter episodes, but they do not create unrestricted additional billing: alternative duration codes must be used according to their requirements. Providers still need patient consent, compliant devices, documentation and the capacity to review data. Vendors therefore compete on their ability to support reliable clinical and administrative workflows. Market growth should be assessed through actual adoption, collected revenue and retention rather than multiplying a published reimbursement rate by the entire eligible population.
Health-system buyers may prefer integration with existing records and centralized review processes, while smaller practices may place greater weight on onboarding support and outsourced operational services.
Connectivity barriers, patient participation and staffing costs can limit deployment even where reimbursement exists. These variables affect both contract renewal and realized revenue per monitored patient.
North America is discussed as a commercially important region; no numerical regional leadership claim is made without a reconciled geographic model.
Company Profiles
Abbott Laboratories participates in connected chronic care through glucose monitoring and cardiovascular technologies. Its commercial relevance to RPM depends on the specific connected product, the associated clinical workflow and the attributable revenue boundary. A diversified supplier’s total medical-device revenue should not be treated as RPM sales. The distinction is particularly important when sensors are used for patient self-management without an ongoing clinician-supervised monitoring service.
Abbott’s February 2026 FDA approval for the CardioMEMS HERO reader illustrates the role of usability in a recurring monitoring relationship. The reader supports collection and transmission of pulmonary artery pressure measurements for patients with an implanted CardioMEMS sensor. For suppliers, improving the routine measurement experience can support continued participation and strengthen the broader connected-care offering. This product development establishes relevant market activity; it does not independently establish Abbott’s share of the overall RPM market.
Key Developments
October 2026: Teladoc Health announced SoloVitals and SoloScribe within its Solo platform. SoloScribe was generally available; SoloVitals was in private preview, with general release expected in December 2026. These hospital workflow capabilities illustrate connected-care platform development rather than a completed rollout of home RPM.
September 2026: Peerbridge Health announced FDA 510(k) clearance for Cor MDx, an ambulatory wearable recording continuous multichannel ECG for up to 14 days.
August 2026: Philips announced collaborations with Blue Spark Technologies, Caretaker Medical, Cuviva, LifeSignals, Respiree and smartQare to expand its wearable and out-of-hospital monitoring ecosystem.
June 2026: Fresenius Medical Care launched kinexus globally to connect home dialysis therapy monitoring and operational workflows. This is an adjacent remote therapy platform development; its full revenue is not automatically included in physiological RPM.
February 2026: Abbott received FDA approval for its CardioMEMS HERO reader, an updated patient system supporting remote pulmonary artery pressure monitoring.
Remote Patient Monitoring Market Scope:
| Report Metric | Details |
|---|---|
| Total Market Size in 2026 | USD 14.7 billion |
| Total Market Size in 2031 | USD 39.1 billion |
| Forecast Unit | Billion |
| Growth Rate | 21.6% |
| Study Period | 2021 to 2031 |
| Historical Data | 2021 to 2024 |
| Base Year | 2025 |
| Forecast Period | 2026 – 2031 |
| Segmentation | Component, Device Type, Connectivity, Application, End User, Geography |
| Companies |
|
| Customization Scope | 15% Free Customization included with purchase — Request Custom Breakdown → |
| Sample & Data Access | PDF Sample, Excel Databook & Analyst Briefing — Download Free Sample → |
Market Segmentation
By Component
Devices
Software & Platforms
Services
By Device Type
Vital Signs Monitor
Glucose Monitor
Blood Pressure Monitor
Heart Rate Monitors
ECG Monitors
Respiratory Monitors
Weight Scale
Pulse Oximeters
Others
By Connectivity
Cellular
Bluetooth
Wi-Fi
Others
By Application
Chronic Disease Management
Cardiac
Hypertension
Respiratory
Diabetes
Others
Acute Care Monitoring
Post-Surgical Monitoring
Hospital-at-Home
Others
Elderly Care
Senior Monitoring
Fall Detection
Others
Wellness
Fitness Monitoring
Preventive Healthcare
Lifestyle Monitoring
By End User
Hospitals and Clinics
Ambulatory Care Centers
Homecare Settings
Others
By Geography
North America
USA
Canada
Mexico
South America
Brazil
Argentina
Others
Europe
United Kingdom
Germany
France
Spain
Others
Middle East and Africa
Saudi Arabia
UAE
Others
Asia Pacific
China
India
Japan
South Korea
Thailand
Indonesia
Others
Table of Contents
1. EXECUTIVE SUMMARY
2. MARKET SNAPSHOT
2.1. Market Overview
2.2. Market Definition
2.3. Scope of the Study
2.4. Market Segmentation
3. MARKET DYNAMICS
3.1. Market Drivers
3.2. Market Restraints
3.3. Market Opportunities
3.4. Porter’s Five Forces Analysis
3.5. Industry Value Chain Analysis
3.6. Installed Base Analysis and RPM Platform Ecosystem
3.7. Strategic Recommendations
4. BUSINESS LANDSCAPE
4.1. Regulatory and Reimbursement Landscape
4.2. Regional Adoption Landscape (Buyers & Supplier Analysis)
4.3. Leading Device and End-User Categories
4.4. Device Shipments (Units)
4.5. Active Remotely Monitored Patients Analysis
4.6. Patient Monitoring Volume (Patient-Months / Monitoring Days)
4.7. Revenue Analysis (Hardware vs. Software & Recurring Services)
4.8. Distribution Channel Analysis
5. TECHNOLOGICAL AND PATENT OUTLOOK
5.1. Wearable & Sensor Technologies
5.1.1. Continuous Multiparameter Wearable Patches
5.1.2. Miniaturized Biosensors
5.1.3. Continuous Glucose Monitoring (CGM)
5.1.4. Cuffless Blood Pressure Monitoring
5.1.5. Contactless Respiratory & Cardiac Monitoring
5.1.6. Digital Biomarkers for Continuous Patient Assessment
5.2. Artificial Intelligence & Clinical Decision Support
5.2.1. AI-Based Patient Deterioration Prediction
5.2.2. Personalized Alert Thresholds
5.2.3. Edge Analytics for Real-Time Monitoring
5.2.4. Automated Clinical Triage & Alert Prioritization
5.3. Connectivity & Interoperability
5.3.1. Bluetooth, Wi-Fi, NFC & Cellular Connectivity
5.3.2. EHR Integration using APIs & HL7 FHIR
5.4. Patent Landscape
5.4.1. Wearable Sensors & Biosensors
5.4.2. AI & Predictive Analytics
5.4.3. Patent Activity by Leading Companies
6. REMOTE PATIENT MONITORING MARKET BY COMPONENT (2021-2031)
6.1. Introduction
6.2. Devices
6.3. Software & Platforms
6.4. Services
7. REMOTE PATIENT MONITORING MARKET BY DEVICE TYPE (2021-2031)
7.1. Introduction
7.2. Vital Signs Monitor
7.3. Glucose Monitor
7.4. Blood Pressure Monitor
7.5. Heart Rate Monitors
7.6. ECG Monitors
7.7. Respiratory Monitors
7.8. Weight Scale
7.9. Pulse Oximeters
7.10. Others
8. REMOTE PATIENT MONITORING MARKET BY CONNECTIVITY (2021-2031)
8.1. Introduction
8.2. Cellular
8.3. Bluetooth
8.4. Wi-Fi
8.5. Others
9. REMOTE PATIENT MONITORING MARKET BY APPLICATION (2021-2031)
9.1. Introduction
9.2. Chronic Disease Management
9.2.1. Cardiac
9.2.2. Hypertension
9.2.3. Respiratory
9.2.4. Diabetes
9.2.5. Others
9.3. Acute Care Monitoring
9.3.1. Post-Surgical Monitoring
9.3.2. Hospital-at-Home
9.3.3. Others
9.4. Elderly Care
9.4.1. Senior Monitoring
9.4.2. Fall Detection
9.4.3. Others
9.5. Wellness
9.5.1. Fitness Monitoring
9.5.2. Preventive Healthcare
9.5.3. Lifestyle Monitoring
10. REMOTE PATIENT MONITORING MARKET BY END USER (2021-2031)
10.1. Introduction
10.2. Hospitals and Clinics
10.3. Ambulatory Care Centers
10.4. Homecare Settings
10.5. Others
11. REMOTE PATIENT MONITORING MARKET BY GEOGRAPHY (2021-2031)
11.1. Introduction
11.2. North America
11.2.1. By Component
11.2.2. By Device Type
11.2.3. By Connectivity
11.2.4. By Application
11.2.5. By End User
11.2.6. By Country
11.2.6.1. USA
11.2.6.2. Canada
11.2.6.3. Mexico
11.3. South America
11.3.1. By Component
11.3.2. By Device Type
11.3.3. By Connectivity
11.3.4. By Application
11.3.5. By End User
11.3.6. By Country
11.3.6.1. Brazil
11.3.6.2. Argentina
11.3.6.3. Others
11.4. Europe
11.4.1. By Component
11.4.2. By Device Type
11.4.3. By Connectivity
11.4.4. By Application
11.4.5. By End User
11.4.6. By Country
11.4.6.1. United Kingdom
11.4.6.2. Germany
11.4.6.3. France
11.4.6.4. Spain
11.4.6.5. Others
11.5. Middle East and Africa
11.5.1. By Component
11.5.2. By Device Type
11.5.3. By Connectivity
11.5.4. By Application
11.5.5. By End User
11.5.6. By Country
11.5.6.1. Saudi Arabia
11.5.6.2. UAE
11.5.6.3. Others
11.6. Asia Pacific
11.6.1. By Component
11.6.2. By Device Type
11.6.3. By Connectivity
11.6.4. By Application
11.6.5. By End User
11.6.6. By Country
11.6.6.1. China
11.6.6.2. India
11.6.6.3. Japan
11.6.6.4. South Korea
11.6.6.5. Thailand
11.6.6.6. Indonesia
11.6.6.7. Others
12. COMPETITIVE ENVIRONMENT AND ANALYSIS
12.1. Major Players and Strategy Analysis
12.2. Market Share Analysis
12.3. Mergers, Acquisitions, Agreements, and Collaborations
12.4. Competitive Dashboard
13. COMPANY PROFILES
13.1. Koninklijke Philips N.V.
13.2. Abbott Laboratories
13.3. GE Healthcare Technologies Inc.
13.4. Boston Scientific Corporation
13.5. Biotronik SE & Co. KG
13.6. Honeywell International, Inc.
13.7. Nihon Kohden Corporation
13.8. Osi Vision LLC
13.9. AMC, Inc.
13.10. Medtronic plc
13.11. Omron Corporation
13.12. Teladoc Health, Inc.
13.13. Masimo Corporation
13.14. Resmed
13.15. Biofourmis
13.16. Dexcom, Inc.
14. RESEARCH METHODOLOGY
15. LIST OF FIGURES
16. LIST OF TABLES





Frequently asked questions
What is the projected market size for Remote Patient Monitoring by 2031?
The Remote Patient Monitoring Market is projected to reach USD 39.1 billion by 2031.
What is the Compound Annual Growth Rate (CAGR) for the RPM market?
The Remote Patient Monitoring Market is growing at a 21.6% CAGR between 2026 and 2031.
What are the primary growth drivers for the RPM market?
AI integration, patient-centric care, and evolving reimbursement policies drive growth.
What key technologies are enabling RPM market expansion?
AI, wearables, connected devices, cloud computing, and EHR platforms enable growth.
Which major companies are prominent in the Remote Patient Monitoring market?
Philips, GE HealthCare, Medtronic, Abbott, Dexcom, and Biofourmis are leaders.
How are global policies impacting RPM market expansion?
Evolving reimbursement policies and national digital health strategies facilitate RPM adoption.
Cite this report
Knowledge Sourcing Intelligence. (Oct 2026). Remote Patient Monitoring Market - Strategic Insights and Forecasts (2026-2031). https://www.knowledge-sourcing.com/report/remote-patient-monitoring-market