
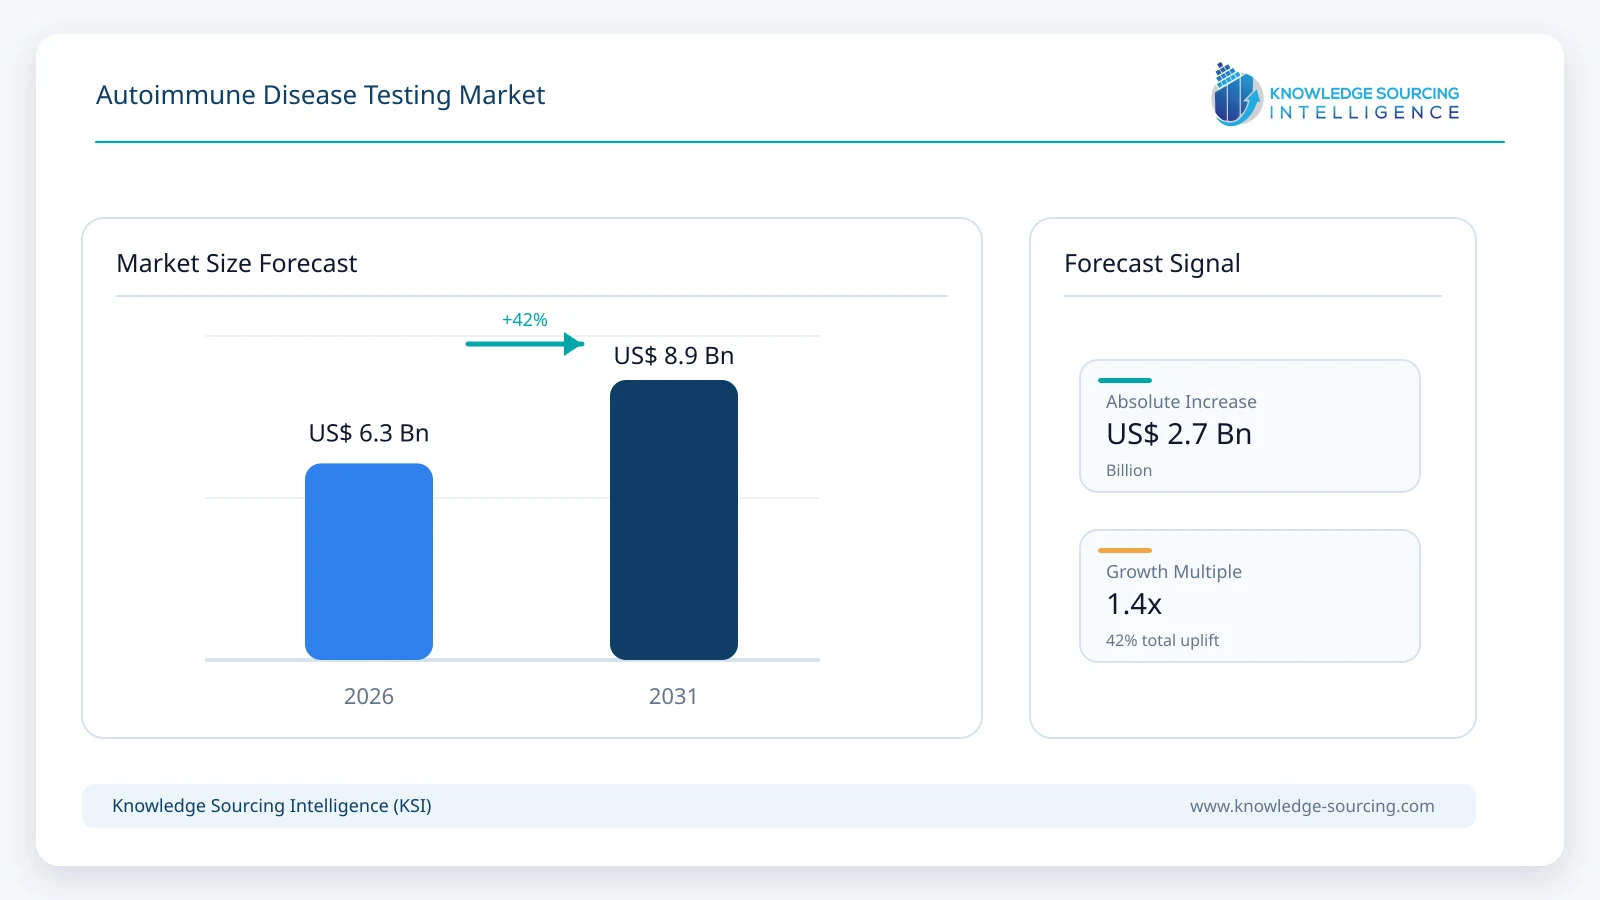
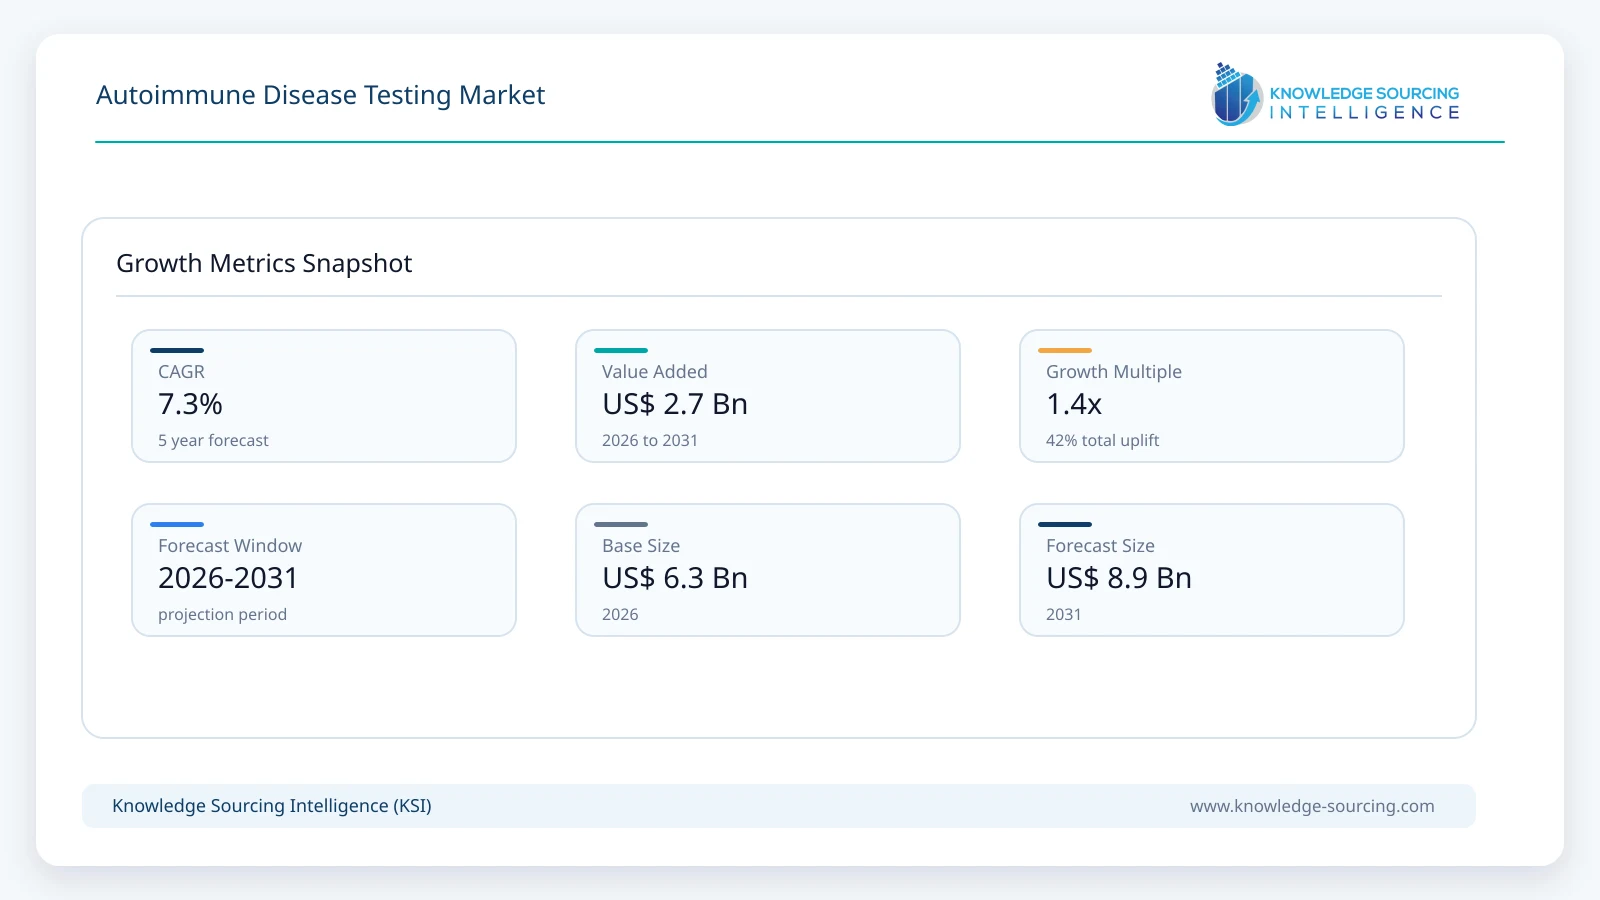
The Autoimmune Disease Testing Market is expected to expand at a CAGR of 7.33%, reaching USD 8.93 billion in 2031 from approximately USD 6.27 billion in 2026.
Highlights:
- 1Reagents and consumables represent approximately 81% of estimated 2026 market value.
- 2Antinuclear antibody testing holds around 26% of the 2026 test-type mix.
- 3Rheumatoid arthritis accounts for an estimated 33% of disease-attributed testing demand.
- 4Diagnostic centers contribute approximately 44% of market value in 2026.
- 5Integrated antigen panels improve clinical differentiation after initial autoimmune screening.
- 6Laboratories increasingly prioritize assay standardization, reflex workflows and clinically justified utilization.
Autoimmune disease testing covers assays and dedicated laboratory equipment used to identify clinically relevant autoantibodies, inflammatory markers, and associated disease profiles. The commercial product base includes reagents, quality-control materials and laboratory instruments, with recurring reagent use accounting for most supplier demand. Testing decisions are driven by clinical suspicion and differential diagnosis; an isolated positive result rarely establishes a specific autoimmune disorder without examination, patient history and confirmatory investigations.
Thermo Fisher Scientific’s EliA platform, Werfen’s Aptiva and QUANTA offerings, Bio-Rad’s BioPlex menus and Revvity’s EUROIMMUN systems demonstrate the different approaches to integrated testing. Their products combine assay availability with automation, quality control, and laboratory connectivity, giving purchasing committees a choice between broad routine chemistry platforms and specialized autoimmune serology systems.
Market Overview
Rheumatoid arthritis, systemic lupus erythematosus and other immune-mediated conditions often present with symptoms shared by unrelated diseases. A clinician may request antinuclear antibodies, rheumatoid factor, or anti-CCP antibodies, followed by narrower markers when warranted. The World Health Organization estimates that 18 million people were living with rheumatoid arthritis in 2019. That burden supports a continuing requirement for laboratory assessment, although testing volume does not rise in direct proportion to disease prevalence because many investigations are performed during diagnosis rather than at every subsequent visit.
At large laboratories, the economics of autoimmune testing depend on reagent utilization and instrument throughput. Thermo Fisher’s Phadia 2500+ family supports an EliA menu spanning more than 50 autoimmune markers, while Bio-Rad’s BioPlex 2200 menus cover antinuclear antibodies, anti-CCP, vasculitis and antiphospholipid panels. Specialized manufacturers such as ORGENTEC and AESKU supply ELISA, immunofluorescence and blot assays for laboratories with different workload requirements. Their commercial advantage is not limited to individual analytes: validated workflows and continuity of supply reduce method-transfer risk for clinical laboratories.
Automation is particularly valuable for indirect immunofluorescence, where slide preparation, image acquisition and pattern interpretation can consume skilled staff time. EUROIMMUN’s automated image-analysis systems and AESKU’s HELIOS instrument address these steps, while Werfen’s assay families allow connective-tissue and antiphospholipid testing on integrated platforms. Competition therefore involves diagnostic accuracy and instrument placement as well as the recurring sale of reagents.
Market Trends
Autoimmune Testing Menus Are Becoming More Clinically Directed
Broad ANA screening remains useful for suspected connective-tissue disease, but screening alone cannot distinguish lupus, Sjögren’s disease and systemic sclerosis reliably. Manufacturers are extending extractable nuclear antigen and disease-specific assays so that laboratories can move from a screening signal to a more informative profile. The FDA’s June 2026 clearance of Phadia’s EliA CTD 13 Screen reflects continuing development of clinically targeted panels rather than simple expansion of total test counts.
In routine practice, reflex rules must match the referring clinician’s indication and the laboratory’s available methods. The ability to offer an appropriate second-line test on the same analytical system can reduce specimen handling and reporting delays. Suppliers with balanced menus are better placed to win laboratory contracts than providers that sell a high-throughput analyzer without enough relevant autoimmune markers.
Immunofluorescence Automation Is Addressing Specialist Labor Constraints
Indirect immunofluorescence continues to be important for antinuclear antibodies and certain vasculitis-related investigations, but results can vary with slide reading, operator training, and image interpretation. AESKU’s HELIOS platform integrates slide handling with image capture and digital pattern recognition, while EUROIMMUN’s automated instruments reduce manual preparation and analysis. These technologies support consistency and create an instrument-reagent relationship that can persist through multiple replacement cycles.
The purchasing case differs between reference laboratories and smaller hospitals. High-volume facilities can spread instrument and validation costs across more samples; facilities with fewer specialist tests may retain semi-automated workflows or send specimens to a central laboratory. Revenue consequently shifts toward instruments where testing volume and staffing pressure justify the installation, while routine reagent purchases remain essential across both arrangements.
Multiplex Panels Are Competing With Sequential Single-Analyte Testing
Multiplex assays can measure several disease-associated antibodies from one specimen, potentially shortening the work required to investigate a complex connective-tissue presentation. Werfen’s Aptiva portfolio uses particle-based multi-analyte technology, and Bio-Rad offers autoimmune panels on its BioPlex platform. Their suitability depends on clinical purpose: a panel may efficiently resolve differential diagnosis, but low-pretest-probability testing can yield confusing findings that increase follow-up rather than improve care.
For manufacturers, larger menus increase the value of installed systems and encourage repeat reagent purchasing. Laboratories assess that value alongside assay specificity, reference ranges, reimbursement and the ability to explain results to clinicians. Multiplex adoption should therefore be viewed as a substitution between workflows, not an automatic increase in the number of appropriately indicated tests.
Laboratory Software Is Moving Closer to Assay Interpretation
Specialist autoimmune laboratories manage a broad range of antigens, instruments and reporting conventions. Werfen’s October 2026 release of QUANTA Link 5.0 adds browser-based access to autoimmune workflow management, illustrating supplier interest in the infrastructure surrounding the laboratory result. Such software can help consolidate analyzer information, standardize review and make complex test menus more manageable for staff.
Connectivity is becoming a procurement requirement when laboratories operate several autoimmune methods or distribute specimens across sites. Software functions are valuable insofar as they improve traceability and reduce avoidable manual handling; they do not replace medical interpretation. Data security, interface validation and the distinction between laboratory workflow tools and regulated diagnostic decision support continue to influence implementation.
Segment Analysis
By Product Type: Reagents & Consumables
Reagents and consumables are projected to reach approximately USD 7.50 billion by 2031, reflecting the repeated purchase of assay materials for a growing installed instrument base. Autoantibody reagents, calibrators, controls and related disposables generate recurring expenditure even when laboratory analyzers remain in service for many years. Systems with a wide, clinically relevant menu encourage laboratories to consolidate purchasing and reduce the number of analytical platforms requiring separate maintenance.
Thermo Fisher, Werfen, Bio-Rad and specialist autoimmune assay manufacturers compete through analytical performance, dependable kit supply and compatible automation. The balance between a high-volume screening assay and lower-volume confirmatory tests affects reagent economics, while method standardization can make a laboratory reluctant to replace an established system without clear clinical or workflow gains.
By Test Type: Antinuclear Antibody (ANA) Test
Antinuclear antibody testing remains central to investigating suspected systemic autoimmune conditions because it can identify a pattern of immune reactivity that guides more specific testing. ANA assays are available through indirect immunofluorescence as well as solid-phase immunoassays, and the clinical value of a positive screen depends heavily on symptoms and other findings. Laboratories that can report results consistently while supporting appropriate second-line testing are likely to capture the strongest demand.
The ANA test segment is projected to grow at approximately 9.7% annually through 2031, supported by greater laboratory access and improvements in automated immunofluorescence. Expansion should remain clinically selective: ANA positivity can occur without systemic autoimmune disease, and unnecessary screening can create additional testing without improving diagnosis.
By Disease Type: Rheumatoid Arthritis
Testing related to rheumatoid arthritis spans rheumatoid factor, anti-CCP and selected inflammatory markers used in diagnosis and differential assessment. The WHO’s estimate of 18 million people living with the disease globally illustrates the substantial clinical population, although test expenditure depends on access to specialist care, diagnostic practice and the availability of validated assays. Siemens Healthineers and Roche offer relevant markers on established laboratory platforms, while specialty manufacturers provide supplementary disease-focused options.
Rheumatoid arthritis-attributed testing is estimated at approximately USD 2.77 billion in 2031. The largest commercial requirement is consistent testing at diagnosis and at clinically meaningful decision points, rather than indiscriminate repetition of every marker. Diagnostic laboratories compete on reliability, reporting time and the availability of complementary tests that help clinicians resolve uncertain presentations.
By End-User: Diagnostic Centers
Independent and reference diagnostic laboratories can consolidate low-frequency autoimmune assays from multiple hospitals and clinics, supporting high instrument utilization and a broader biomarker menu. Specialized staff and validated laboratory information systems allow these organizations to offer combinations of routine ANA, rheumatoid arthritis, connective-tissue and vasculitis testing that smaller providers may not perform locally. Exagen’s centralized AVISE testing model shows how a specialist laboratory can differentiate itself through proprietary diagnostic profiles and clinical reporting.
Diagnostic centers are expected to generate approximately USD 4.11 billion in 2031. Their growth will depend on referral networks, reimbursement coverage and the efficiency of sample transportation, not merely on the acquisition of more analyzers. Hospitals retain an important role where rapid results and coordinated specialist consultations outweigh the efficiencies of centralized testing.
Market Drivers
Persistent Diagnostic Demand from Chronic Autoimmune Conditions
Rheumatoid arthritis and systemic autoimmune disorders often require laboratory investigation before clinicians can establish a working diagnosis. The burden of chronic rheumatic disease creates an enduring flow of diagnostic referrals, while greater recognition of disease manifestations can bring previously undiagnosed patients into laboratory pathways.
Revenue growth depends on useful clinical testing rather than disease counts alone. Reagent manufacturers benefit most when clinicians have access to consistent screening and confirmatory assays, allowing an informed decision without repeating inconclusive tests.
Expansion of Automated Laboratory Capacity
Automated systems reduce manual pipetting, support controlled reagent handling and improve throughput for recurring autoimmune assays. Large diagnostic laboratories can combine higher-volume tests with specialist markers, making a wider menu economically attractive.
Thermo Fisher’s Phadia systems and Werfen’s multi-analyte platforms illustrate different procurement models. Buyers weigh staffing needs, connectivity and reagent continuity against the capital cost of instruments and the resources required to validate a method.
Demand for More Specific Disease Differentiation
Symptoms shared by lupus, Sjögren’s disease and other connective-tissue conditions complicate decisions based on a first-line ANA result. Assays for extractable nuclear antigens, anti-dsDNA and disease-related antibodies provide additional information when matched to the clinical presentation.
The breadth of a manufacturer’s autoimmune menu can improve its position in laboratory tenders. New assay clearances expand testing options, but routine use depends on clinical validation, test guidelines and the reimbursement environment.
Clinical Laboratory Consolidation
Central laboratories process referrals from several hospital networks and clinics, which creates higher utilization for automated autoimmune systems. Consolidation can support stronger quality control and specialist oversight for tests requiring interpretation.
Suppliers that offer interoperable instruments, reporting software and stable reagent supply are better suited to multi-site contracts. The benefit is particularly relevant where skilled immunofluorescence personnel are scarce or test volumes vary sharply across locations.
Growth of Specialty Autoimmune Biomarker Services
Complex rheumatology cases can justify advanced panels beyond routine screening, particularly where conventional serology gives inconsistent or incomplete results. Exagen’s AVISE portfolio illustrates the value that specialist laboratories may place on differentiated clinical reporting.
Premium-priced services remain a smaller and more selective purchasing category than standard screening. They nevertheless influence market innovation by demonstrating demand for better diagnostic resolution in difficult cases.
Market Restraints
Limited Specificity of Screening Results
An ANA-positive result may occur in patients without a systemic autoimmune condition, and clinical interpretation depends on the symptoms that prompted testing. Broad screening in low-risk populations can generate follow-up investigations that add cost without proportionate clinical benefit.
Laboratories must provide clear reporting and support clinically appropriate reflex pathways. Manufacturers face pressure to demonstrate that expanded panels improve diagnostic decisions rather than simply increase the number of analytes ordered.
Regulatory Documentation and Method Validation
Autoimmune immunoassays require validated sensitivity, specificity, repeatability and defined clinical indications. In the European Union, the IVDR increases requirements for performance evidence and ongoing oversight, while laboratories must establish local method performance before adopting new tests.
The associated technical files, reviews and laboratory verification can slow assay launches and menu expansion. Smaller suppliers face a particularly difficult balance between the cost of compliance and the limited volume of rare-disease markers.
Reimbursement Pressure and Test-Ordering Controls
Diagnostic purchasers cannot assume that a broader autoimmune panel will be reimbursed at a price corresponding to its number of markers. Payers and health systems may restrict coverage when clinical utility is uncertain, and inappropriate ordering can create downstream expenditure.
Specialty laboratory services must defend their clinical value through outcomes and utilization evidence. Routine assay manufacturers face pricing pressure as procurement teams compare equivalent methods and negotiate consolidated contracts.
High Implementation Costs for Specialized Automation
Advanced immunofluorescence systems and multiplex analyzers require investment in equipment, maintenance, quality control, data interfaces, and staff training. Smaller laboratories may not have the sample volume to justify replacing established manual or outsourced workflows.
The result is uneven equipment adoption across countries and provider types. Manufacturers need flexible instrument configurations and dependable technical support to expand beyond reference laboratories.
Inter-Method Variability and Difficult Result Comparison
Autoantibody assays using different antigens, detection systems and reporting conventions do not always provide directly interchangeable results. Changing platforms can therefore affect longitudinal interpretation for patients monitored by several care providers.
Laboratories must invest in reference materials, external quality assurance and physician education. These requirements can delay switching decisions even when a competing analyzer offers attractive productivity gains.
Regional Outlook
North America
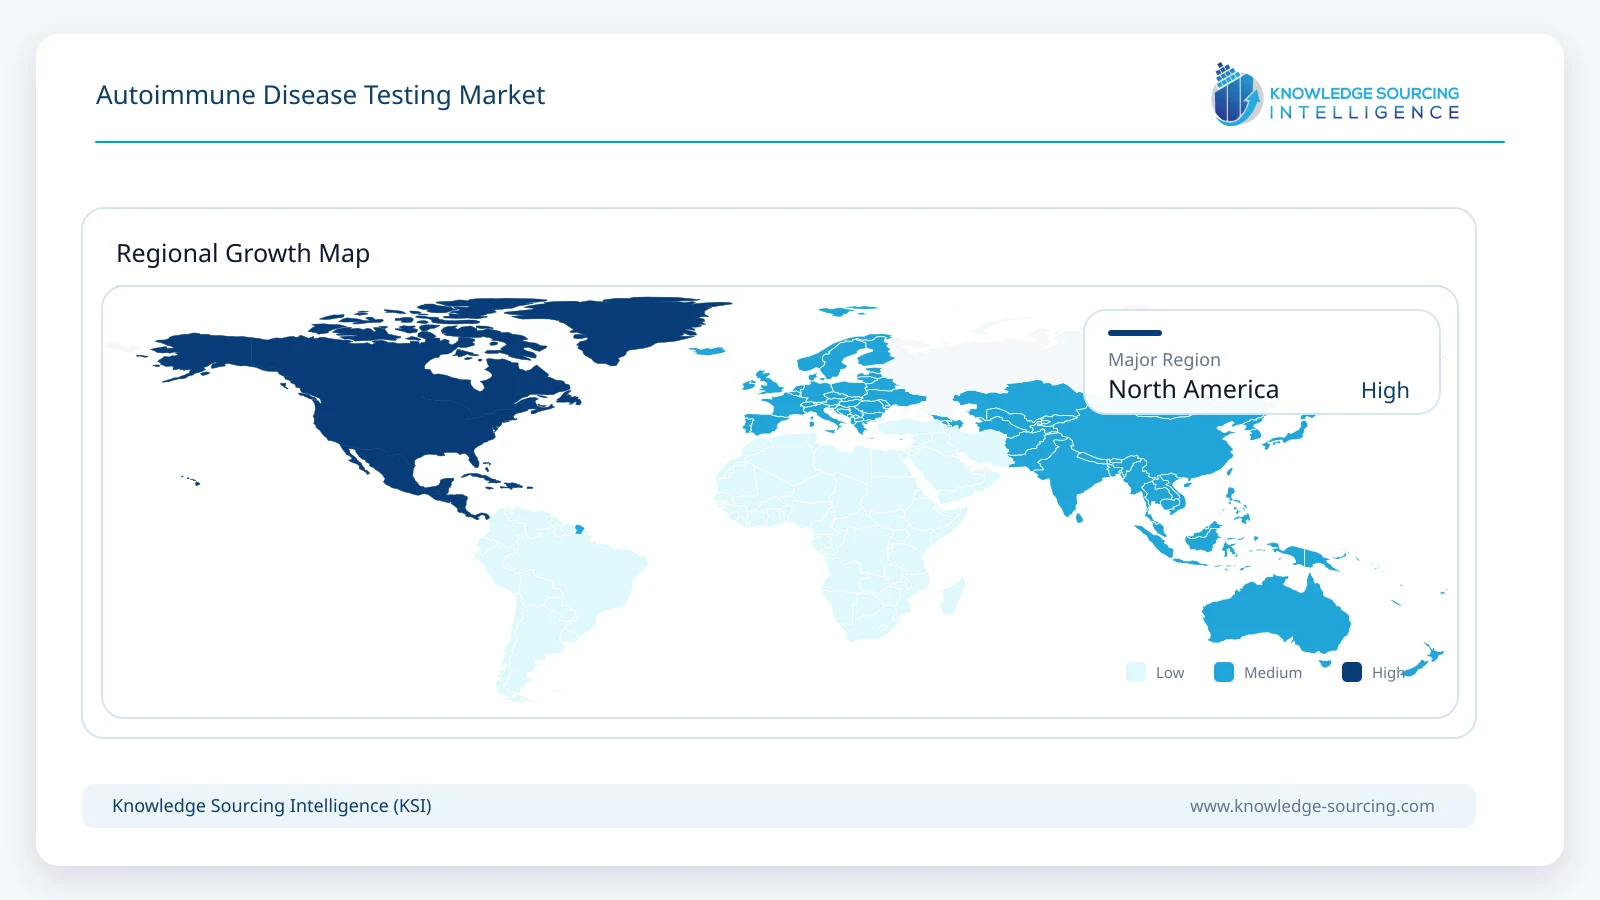
North America accounts for an estimated 35% of global autoimmune disease testing value in 2026. US laboratory infrastructure, specialist rheumatology practice and access to high-complexity testing support substantial demand for both routine autoantibody assays and disease-focused panels. The CDC estimates that more than 200,000 people in the United States have systemic lupus erythematosus, illustrating one defined clinical population requiring appropriate diagnostic access. The region also hosts specialist testing providers such as Exagen, whose centralized AVISE platform competes through differentiated clinical profiles.
US diagnostic spending is concentrated in hospital systems, national laboratories and dedicated rheumatology providers, with strong technical expectations around assay validation and reproducibility. The region remains an important commercialization market for new FDA-cleared reagent menus, but reimbursement requirements and pressure to reduce unnecessary screening limit how quickly expanded panels translate into revenue. Canada and Mexico contribute distinct laboratory-access dynamics within the regional total.
Asia Pacific
Asia Pacific is projected to expand at approximately 10.7% annually from 2026 to 2031, the fastest pace among the modeled major regions. China and India offer large and increasingly accessible diagnostic populations, while Japan and South Korea maintain sophisticated laboratory infrastructure with established use of specialized immunoassays. Investment in automated equipment and broader availability of assay menus can support testing where patients have historically encountered long diagnostic pathways.
Differences in reimbursement, clinical specialist availability and laboratory quality systems will keep growth uneven across countries. In urban referral centers, complex autoimmune profiles can justify multiplex and immunofluorescence automation; outside those centers, affordability and sample transport remain more influential than test-menu breadth. Asia Pacific’s projected rise reflects an expansion of qualified laboratory access as well as gradual adoption of more differentiated testing methods.
Competitive Landscape
Thermo Fisher Scientific, Werfen, Bio-Rad and Revvity compete through broad immunodiagnostic menus supported by specialized instruments, quality controls and laboratory workflow systems. Thermo Fisher’s EliA assays benefit from established Phadia automation; Werfen combines QUANTA Flash, Aptiva and immunofluorescence offerings; Bio-Rad markets multiparameter assays through BioPlex; and Revvity’s EUROIMMUN business addresses immunofluorescence as well as specialty immunoassays. Competitive advantage rests on the number of clinically relevant markers that laboratories can run reliably, not solely on nominal analyzer throughput.
Specialists such as AESKU, ORGENTEC and ZEUS Scientific compete through targeted autoimmune menus and method expertise, while Siemens Healthineers and Roche offer selected markers on broader routine laboratory platforms. Exagen represents a distinct laboratory-service model, where proprietary panels and clinical reports are the customer offering. Laboratory contracts increasingly favor suppliers with validated assays, dependable instrument service, clinically useful test menus and experienced technical support.
Recent Developments
6 October 2026: Werfen launched QUANTA Link 5.0, introducing browser-based autoimmune laboratory workflow management and centralized access to testing information.
23 September 2026: Werfen announced US FDA clearance and a CE mark for its Aptiva antiphospholipid syndrome IgA reagent, completing the platform’s major APS isotype menu.
21 August 2026: The US FDA cleared Immunodiagnostic Systems’ IDS SS-A/Ro, SS-A/Ro 60 kDa and SS-B/La assays, extending the available connective-tissue serology menu.
4 August 2026: Exagen reported an 11% year-on-year increase in AVISE CTD testing volume during the second quarter, underscoring growth in specialized autoimmune laboratory services.
25 June 2026: The US FDA cleared Phadia’s EliA CTD 13 Screen, providing an additional automated connective-tissue disease screening option.
22 October 2025: The US FDA cleared ZEUS Scientific’s Alegria Flash CTD Screen, an automated immunoassay for connective-tissue disease-associated autoantibodies.
Market Outlook
Clinical interpretation and laboratory workflow integration will shape competitive positioning through 2031. Automated platforms should gain where sample concentration supports high utilization, while specialist immunofluorescence and reflex panels will remain necessary for cases that routine assays cannot resolve. Manufacturers supplying a coordinated selection of screening and confirmatory tests are likely to retain a stronger role in procurement decisions than those offering isolated analytes.
The economic balance between routine reagent demand and higher-value specialty assays will vary among health systems. North American laboratories are expected to emphasize validated methods and reimbursement evidence, whereas Asia Pacific offers greater scope for first-time access to comprehensive autoimmune test menus. Suppliers must accommodate both requirements without encouraging unnecessary testing.
Competitive outcomes will depend on measurable clinical utility, consistent results, and reliable supply. New biomarker products may broaden diagnostic options, but sustained adoption requires evidence that the information changes care decisions. This favors companies able to combine assay development with application expertise, clinical studies, and practical laboratory support.
Autoimmune Disease Testing Market Scope:
| Report Metric | Details |
|---|---|
| Total Market Size in 2026 | USD 6.27 billion |
| Total Market Size in 2031 | USD 8.93 billion |
| Forecast Unit | Billion |
| Growth Rate | 7.33% |
| Study Period | 2021 to 2031 |
| Historical Data | 2021 to 2024 |
| Base Year | 2025 |
| Forecast Period | 2026 – 2031 |
| Segmentation | Product Type, Test Type, Disease Type, End-user |
| Companies |
|
| Customization Scope | 15% Free Customization included with purchase — Request Custom Breakdown → |
| Sample & Data Access | PDF Sample, Excel Databook & Analyst Briefing — Download Free Sample → |
Market Segmentation
By Product Type
Instruments
Analyzers
Flow Cytometers
Others
Reagents & Consumables
By Test Type
Antinuclear Antibody (ANA) Test
C-Reactive Protein Test
Rheumatoid Factor
Anti-CCP Test
Others
By Disease Type
Rheumatoid Arthritis
Lupus
Scleroderma
Vasculitis
Inflammatory Bowel Disease
Others
By End-user
Hospitals & Clinics
Diagnostic Centers
Others
By Geography
North America
USA
Canada
Mexico
South America
Brazil
Argentina
Others
Europe
Germany
France
United Kingdom
Spain
Italy
Others
Middle East and Africa
Saudi Arabia
UAE
Israel
Others
Asia Pacific
China
India
Japan
South Korea
Indonesia
Thailand
Others
Table of Contents
1. EXECUTIVE SUMMARY
2. MARKET SNAPSHOT
2.1. Market Overview
2.2. Market Definition
2.3. Scope of the Study
2.4. Market Segmentation
3. BUSINESS LANDSCAPE
3.1. Market Drivers
3.1.1. Persistent Diagnostic Demand from Chronic Autoimmune Conditions
3.1.2. Expansion of Automated Laboratory Capacity
3.1.3. Demand for More Specific Disease Differentiation
3.1.4. Clinical Laboratory Consolidation
3.1.5. Growth of Specialty Autoimmune Biomarker Services
3.2. Market Restraints
3.2.1. Limited Specificity of Screening Results
3.2.2. Regulatory Documentation and Method Validation
3.2.3. Reimbursement Pressure and Test-Ordering Controls
3.2.4. High Implementation Costs for Specialized Automation
3.2.5. Inter-Method Variability and Difficult Result Comparison
3.3. Market Opportunities
3.4. Porter’s Five Forces Analysis
3.5. Industry Value Chain Analysis
3.6. Policies and Regulations
3.7. Strategic Recommendations
4. TECHNOLOGICAL OUTLOOK
4.1. Automated Immunoassays and Multiplex Systems
4.2. Indirect Immunofluorescence and Digital Pattern Recognition
4.3. Laboratory Connectivity and Reflex Testing
5. AUTOIMMUNE DISEASE TESTING MARKET BY PRODUCT TYPE
5.1. Introduction
5.2. Instruments
5.2.1. Analyzers
5.2.2. Flow Cytometers
5.2.3. Others
5.3. Reagents & Consumables
6. AUTOIMMUNE DISEASE TESTING MARKET BY TEST TYPE
6.1. Introduction
6.2. Antinuclear Antibody (ANA) Test
6.3. C-Reactive Protein Test
6.4. Rheumatoid Factor
6.5. Anti-CCP Test
6.6. Others
7. AUTOIMMUNE DISEASE TESTING MARKET BY DISEASE TYPE
7.1. Introduction
7.2. Rheumatoid Arthritis
7.3. Lupus
7.4. Scleroderma
7.5. Vasculitis
7.6. Inflammatory Bowel Disease
7.7. Others
8. AUTOIMMUNE DISEASE TESTING MARKET BY END-USER
8.1. Introduction
8.2. Hospitals & Clinics
8.3. Diagnostic Centers
8.4. Others
9. AUTOIMMUNE DISEASE TESTING MARKET BY GEOGRAPHY
9.1. Introduction
9.2. North America
9.2.1. USA
9.2.2. Canada
9.2.3. Mexico
9.3. South America
9.3.1. Brazil
9.3.2. Argentina
9.3.3. Others
9.4. Europe
9.4.1. Germany
9.4.2. France
9.4.3. United Kingdom
9.4.4. Spain
9.4.5. Italy
9.4.6. Others
9.5. Middle East and Africa
9.5.1. Saudi Arabia
9.5.2. UAE
9.5.3. Israel
9.5.4. Others
9.6. Asia Pacific
9.6.1. China
9.6.2. India
9.6.3. Japan
9.6.4. South Korea
9.6.5. Indonesia
9.6.6. Thailand
9.6.7. Others
10. COMPETITIVE ENVIRONMENT AND ANALYSIS
10.1. Major Players and Strategy Analysis
10.2. Market Share Analysis
10.3. Mergers, Acquisitions, Agreements, and Collaborations
10.4. Competitive Dashboard
11. COMPANY PROFILES
11.1. Thermo Fisher Scientific Inc. (Phadia)
11.2. Werfen (INOVA Diagnostics)
11.3. Bio-Rad Laboratories, Inc.
11.4. Revvity, Inc. (EUROIMMUN and IDS)
11.5. Siemens Healthineers AG
11.6. F. Hoffmann-La Roche Ltd. (Roche Diagnostics)
11.7. AESKU.Group GmbH
11.8. ORGENTEC Diagnostika GmbH
11.9. ZEUS Scientific LLC
11.10. Exagen Inc.
12. APPENDIX
12.1. Currency
12.2. Assumptions
12.3. Base and Forecast Years Timeline
12.4. Key Benefits for Stakeholders
12.5. Research Methodology
12.6. Abbreviations





Frequently asked questions
What is the forecasted market size by 2031 for autoimmune disease testing?
The Autoimmune Disease Testing Market is projected to reach USD 8.93 billion by 2031.
What is the compound annual growth rate (CAGR) for this market?
The Autoimmune Disease Testing Market is expected to expand at a CAGR of 7.33%.
Which product category holds the largest market share?
Reagents and consumables represent approximately 81% of the market.
Which disease drives the highest testing demand?
Rheumatoid arthritis accounts for an estimated 33% of testing demand.
What is the leading test-type in the market?
Antinuclear antibody testing holds around 26% of the test-type mix.
Which end-user segment contributes most to market value?
Diagnostic centers contribute approximately 44% of the market value.
Cite this report
Knowledge Sourcing Intelligence. (Oct 2026). Autoimmune Disease Testing Market - Strategic Insights and Forecasts (2026-2031). https://www.knowledge-sourcing.com/report/autoimmune-disease-testing-market