
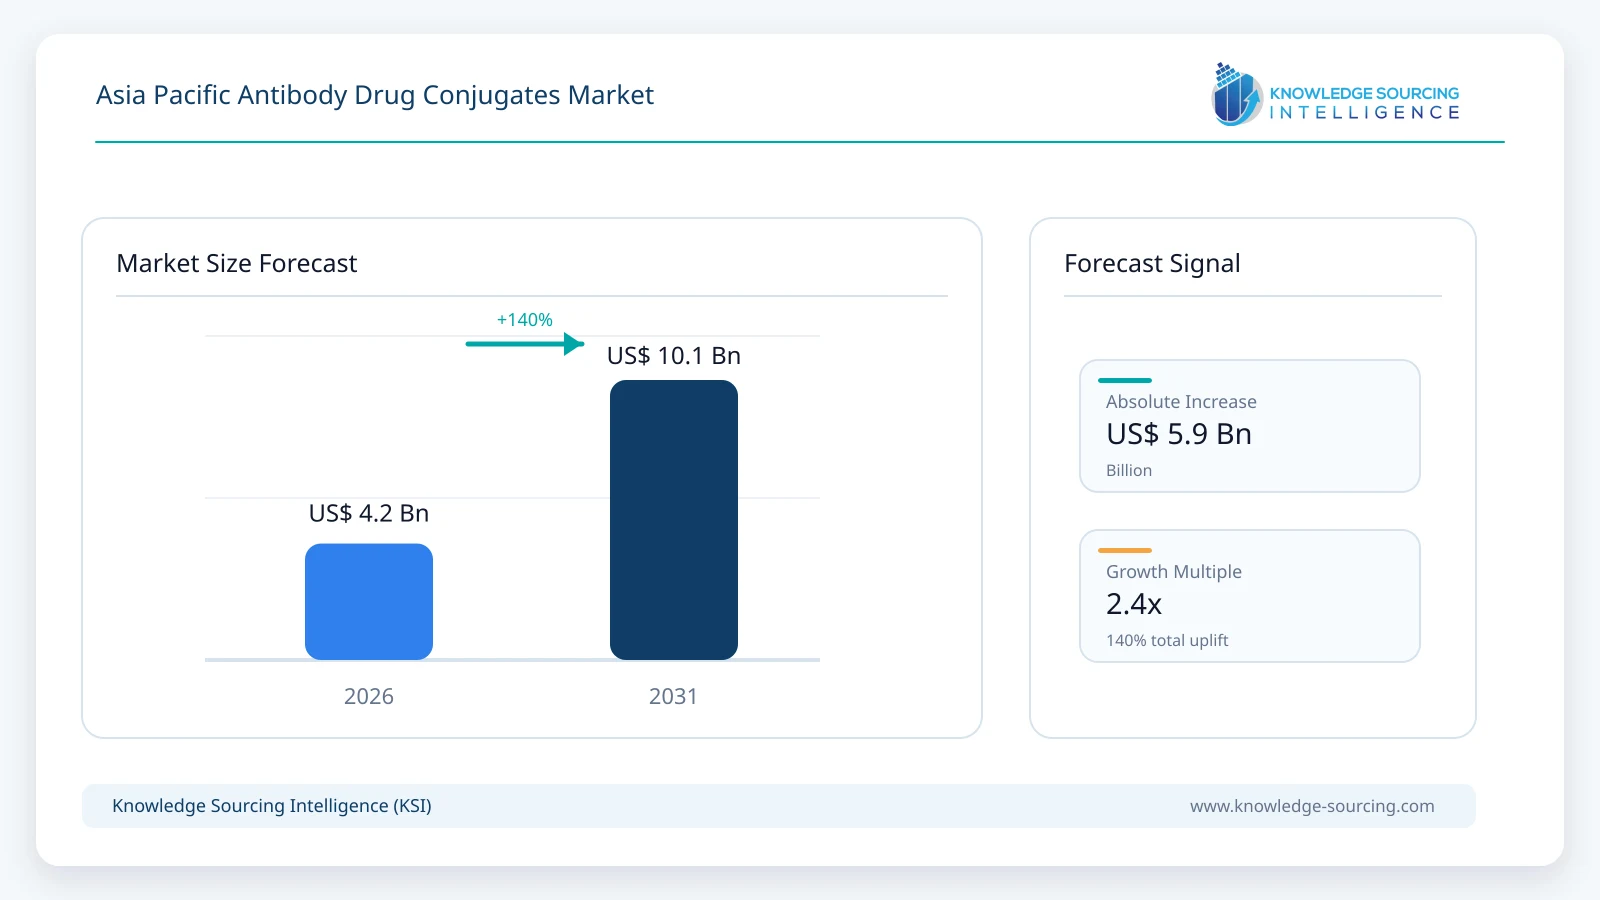
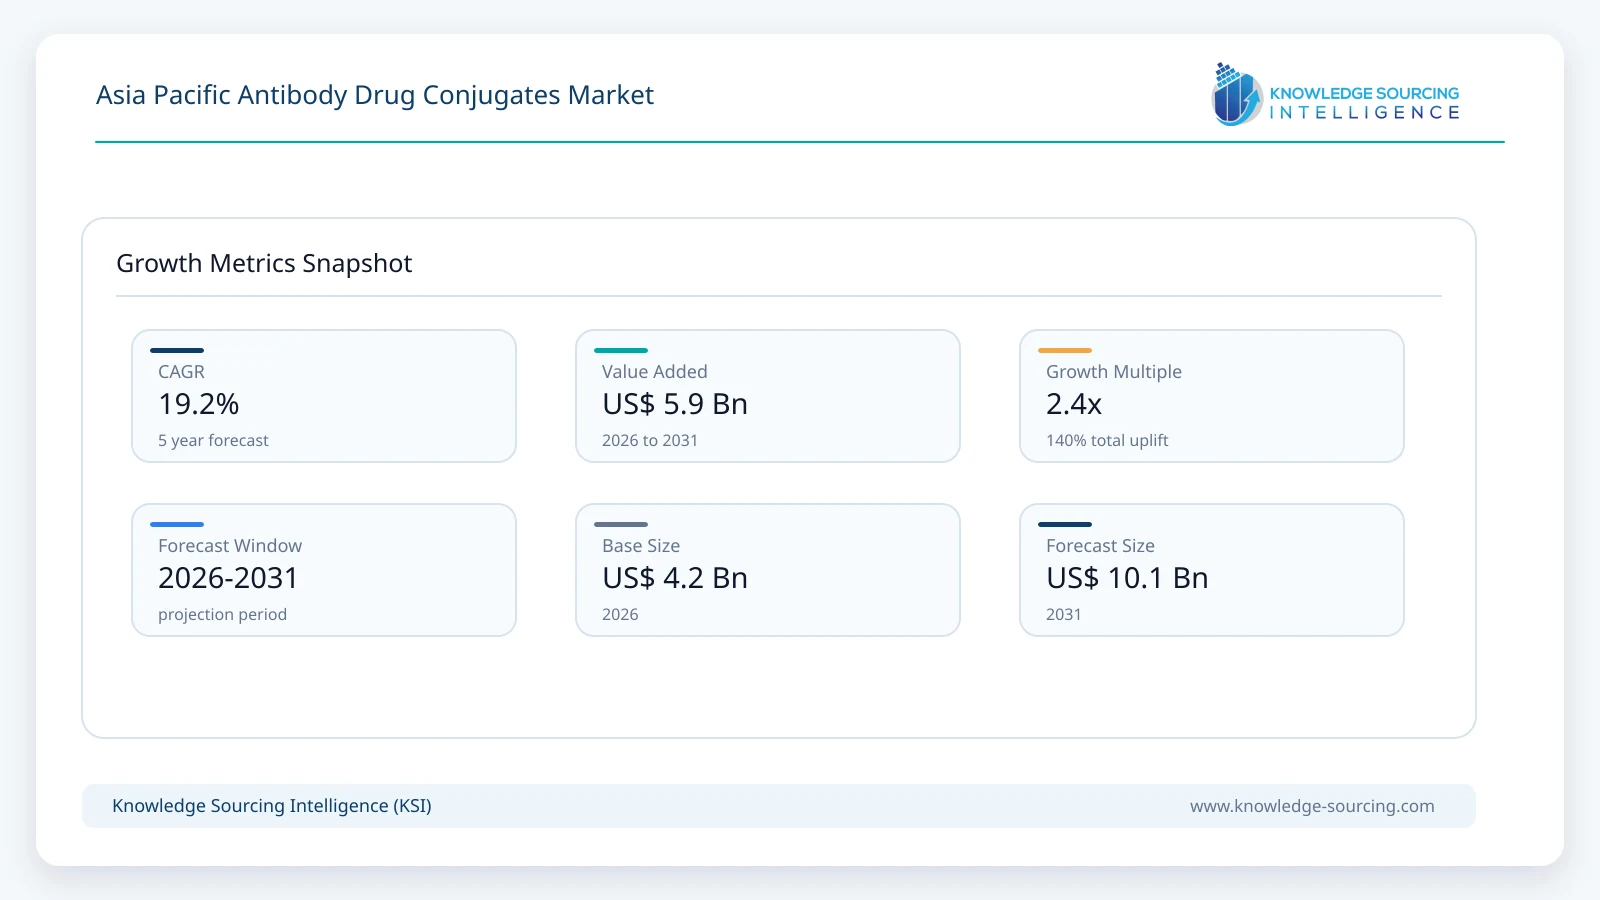
The Asia Pacific Antibody Drug Conjugates Market is projected to expand at a CAGR of 19.2%, reaching USD 10.1 billion in 2031 from USD 4.2 billion in 2026.
Highlights:
- 1HER2-directed medicines represent approximately 42% of 2026 regional ADC sales value.
- 2Cleavable-linker designs dominate commercially established therapies and new solid-tumour launches.
- 3Enhertu and newer ADCs are expanding the product mix beyond older flagship brands.
- 4China leads regional spending; India has the fastest modeled growth trajectory.
- 5Treatment eligibility increasingly depends on biomarker testing and specialist infusion capacity.
- 6Net pricing, reimbursement and interstitial lung disease monitoring constrain patient access.
The Asia Pacific antibody-drug conjugates market covers sales of finished, approved ADC medicines used in oncology, including antibody-linked cytotoxic treatments for solid tumours and hematologic cancers. Medicines are measured at the pharmaceutical selling-value level rather than as treatment administration fees, companion diagnostics, oncology services or contract manufacturing transactions. The category contains established therapies such as Enhertu, Kadcyla, Adcetris, Polivy, Padcev and Trodelvy, together with newer regional products and indications.
Treatment decisions depend on antigen expression, prior therapies, toxicity management and local regulatory labels. Daiichi Sankyo manufactures Enhertu and Datroway under commercial arrangements with AstraZeneca, while Roche markets Kadcyla and Polivy and Pfizer owns the Seagen ADC portfolio. Chinese manufacturers, including RemeGen, are translating proprietary conjugation and payload capabilities into domestic approvals. These positions create different growth trajectories across products even when the overall category expands.
Market Overview
Enhertu has broadened the clinical reach of ADC treatment from previously treated HER2-positive breast cancer into HER2-low disease, gastric cancer, lung cancer and selected other solid tumours. Its tetrapeptide cleavable linker releases a topoisomerase-I inhibitor payload after cellular uptake, whereas Kadcyla uses a non-cleavable linker and microtubule-inhibiting payload. The difference is commercially significant: an ADC’s target alone does not determine interchangeability, and new efficacy data can alter treatment sequencing even within the same biomarker-defined population.
Drug manufacturers have been expanding permitted use across major Asia Pacific markets. Daiichi Sankyo disclosed additional Chinese Enhertu and Datroway approvals in October 2026; RemeGen obtained a further Chinese indication for disitamab vedotin in March. Roche reported continuing growth for Polivy alongside a more mature Kadcyla franchise, while Pfizer and Astellas are seeking broader Padcev use in bladder cancer. Approval dates, treatment line and companion-testing requirements differ by country, preventing a regional launch from translating immediately into uniform regional sales.
Production economics also distinguish ADCs from standard monoclonal antibodies. Manufacturers must control antibody production, payload synthesis, conjugation, drug-to-antibody ratio, analytical testing and potent-compound containment. The scale advantage of established suppliers is therefore accompanied by concentrated technical risk. National reimbursement and provider readiness determine whether additional manufacturing capacity becomes dispensed therapy, particularly in countries where oncology spending remains heavily out of pocket.
Market Trends
HER2 Therapy Is Moving Into Earlier Treatment Lines
China’s August 2026 approval of Enhertu with pertuzumab for first-line HER2-positive metastatic breast cancer reflects a meaningful shift from later-line salvage treatment toward earlier therapeutic use. A patient receiving an ADC sooner in the treatment pathway can increase addressable treatment episodes, although physicians must weigh sequence, toxicity and the evidence supporting each combination.
Earlier-line use is also advancing in the neoadjuvant and adjuvant settings. These indications require different benefit-risk judgments because a larger share of patients may be treated with curative intent. Local regulatory decisions, financing and surveillance for treatment-related lung toxicity will determine the pace at which such labels change routine care.
TROP2 and Other Targets Are Broadening Commercial Choice
Datroway and Trodelvy extend ADC treatment beyond HER2, particularly in selected breast-cancer populations. Datroway received an additional Chinese approval in October 2026 for a specified metastatic triple-negative breast-cancer population. Regulatory breadth matters because different tumour subtypes create distinct clinical and reimbursement pathways, even when products share a broad target such as TROP2.
New targets also bring additional efficacy and safety differentiation rather than automatic replacement of existing chemotherapy or immunotherapy. Companies must demonstrate benefit in a precise treatment setting and sustain enough eligible patient volume to justify specialized promotion and distribution.
China’s Domestic ADC Portfolio Is Becoming More Commercially Significant
RemeGen’s disitamab vedotin has obtained multiple Chinese indications covering HER2-expressing tumours. Chinese manufacturers are increasingly competing through their own clinical programmes while international originators expand approved uses of imported ADCs. Commercial execution now involves oncology-hospital access, reimbursement negotiations and biomarker testing as well as regulatory approval.
The competitive effect is uneven across indications. Locally developed ADCs may have greater scope to compete on procurement terms in selected tumour segments, but they still require differentiated clinical evidence. A reported licensing agreement or a clinical candidate does not represent regional medicine sales until approval, procurement and treatment occur.
Biosimilar Capability Could Alter Mature Product Economics
India’s Department of Pharmaceuticals identifies trastuzumab emtansine among complex medicines manufactured through domestic industrial programmes. As mature ADC patents and exclusivity arrangements evolve, lower-cost versions may broaden access to established products, particularly in budget-constrained treatment channels. Technical comparability and regulatory approval remain essential before such products can be counted as commercially available alternatives.
Biosimilar competition is less likely to affect every ADC franchise simultaneously. Newer products protected by patents and supported by expanded indications retain a different value proposition from mature agents; price erosion in one product can coexist with category revenue growth led by another.
Specialist Delivery Requirements Remain a Commercial Differentiator
ADC administration requires specialist infusion capacity, reliable cold-chain distribution, correct patient selection and monitoring for adverse events. Enhertu’s interstitial lung disease warning is particularly important to patient screening and follow-up. Access therefore depends on trained oncology teams and hospital systems, not merely the number of registered drugs.
Drug companies that support testing workflows, pharmacovigilance and treatment education can improve appropriate adoption within approved labels. Nevertheless, such services should not be confused with additional ADC drug sales, and improved testing alone does not establish a patient’s eligibility for treatment.
Segment Analysis
By Technology: Cleavable Linker
Cleavable-linker ADCs account for an estimated USD 2.78 billion of the regional market in 2026. Enhertu’s peptide linker, along with several marketed auristatin-based ADCs, illustrates how intracellular release of a cytotoxic payload can be matched to antigen targeting and tumour biology. The technology has become commercially prominent because it is represented in both established products and newer solid-tumour indications.
The segment is expected to maintain its lead as treatment expands beyond HER2-positive late-line breast cancer. Its economic position is not a guarantee of clinical superiority over non-cleavable designs: payload properties, safety, linker stability, antigen expression and supporting clinical trials determine how particular products are prescribed. Non-cleavable designs remain important in mature breast-cancer treatment and other selected uses.
By Product Type: Others
The Others category is the largest product grouping because the original KSI taxonomy names Adcetris and Kadcyla individually but places major newer medicines, including Enhertu, Padcev, Polivy, Trodelvy and Datroway, in the residual group. That category increasingly captures the breadth of ADC commercialization in solid tumours and hematologic cancers. It is not a collection of experimental products; only approved medicines contributing finished-drug sales are included.
By 2031, the Others group is projected to reach approximately USD 8.84 billion. Expansion depends particularly on eligible patient populations for newer treatments and indications, while mature Adcetris and Kadcyla retain established clinical roles. A broad residual category is less useful for product-level competitive interpretation, so individual brand positioning is addressed within the market and company analysis.
By Target: HER2
HER2-directed medicines remain the largest identifiable target group because of the number of breast and gastric cancer indications, the established use of Kadcyla and the expanded approvals of Enhertu and disitamab vedotin. HER2 status is not a single uniform eligibility criterion: protein overexpression, gene amplification, lower-level expression and specific tumour types can define different treatment decisions, depending on the medicine and local label.
The HER2 category is projected to generate approximately USD 4.38 billion in 2031. China and Japan account for much of the current commercial opportunity, while additional indications in India and other Asia Pacific markets enlarge the prospective patient pool. Competition within HER2 will turn increasingly on treatment sequence, tolerability, reimbursement and the strength of evidence in each line of therapy.
Market Drivers
Expansion of Biomarker-Defined Oncology Treatment
Broader use of HER2 testing in breast, gastric and selected other cancers identifies patients who may benefit from targeted antibody-drug conjugates. As approved labels become more differentiated, oncology practices must interpret tumour-specific assays and earlier treatment history before choosing an ADC. These activities directly influence how many clinically eligible patients can enter treatment.
Commercial expansion is stronger when testing is accessible before treatment decisions are made and when subsequent reimbursement covers the indicated medicine. Merely increasing the number of tests will not produce equivalent revenue growth if results are inconclusive or eligible patients cannot afford therapy.
Earlier-Line Regulatory Approvals
Daiichi Sankyo’s 2026 Chinese approvals include additional HER2-positive breast-cancer settings, while other companies are investigating movement into earlier treatment lines. Moving a therapy forward can enlarge the treated population and alter course length, but the eligible population must be reassessed separately for neoadjuvant, adjuvant and metastatic indications.
Payers will evaluate incremental clinical benefit against established lower-cost regimens. Earlier treatment adoption can be substantial in Japan and higher-tier Chinese oncology centres where clinical pathways are well developed; elsewhere, procurement budgets and infusion capacity can delay the transition.
Development of Regionally Originated ADC Medicines
Chinese pharmaceutical companies have created proprietary ADC medicines and commercial programmes that are no longer confined to licensing research assets internationally. RemeGen’s approved disitamab vedotin indications demonstrate a regional product with direct domestic treatment relevance rather than an ADC platform existing only in preclinical development.
Local development can expand competition, shorten selected supply chains and introduce additional clinical options. The resulting revenue depends on approvals and hospital use, while licensing milestones and manufacturing-service fees are excluded from sales of finished ADC medicines to prevent double counting.
Growing Access to Specialized Cancer Treatment
Cancer-centre investment, reimbursement coverage and regional oncology networks are broadening treatment capacity in parts of Asia Pacific. ADC utilization is particularly sensitive to access because medicines require hospital administration and trained staff to manage adverse effects, including pulmonary complications and peripheral neuropathy for relevant products.
Access improvements support higher volumes when referral networks, pathology laboratories and drug supply operate together. Expansion will remain uneven between metropolitan cancer centres and smaller hospitals, producing different growth trajectories even within the same national market.
Improvement in ADC Manufacturing and Formulation Capability
Commercial ADC manufacture combines biologics production with potent payload handling, controlled conjugation, and analytical release testing. Regional manufacturers developing these skills can improve reliability of supply and support more products entering clinical and commercial development, particularly in China and India.
Investment does not immediately translate into medicine sales. Complex validation, batch consistency, supply-chain qualification, and product-specific approvals create long lead times, so the forecast recognizes commercially supplied products rather than adding announced capacity or contract-manufacturing revenue to finished-drug value.
Market Restraints
Treatment Cost and Reimbursement Constraints
ADC treatment can entail substantial medicine expense over repeated infusion cycles. Access is sensitive to reimbursement formularies, patient co-payments and public procurement rules, especially where oncology budgets must fund a growing set of targeted therapies. A product can hold regulatory approval for several years without achieving broad utilization.
Price negotiations and managed access arrangements can increase patient volumes while reducing net revenue per treatment. Manufacturer forecasts must therefore distinguish adoption growth from realized selling-price growth and avoid assuming list prices apply across all countries.
Safety Monitoring and Treatment Discontinuation
ADC-related toxicity differs by product, target and payload. Pneumonitis or interstitial lung disease associated with trastuzumab deruxtecan, as well as neuropathy and hematologic adverse events from certain other ADCs, can affect prescribing decisions and duration of therapy. Patient selection and adverse-event monitoring are central clinical requirements.
In less-resourced hospitals, limited specialist monitoring can constrain utilization independently of product availability. Discontinuations and dose reductions also reduce realized treatment exposure relative to the theoretical number of eligible patients.
Uneven Diagnostic and Infusion Infrastructure
HER2 and other target-based treatment pathways require reliable pathology and interpretation of biomarker results. Smaller oncology providers may lack advanced testing, consistent sample logistics or experience with complex treatment sequencing. Geographical differences in diagnostic quality can delay or prevent use even after national approval.
ADCs also require secure distribution and infusion services. Expanding centres and referral networks takes sustained investment; an increase in registered hospitals should not be equated with immediate capacity to provide every indicated medicine.
Complex Manufacturing and Quality Assurance
Conjugation chemistry, high-potency payload containment and product-specific quality controls limit the number of suppliers able to manufacture commercial ADCs reliably. Batch deviations can affect supply and raise costs, while changes to production processes may require comparability assessment and regulatory approval.
Additional regional facilities can alleviate concentration risks over time but bring scale-up expense and qualification schedules. Developers without a commercially validated manufacturing process may be unable to convert positive clinical data into dependable product supply.
Clinical and Commercial Competition From Other Modalities
ADCs compete with immunotherapy, tyrosine kinase inhibitors, endocrine combinations and conventional chemotherapy across different tumour stages. Changing treatment guidelines can redirect eligible patients, while emerging ADCs may compete directly with established products targeting the same antigen.
Comparative efficacy, tolerability, drug availability and payer preference matter more than technology branding. A promising phase III readout may change expectations, but it should not be booked as commercial demand before the relevant national approval and adoption.
Regional Outlook
China: Largest Country Market
China accounts for an estimated 42.9% of Asia Pacific ADC medicine revenue in 2026. The country combines large oncology patient populations with an expanding product registration base and home-grown companies such as RemeGen. Daiichi Sankyo’s October 2026 approvals for Enhertu and Datroway extend available therapeutic indications, while Roche has reported continued demand for Polivy within its Chinese business.
An estimated USD 4.55 billion of sales by 2031 would make China the principal driver of absolute regional value creation. Access will not expand uniformly: pricing agreements, biomarker testing, tertiary-hospital procurement and clinical selection will govern actual use. Domestic manufacturers also introduce additional competition, making net revenue per treatment as important as approval counts.
India: Fastest-Growing Country Market
India’s ADC treatment market is projected to grow by approximately 24.3% annually over 2026–2031, from a smaller initial base than China or Japan. Expanded trastuzumab deruxtecan indications, including a 2026 neoadjuvant approval listed by CDSCO, establish a broader permitted clinical scope. Domestic initiatives around complex biologics and trastuzumab emtansine manufacturing could gradually improve commercial access to selected mature ADC treatments.
Growth remains conditioned by high out-of-pocket expenditure, the concentration of specialist oncology services and uneven molecular-testing availability. The most immediate utilization is expected in major hospital networks, with slower diffusion into lower-tier centres. Local manufacturing capability may influence pricing of certain products but does not automatically make newer proprietary ADCs broadly affordable.
Competitive Landscape
Daiichi Sankyo and AstraZeneca hold a distinctive commercial position through Enhertu and Datroway. Daiichi Sankyo is responsible for manufacturing and supply, while development and commercialization responsibilities are shared outside Japan under the companies’ agreements. Roche’s Kadcyla and Polivy franchise covers mature HER2-positive breast-cancer use and hematologic indications; Pfizer’s Seagen assets include Adcetris and Padcev, with Astellas collaborating on the latter. These franchises compete across separate target populations but increasingly encounter each other through treatment sequencing and therapeutic alternatives.
China has become a substantive originator market. RemeGen’s disitamab vedotin has several approved Chinese indications, demonstrating that domestically developed ADCs can compete as finished therapeutic products rather than only as early-stage licensing opportunities. Other developers and contract manufacturers are building technical capacity, but candidate-stage medicines and third-party manufacturing revenue are not interchangeable with approved regional sales. The strongest commercial participants combine clinical evidence, manufacturing reliability, hospital access and pharmacovigilance.
Competitive advantages differ across treatment segments. Mature products face greater pressure from regimen substitution and eventual follow-on competition, while newer medicines rely on differential efficacy, approved populations and clinical support. Companies operating across Japan, China and India must adapt pricing and reimbursement strategy to local treatment protocols rather than transferring one regional launch model unchanged across all Asia Pacific markets.
Recent Developments
22 October 2026: Daiichi Sankyo announced Chinese approval of Enhertu for previously treated patients with HER2-positive metastatic solid tumours under a tumour-agnostic indication, extending its approved target population.
8 October 2026: Daiichi Sankyo announced approval of Datroway in China for a defined population with metastatic triple-negative breast cancer who are not candidates for PD-1/PD-L1 inhibitor therapy.
8 October 2026: Daiichi Sankyo announced Chinese approval of Enhertu in the adjuvant setting for HER2-positive early breast cancer with residual disease after neoadjuvant treatment.
12 August 2026: Daiichi Sankyo announced approval in China of Enhertu with pertuzumab for first-line treatment of HER2-positive metastatic breast cancer, supporting earlier-line ADC use.
27 July 2026: India’s CDSCO recorded approval of trastuzumab deruxtecan for a specified HER2-positive stage II or III neoadjuvant breast-cancer regimen, widening its authorized use.
23 March 2026: RemeGen announced Chinese approval of an additional disitamab vedotin indication covering HER2-low breast cancer with liver metastases, extending its domestic ADC portfolio.
Market Outlook
Asia Pacific ADC growth through 2031 will increasingly reflect additional treatment-line approvals and broader biomarker-defined oncology pathways. HER2 remains central to spending, but TROP2, Nectin-4, CD30 and other targets give the market a more varied clinical profile. Commercial outcomes will depend on the proportion of eligible patients who actually receive treatment, not on the number of products in research pipelines.
China is likely to contribute the largest absolute revenue increase as international and domestic ADC manufacturers compete for approved indications and reimbursement access. Japan continues to provide an important base for established therapies and high-acuity oncology care, while India offers faster percentage expansion from lower per-patient penetration. Country differences in net price and treatment infrastructure will keep reported regional growth from tracking cancer incidence directly.
The successful suppliers will be those able to combine credible clinical differentiation with reliable manufacture, controlled toxicity and patient access. Price pressure on older medicines may be partly offset by broader adoption of newer ADCs, although the timing of national approvals and reimbursement decisions remains decisive. The market’s value therefore shifts toward medicines supported by robust outcome evidence and repeatable commercial delivery rather than platform claims alone.
Asia Pacific Antibody Drug Conjugates Market Scope:
| Report Metric | Details |
|---|---|
| Total Market Size in 2026 | USD 4.2 billion |
| Total Market Size in 2031 | USD 10.1 billion |
| Forecast Unit | USD Billion |
| Growth Rate | 19.2% |
| Study Period | 2021 to 2031 |
| Historical Data | 2021 to 2024 |
| Base Year | 2025 |
| Forecast Period | 2026 – 2031 |
| Segmentation | Technology, Product Type, Target, Geography |
| Companies |
|
| Customization Scope | 15% Free Customization included with purchase — Request Custom Breakdown → |
| Sample & Data Access | PDF Sample, Excel Databook & Analyst Briefing — Download Free Sample → |
Market Segmentation
By Technology
Cleavable Linker
Non-cleavable Linker
Linkerless
By Product Type
Adcetris
Kadcyla
Others (Including Other Marketed ADCs)
By Target
CD 30
CD 22
HER 2
Others
By Geography
China
India
Japan
South Korea
Taiwan
Thailand
Indonesia
Others
Table of Contents
1. EXECUTIVE SUMMARY
2. MARKET SNAPSHOT
2.1. Market Overview
2.2. Market Definition
2.3. Scope of the Study
2.4. Market Segmentation
3. BUSINESS LANDSCAPE
3.1. Market Drivers
3.1.1. Expansion of Biomarker-Defined Oncology Treatment
3.1.2. Earlier-Line Regulatory Approvals
3.1.3. Development of Regionally Originated ADC Medicines
3.1.4. Growing Access to Specialized Cancer Treatment
3.1.5. Improvement in ADC Manufacturing and Formulation Capability
3.2. Market Restraints
3.2.1. Treatment Cost and Reimbursement Constraints
3.2.2. Safety Monitoring and Treatment Discontinuation
3.2.3. Uneven Diagnostic and Infusion Infrastructure
3.2.4. Complex Manufacturing and Quality Assurance
3.2.5. Clinical and Commercial Competition from Other Modalities
3.3. Market Opportunities
3.4. Porter’s Five Forces Analysis
3.5. Industry Value Chain Analysis
3.6. Policies and Regulations
3.7. Strategic Recommendations
4. TECHNOLOGICAL OUTLOOK
4.1. ADC Linker and Payload Technologies
4.2. Biomarker Selection and Companion Testing
4.3. Conjugation and Manufacturing Processes
4.4. Clinical Development and Safety Management
5. ASIA PACIFIC ANTIBODY-DRUG CONJUGATES MARKET, BY TECHNOLOGY
5.1. Cleavable Linker
5.2. Non-cleavable Linker
5.3. Linkerless
6. ASIA PACIFIC ANTIBODY-DRUG CONJUGATES MARKET, BY PRODUCT TYPE
6.1. Adcetris
6.2. Kadcyla
6.3. Others (Including Other Marketed ADCs)
7. ASIA PACIFIC ANTIBODY-DRUG CONJUGATES MARKET, BY TARGET
7.1. CD 30
7.2. CD 22
7.3. HER 2
7.4. Others
8. ASIA PACIFIC ANTIBODY-DRUG CONJUGATES MARKET, BY GEOGRAPHY
8.1. China
8.2. India
8.3. Japan
8.4. South Korea
8.5. Taiwan
8.6. Thailand
8.7. Indonesia
8.8. Others
9. COMPETITIVE ENVIRONMENT AND ANALYSIS
9.1. Major Players and Strategy Analysis
9.2. Market Share Analysis
9.3. Mergers, Acquisitions, Agreements and Collaborations
9.4. Competitive Dashboard
10. COMPANY PROFILES
10.1. Daiichi Sankyo Company, Limited
10.2. AstraZeneca PLC
10.3. F. Hoffmann-La Roche Ltd.
10.4. Pfizer Inc.
10.5. Astellas Pharma Inc.
10.6. Takeda Pharmaceutical Company Limited
10.7. Gilead Sciences, Inc.
10.8. RemeGen Co., Ltd.
10.9. Kelun-Biotech Biopharmaceutical Co., Ltd.
10.10. Zydus Lifesciences Limited
11. APPENDIX
11.1. Currency
11.2. Assumptions
11.3. Base and Forecast Years Timeline
11.4. Key Benefits for Stakeholders
11.5. Research Methodology
11.6. Abbreviations





Frequently asked questions
What is the projected market value of the Asia Pacific ADC market by 2031?
The Asia Pacific Antibody Drug Conjugates Market is projected to reach USD 10.1 billion by 2031.
What is the anticipated CAGR for the Asia Pacific ADC market (2026-2031)?
The Asia Pacific Antibody Drug Conjugates Market is projected to expand at a CAGR of 19.2%.
Which specific ADC medicine segment leads regional sales in 2026?
HER2-directed medicines represent approximately 42% of 2026 regional ADC sales.
Which country leads regional spending, and which has the fastest growth?
China leads regional spending; India has the fastest modeled growth trajectory.
What linker design dominates commercially established ADC therapies in the region?
Cleavable-linker designs dominate commercially established therapies and new launches.
What factors restrict patient access to ADCs in the Asia Pacific market?
Net pricing, reimbursement, and ILD monitoring constrain patient access.
Cite this report
Knowledge Sourcing Intelligence. (Oct 2026). Asia Pacific Antibody Drug Conjugates Market - Strategic Insights and Forecasts (2026-2031). https://www.knowledge-sourcing.com/report/asia-pacific-antibody-drug-conjugates-market