
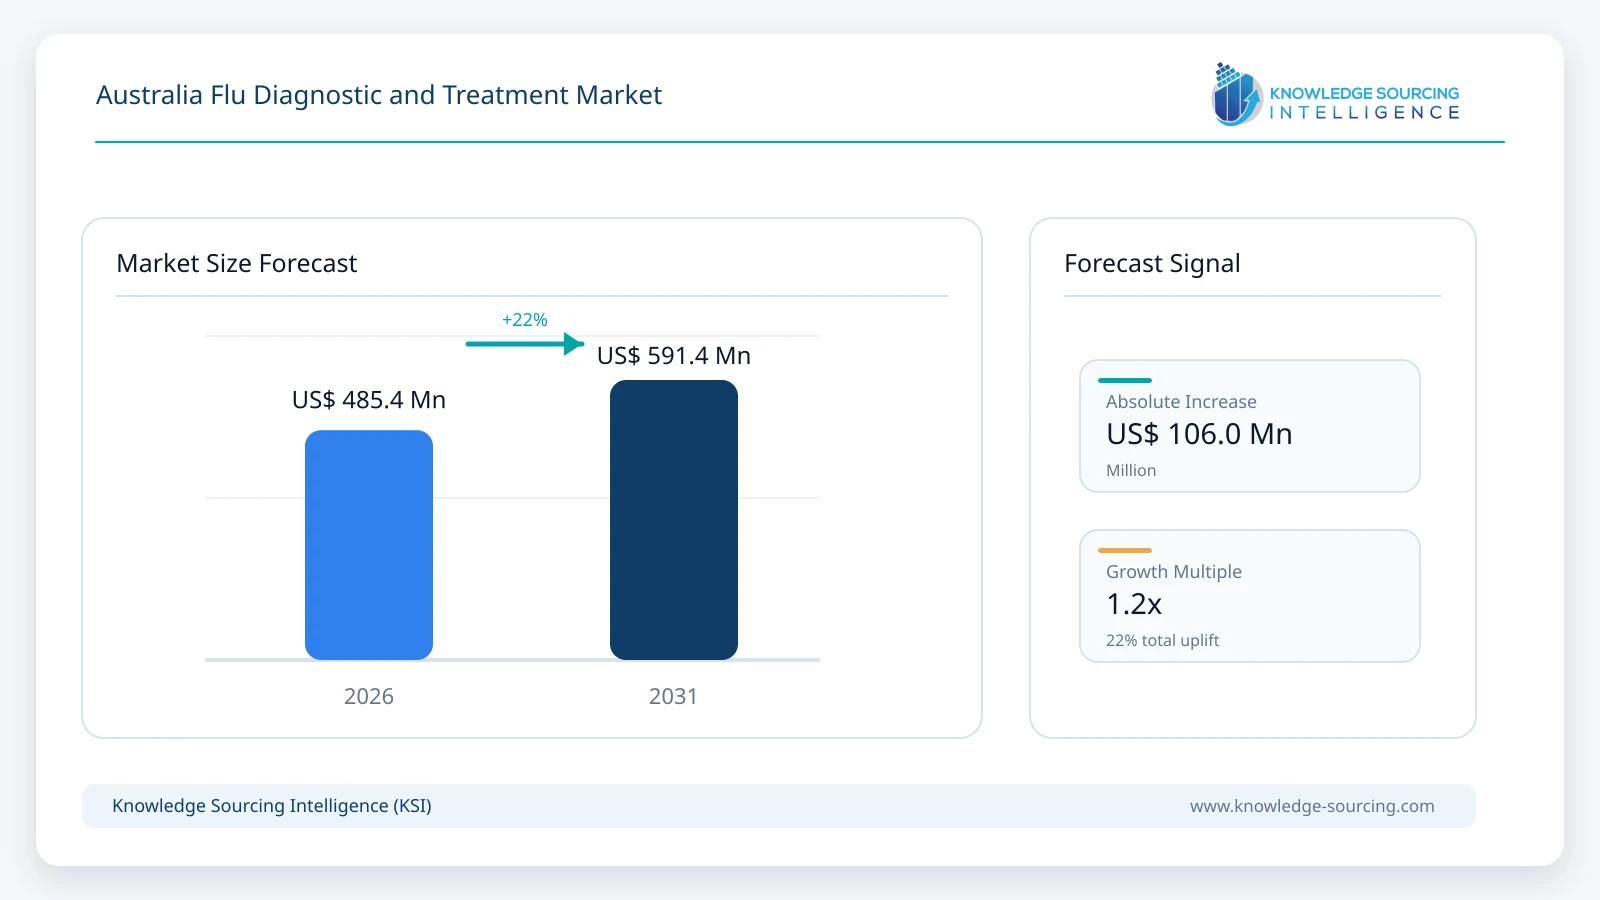
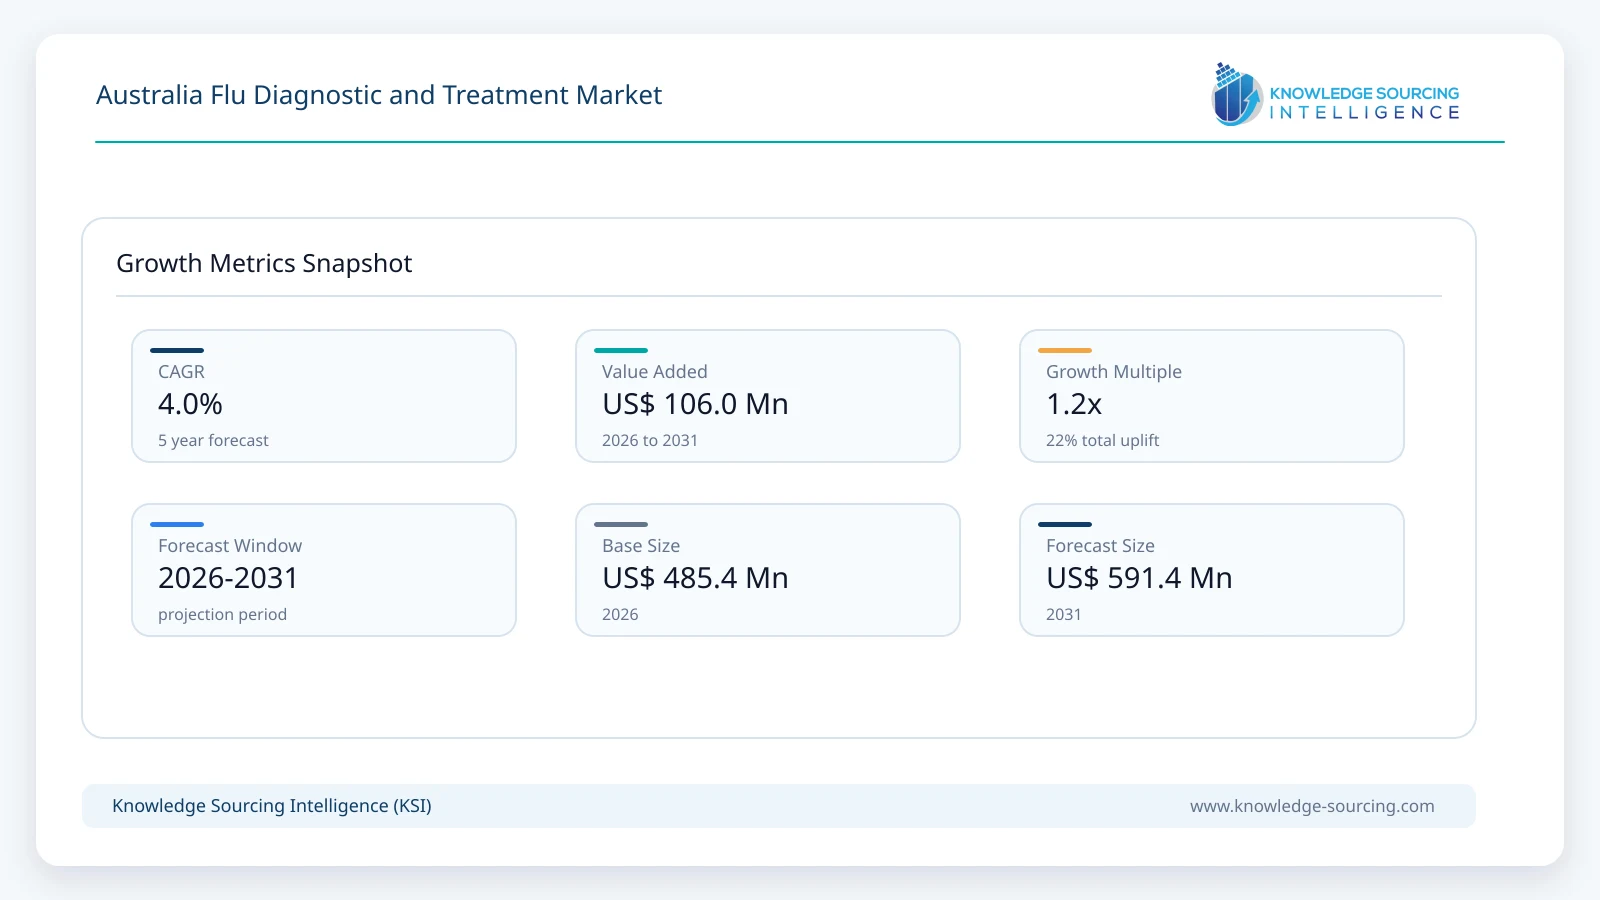
The Australian flu diagnostic and treatment market is estimated at USD 485.45 million in 2026 and is forecast to reach approximately USD 591.41 million in 2031, representing a CAGR of 4.0% over the forecast period.
Highlights:
- 1Seasonal influenza activity creates recurring demand across diagnostics, antivirals, hospitals, laboratories, and pharmacies.
- 2Influenza A remains commercially important because it drives substantial clinical testing and surveillance requirements.
- 3Molecular and multiplex testing supports faster differentiation of influenza from other respiratory infections.
- 4Hospitals and pathology laboratories place greater emphasis on turnaround time, workflow fit, and assay breadth.
- 5Self-testing expands access but remains subject to Australia’s risk-based IVD regulatory framework.
- 6Antiviral availability, seasonal supply planning, and early treatment remain important commercial considerations.
Key Highlights
Market Overview
The need for flu diagnostics and treatment is seasonal, but purchasing decisions are not based only on case volumes. Hospitals, pathology providers, clinics, pharmacies, and public-health services also consider turnaround time, clinical utility, test performance, supply reliability, workflow requirements, and treatment timing.
Australian respiratory surveillance shows why influenza testing must be considered within a wider respiratory-disease setting. Influenza-like illness can be caused by influenza, respiratory syncytial virus, rhinovirus, parainfluenza, human metapneumovirus, SARS-CoV-2, and other pathogens. The Australian Centre for Disease Control uses laboratory surveillance, primary-care testing, hospital data, virology, and other sources to track respiratory activity and its effect on the health system.
This environment supports demand for tests that can distinguish influenza from other respiratory infections when the result affects treatment, referral, infection control, or patient management. Multiplex molecular systems are particularly relevant because they can identify several respiratory pathogens within one workflow. Roche’s Australian respiratory portfolio, for example, includes an automated multiplex molecular assay that detects influenza A and B alongside other respiratory viruses.
Treatment demand remains concentrated around patients at higher risk of complications and patients who can benefit from early antiviral therapy. Australia’s therapeutic framework includes neuraminidase inhibitors such as oseltamivir and cap-dependent endonuclease inhibition through baloxavir. The commercial environment therefore links diagnostics, clinical decision-making, medicine availability, and seasonal preparedness rather than treating testing and treatment as separate markets.
Key Market Indicators
Indicator | Latest Evidence | Commercial Meaning |
Influenza surveillance | Australian respiratory surveillance combines community, laboratory, hospital, virological, and public-health data. | Suppliers must respond to changes in disease activity across several care settings rather than relying on a single demand signal. |
Respiratory pathogen differentiation | Australian sentinel surveillance uses laboratory testing to identify influenza and other respiratory pathogens. | Diagnostic value increases when results can distinguish influenza from clinically similar infections. |
Influenza A and B testing | Australian diagnostic products include assays designed to detect influenza A and B, often alongside RSV and other respiratory pathogens. | Multiplex capability can improve the value of existing diagnostic platforms and laboratory workflows. |
Self-testing availability | Seasonal influenza self-testing IVDs can be supplied in Australia when they meet applicable regulatory requirements. | Consumer access creates an additional channel for diagnostic suppliers while increasing performance and labelling obligations. |
IVD market access | IVDs generally require appropriate conformity evidence and ARTG inclusion before legal supply in Australia. | Regulatory readiness remains an important barrier to commercial entry and product expansion. |
Antiviral treatment options | Australian regulation includes both neuraminidase inhibitor and cap-dependent endonuclease inhibitor therapies. | Treatment suppliers compete within a regulated market where patient eligibility, timing, and clinical guidance influence demand. |
Market Drivers
Clinical need to distinguish influenza from other respiratory infections. Influenza-like illness does not identify the causative pathogen on its own. Australian surveillance testing routinely detects several respiratory viruses among people presenting with influenza-like illness, which increases the clinical value of tests that can separate influenza from RSV, SARS-CoV-2, and other pathogens. The commercial benefit is strongest where diagnosis changes antiviral treatment, hospital placement, infection-control measures, or the need for further testing.
Hospital demand for actionable respiratory diagnostics. Hospitals face different testing requirements from community pharmacies or low-acuity clinics. Inpatient settings need results that can support treatment decisions, cohorting, infection prevention, and patient flow. This favours molecular platforms that provide influenza detection together with other respiratory targets. Suppliers can therefore compete on workflow speed, automation, assay breadth, instrument compatibility, and service support rather than test sensitivity alone.
Expansion of multiplex respiratory testing. Roche, Cepheid, and other suppliers have developed respiratory assays that combine influenza detection with additional viral targets. Roche’s Australian cobas Respiratory flex assay provides multiplex molecular testing for influenza A, influenza B, and other respiratory viruses, while Cepheid markets Xpert Xpress Flu/RSV and broader respiratory panels in Australia. These products address a practical buyer problem: the need to identify the relevant pathogen when several respiratory infections circulate at the same time.
Recurring vaccination and high-risk patient management. Australian immunisation policy recommends annual influenza vaccination and provides public funding for specified groups at higher risk of severe disease. Vaccination reduces preventable illness but does not eliminate diagnostic or treatment demand. Seasonal vaccination programs also require manufacturers, distributors, pharmacies, and healthcare providers to manage recurring supply, administration, and patient-engagement requirements, keeping influenza within the annual planning cycle of the healthcare system.
Greater value is placed on rapid results in near-patient care. Point-of-care molecular testing can reduce the delay between specimen collection and clinical decision-making. Cepheid’s Australian respiratory portfolio includes near-patient tests for influenza A, influenza B, and RSV, reflecting demand from settings where sending specimens to a central laboratory may delay treatment decisions. The commercial opportunity is strongest when faster results change clinical management rather than simply providing additional information.
Market Restraints and Challenges
Seasonal demand creates uneven utilisation. Influenza testing and treatment demand varies sharply with seasonal transmission, vaccination coverage, population behaviour, and the circulation of other respiratory pathogens. Diagnostic suppliers must maintain product availability during periods of high activity while avoiding excessive inventory when testing volumes fall. This affects reagent planning, distributor inventories, instrument utilisation, workforce scheduling, and commercial forecasting. The Australian CDC’s recurring respiratory surveillance reports reinforce the need to monitor seasonal conditions continuously rather than rely on fixed annual assumptions.
Regulatory requirements increase the cost and time needed for market entry. IVD suppliers must meet Australian safety, quality, and performance requirements, provide appropriate conformity assessment evidence, and obtain ARTG inclusion unless an exemption applies. TGA assessment can involve technical documentation, conformity evidence, and application audits. The risk-based framework also means that manufacturers must align their evidence with the intended purpose and classification of the product.
Molecular testing can face utilisation and cost constraints. Molecular platforms offer clinical value when rapid and accurate pathogen identification affects treatment or patient management. Their economics become less attractive when testing volumes are low or when a result does not change the clinical decision. Buyers must consider instruments, reagents, maintenance, staff capability, workflow integration, and service arrangements. Lower-acuity settings may therefore continue to use simpler diagnostic formats where their clinical and operational needs are adequately met.
Supply continuity remains important during seasonal surges. Influenza demand can rise quickly when community transmission increases, creating pressure on test inventories and antiviral supply. Australian regulatory information has previously recorded supply constraints affecting oseltamivir presentations. Pharmacy and healthcare buyers therefore have an incentive to favour suppliers with dependable distribution, contingency planning, and the ability to respond to changes in seasonal demand. The issue is especially relevant when treatment needs rise faster than routine procurement cycles.
Self-testing carries additional performance and risk-management requirements. Australia permits supply of seasonal influenza self-tests within its IVD framework, but manufacturers must meet performance, labelling, and risk-mitigation expectations. TGA guidance places particular attention on clinical sensitivity, specificity, intended use, instructions, warnings, and appropriate interpretation of results. This limits the ability of suppliers to treat self-testing as a simple consumer product category and increases the importance of regulatory and post-market capabilities.
Major Segment Analysis
Molecular Tests / NAATs
Molecular tests and nucleic acid amplification tests are commercially important because they provide the analytical performance and pathogen differentiation needed in hospital and laboratory settings. Australian respiratory surveillance uses laboratory methods to identify circulating pathogens, while clinical diagnostic suppliers increasingly combine influenza detection with other respiratory targets. This supports demand for platforms that can fit into existing laboratory or near-patient workflows rather than operate as isolated influenza systems.
Buyer priorities vary by setting. Hospitals generally value rapid results, reliable operation, and respiratory-pathogen differentiation, while reference laboratories place greater emphasis on automation, throughput, assay breadth, and workflow consistency. Near-patient buyers place greater weight on ease of operation and turnaround time. Roche and Cepheid illustrate this distinction through automated laboratory systems and on-demand respiratory platforms.
The main limitation is economic. Molecular systems require platform investment and recurring consumables, so utilisation must justify the total cost of ownership. Suppliers that broaden respiratory menus can improve platform economics by allowing the same system to address several diagnostic needs rather than relying on influenza testing alone.
Competitive Landscape
The Australian flu diagnostic and treatment market is technology-led, procurement-driven, and service-dependent. Competition is not limited to individual influenza assays. Suppliers compete through installed instrument bases, respiratory assay menus, automation, turnaround time, platform compatibility, distribution, technical support, regulatory capability, and customer relationships.
The companies covered in the market include Abbott, Roche Diagnostics, BD, bioMérieux, Cepheid, Thermo Fisher Scientific, Hologic, QuidelOrtho, AusDiagnostics, and Siemens Healthineers. Their competitive positions differ according to laboratory scale, point-of-care capability, respiratory assay breadth, platform reach, and existing healthcare relationships.
Roche and Cepheid have clear respiratory molecular portfolios in Australia. Roche’s cobas Respiratory flex combines influenza detection with broader respiratory pathogen testing, while Cepheid offers Flu/RSV and broader respiratory assays through its GeneXpert ecosystem. BD has expanded the respiratory menu available on its BD MAX molecular platform through its collaboration with Certest Biotec.
Hologic competes through automated molecular respiratory testing, while bioMérieux extends the BIOFIRE ecosystem into respiratory and environmental surveillance. QuidelOrtho’s decision to refocus its molecular diagnostics strategy and pursue LEX Diagnostics also shows how platform economics and product development priorities can alter competitive positioning.
Recent Developments
April 2026: Western Australia expanded Spotfire rapid respiratory testing across selected emergency departments, enabling approximately 15-minute detection of influenza and other pathogens, supporting faster diagnosis and treatment during winter demand.
March 2026: TGA confirmed seven influenza vaccines for Australia’s 2026 season, including AstraZeneca’s FluMist, the first intranasal influenza vaccine new to the Australian market for children aged two-to-seventeen years.
December 2025: CSL Seqirus officially opened its A$1-billion cell-based vaccine manufacturing facility in Tullamarine, Melbourne, supplying seasonal and pandemic influenza vaccines domestically under a long-term government supply agreement thereafter.
June 2025: QuidelOrtho announced plans to acquire LEX Diagnostics after regulatory clearance and discontinue development of its Savanna platform. The decision shows how clinical performance, investment needs, and platform economics are influencing molecular diagnostics portfolios.
Regulatory and Policy Environment
Australia’s Therapeutic Goods Administration regulates IVDs through a risk-based framework that considers the intended purpose and potential consequences of incorrect results. IVDs generally need to meet safety, quality, and performance requirements and be included in the Australian Register of Therapeutic Goods before legal supply. Manufacturers and sponsors must provide suitable conformity evidence, while higher-risk products can face more extensive assessment.
The framework also covers point-of-care and self-testing products. TGA permits certain seasonal influenza self-tests, subject to the applicable classification and regulatory requirements. Manufacturers must address clinical performance and risk mitigation, while product labels and advertising must provide accurate information about intended use, instructions, warnings, and appropriate interpretation.
Post-market responsibilities remain relevant after product approval. Sponsors must maintain ARTG information, monitor safety, report relevant issues, and manage product changes. This creates an ongoing compliance burden for suppliers and increases the value of regulatory teams with experience in Australian IVD requirements.
Therapeutic products are regulated separately from diagnostic devices. TGA-approved influenza treatments include oseltamivir and baloxavir, with prescribing and patient eligibility conditions linked to the registered indications. Baloxavir acts through inhibition of the influenza polymerase complex and is registered for treatment of uncomplicated influenza in specified patients.
Public-health policy also affects the market through annual influenza vaccination recommendations, surveillance programs, laboratory monitoring, and guidance for higher-risk populations. The commercial result is a market where diagnostic suppliers, pharmaceutical companies, healthcare providers, distributors, and regulators remain closely connected.
Outlook and Strategic Implications
Over the forecast period, market performance will depend on the interaction between seasonal influenza activity, respiratory-virus co-circulation, diagnostic practices, antiviral access, and healthcare capacity. The Australian CDC’s surveillance model indicates that demand conditions can change across community, hospital, laboratory, and public-health settings. Suppliers therefore need flexible supply planning rather than a fixed seasonal sales model.
Molecular diagnostics should remain commercially relevant where rapid pathogen identification affects treatment, patient flow, infection control, or laboratory surveillance. Multiplex testing has an additional advantage because the same platform can address influenza alongside other respiratory infections. However, high instrument and consumable costs will continue to favour settings where testing volumes and clinical value justify molecular workflows.
The competitive environment is likely to reward suppliers that combine reliable assays with strong platforms, local regulatory capability, distribution, service, and workflow integration. Buyers will increasingly assess the full operating cost of a diagnostic system rather than the price of an individual test. This favours platforms that can support several respiratory applications and maintain useful utilisation outside peak influenza periods.
For pharmaceutical suppliers and distributors, antiviral availability remains a central consideration. Early treatment depends on timely access, appropriate prescribing, and recognition of patients at higher risk of complications. Supply resilience therefore has commercial value during periods when seasonal activity changes quickly.
For diagnostic manufacturers, Australia offers a regulated market in which product performance, evidence quality, post-market monitoring, and supply reliability influence market access. Suppliers that align molecular diagnostics, multiplex testing, self-testing, surveillance capability, and clinical workflow requirements should be better positioned to capture demand across hospitals, laboratories, clinics, pharmacies, and selected home-care settings.
Australia Flu Diagnostic and Treatment Market Scope:
| Report Metric | Details |
|---|---|
| Total Market Size in 2026 | USD 485.45 million |
| Total Market Size in 2031 | USD 591.41 million |
| Forecast Unit | USD million |
| Growth Rate | 4.0% |
| Study Period | 2021 to 2031 |
| Historical Data | 2021 to 2024 |
| Base Year | 2025 |
| Forecast Period | 2026 – 2031 |
| Segmentation | Type of Flu, Offering, Age Group, End-User |
| Companies |
|
| Customization Scope | 15% Free Customization included with purchase — Request Custom Breakdown → |
| Sample & Data Access | PDF Sample, Excel Databook & Analyst Briefing — Download Free Sample → |
Market Segmentation
BY TYPE OF FLU
Influenza A
H1N1
H3N2
Other/Novel Influenza A Subtypes
Influenza B
BY OFFERING
Diagnostics
Rapid Influenza Diagnostic Tests (RIDTs)
Molecular Tests / NAATs
Digital Immunoassays
Multiplex Respiratory Panels
Others
Therapeutics
Neuraminidase Inhibitors
Cap-Dependent Endonuclease Inhibitors
Others
BY AGE GROUP
0–14 Years
15–64 Years
?65 Years
BY END-USER
Hospitals
Diagnostic Centers and Reference Laboratories
Clinics and Physician Offices
Pharmacies
Home Care / Self-Testing
Others
Table of Contents
1. INTRODUCTION
1.1. Market Overview
1.2. COVID-19 Impact
1.3. Market Definition
1.4. Market Segmentation
2. RESEARCH METHODOLOGY
2.1. Research Data
2.2. Assumptions
3. EXECUTIVE SUMMARY
3.1. Research Highlights
4. MARKET DYNAMICS
4.1. Market Drivers
4.2. Market Restraints
4.3. Market Opportunities
4.4. Porters Five Forces Analysis
4.4.1. Bargaining Power of Suppliers
4.4.2. Bargaining Power of Buyers
4.4.3. Threat of New Entrants
4.4.4. Threat of Substitutes
4.4.5. Competitive Rivalry in the Industry
4.5. Industry Value Chain Analysis
5. AUSTRALIA FLU DIAGNOSTIC AND TREATMENT MARKET ANALYSIS, BY TYPE OF FLU
5.1. Introduction
5.2. Influenza A
5.2.1. H1N1
5.2.2. H3N2
5.2.3. Other/Novel Influenza A Subtypes
5.3. Influenza B
6. AUSTRALIA FLU DIAGNOSTIC AND TREATMENT MARKET ANALYSIS, BY OFFERING
6.1. Introduction
6.2. Diagnostics
6.2.1. Rapid Influenza Diagnostic Tests (RIDTs)
6.2.2. Molecular Tests / NAATs
6.2.3. Digital Immunoassays
6.2.4. Multiplex Respiratory Panels
6.2.5. Others
6.3. Therapeutics
6.3.1. Neuraminidase Inhibitors
6.3.2. Cap-Dependent Endonuclease Inhibitors
6.3.3. Others
7. AUSTRALIA FLU DIAGNOSTIC AND TREATMENT MARKET ANALYSIS, BY AGE GROUP
7.1. Introduction
7.2. 0-14 Years
7.3. 15-64 Years
7.4. >=65 Years
8. AUSTRALIA FLU DIAGNOSTIC AND TREATMENT MARKET ANALYSIS, BY END-USER
8.1. Introduction
8.2. Hospitals
8.3. Diagnostic Centers and Reference Laboratories
8.4. Clinics and Physician Offices
8.5. Pharmacies
8.6. Home Care / Self-Testing
8.7. Others
9. COMPETITIVE ENVIRONMENT AND ANALYSIS
9.1. Major Players and Strategy Analysis
9.2. Emerging Players and Market Lucrativeness
9.3. Mergers, Acquisitions, Agreements, and Collaborations
9.4. Vendor Competitiveness Matrix
10. COMPANY PROFILES
10.1. Abbott
10.2. Roche Diagnostics / F. Hoffmann-La Roche Ltd.
10.3. BD
10.4. BioMérieux
10.5. Cepheid
10.6. Thermo Fisher Scientific Inc.
10.7. Hologic, Inc.
10.8. QuidelOrtho Corporation
10.9. AusDiagnostics
10.10. Siemens Healthineers
List of Figures
List of Tables





Frequently asked questions
What is the Australian flu market size projected for 2031?
The Australia Flu Diagnostic and Treatment Market is forecast to reach USD 591.41 million in 2031.
What is the CAGR for the Australian flu market from 2026-2031?
The Australia Flu Diagnostic and Treatment Market is projected to grow at a 4.0% CAGR.
What are the primary drivers for the Australian flu market?
Seasonal influenza activity drives recurring demand across multiple sectors.
Which diagnostic methods are gaining importance in Australia?
Molecular and multiplex testing support faster differentiation of infections.
What key factors influence flu diagnostic and treatment purchasing?
Turnaround time, clinical utility, and supply reliability are important factors.
What is the role of antivirals in Australia's flu market?
Antiviral availability and early treatment are crucial commercial considerations.
Cite this report
Knowledge Sourcing Intelligence. (Oct 2026). Australia Flu Diagnostic and Treatment Market - Strategic Insights and Forecasts (2026-2031). https://www.knowledge-sourcing.com/report/australia-flu-diagnostic-and-treatment-market