
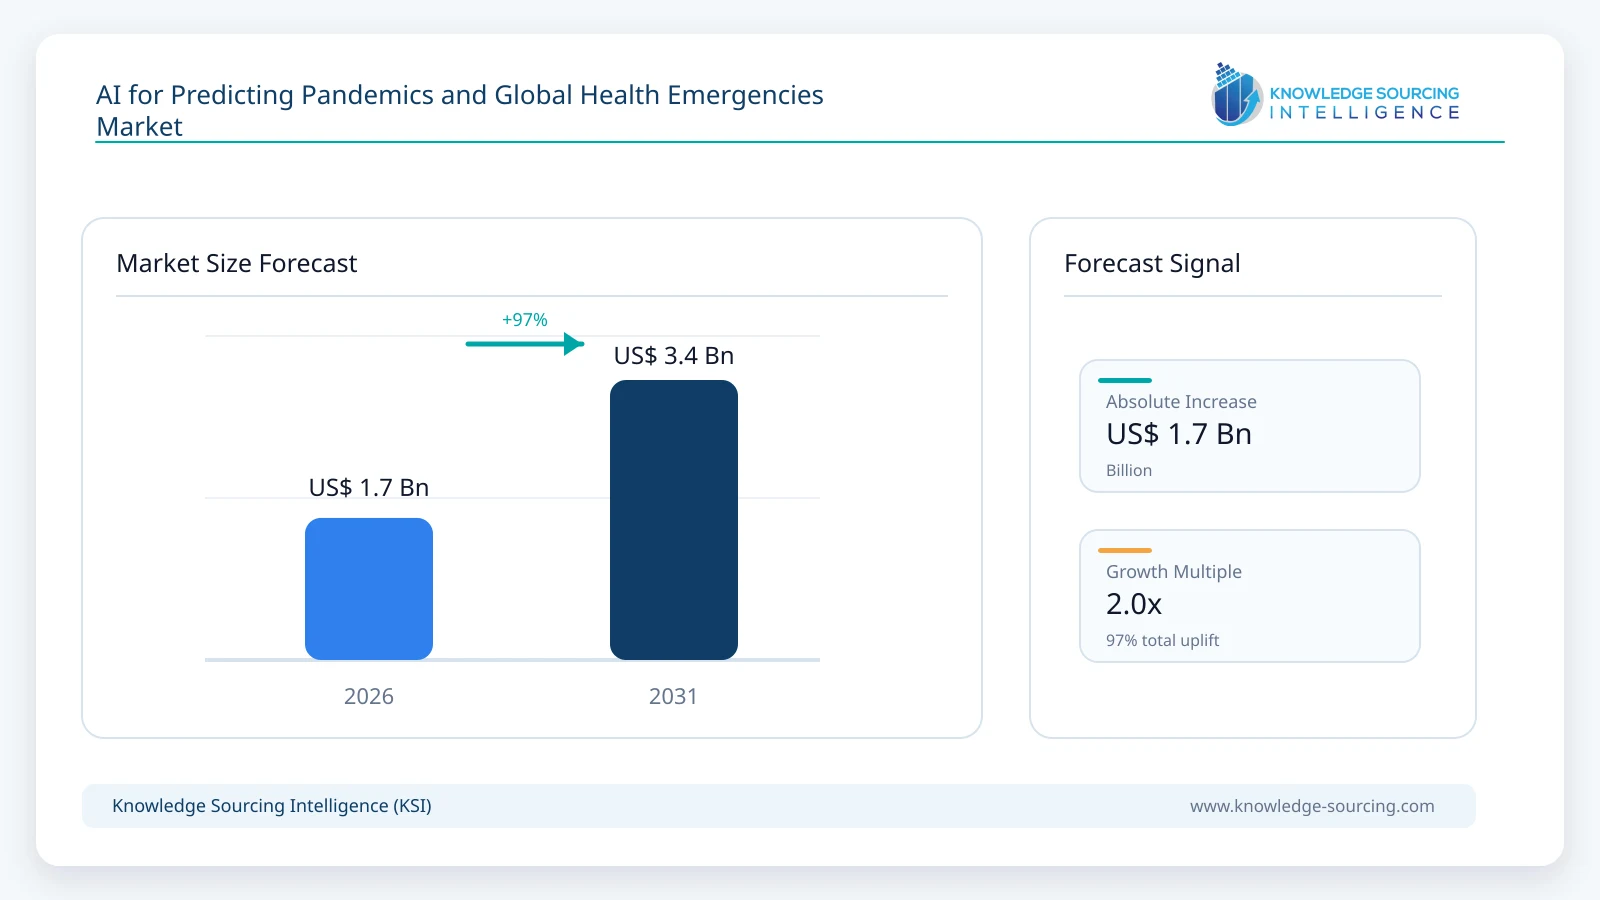
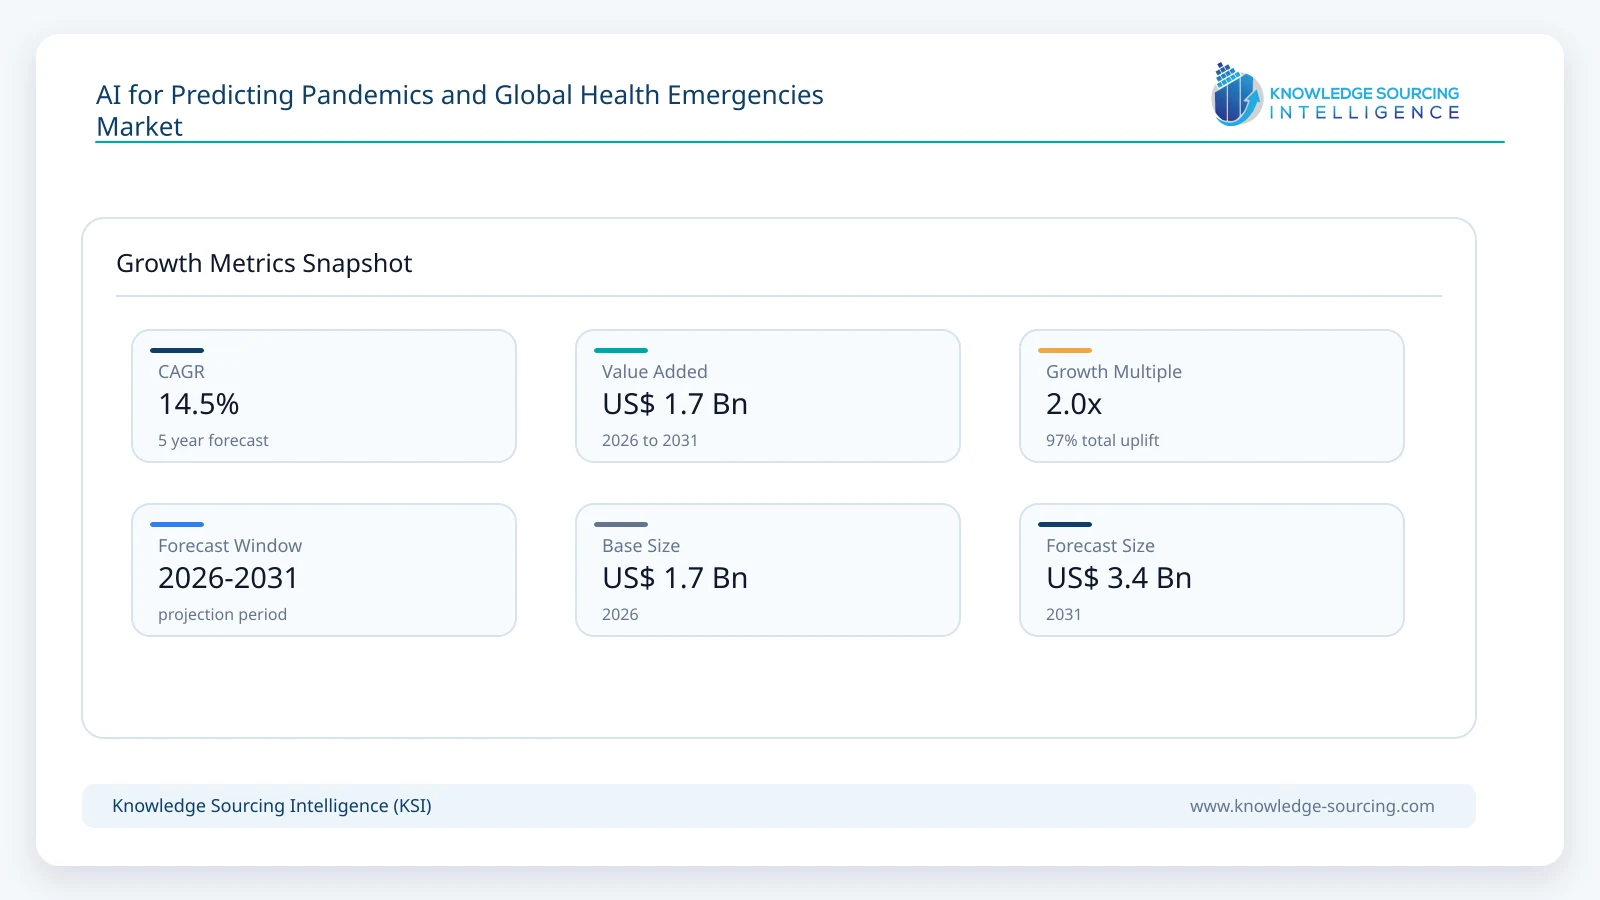
The AI for Predicting Pandemics and Global Health Emergencies Market is expected to expand at a CAGR of approximately 14.5%, reaching USD 3.35 billion in 2031 from USD 1.70 billion in 2026.
Highlights:
- 1Software contributes approximately 65% of estimated 2026 market value, reflecting recurring demand for pathogen intelligence, detection models and continuously updated forecasts.
- 2Government and public-health agencies account for an estimated 54% of 2026 demand, with tender requirements increasingly focused on auditability and operational response.
- 3Cloud-based deployment supports multilingual event scanning and cross-border coordination, while sensitive clinical data may still require protected or locally controlled environments.
- 4Specialist companies are differentiating through disease-specific forecasts and environmental surveillance, rather than generic AI capabilities alone.
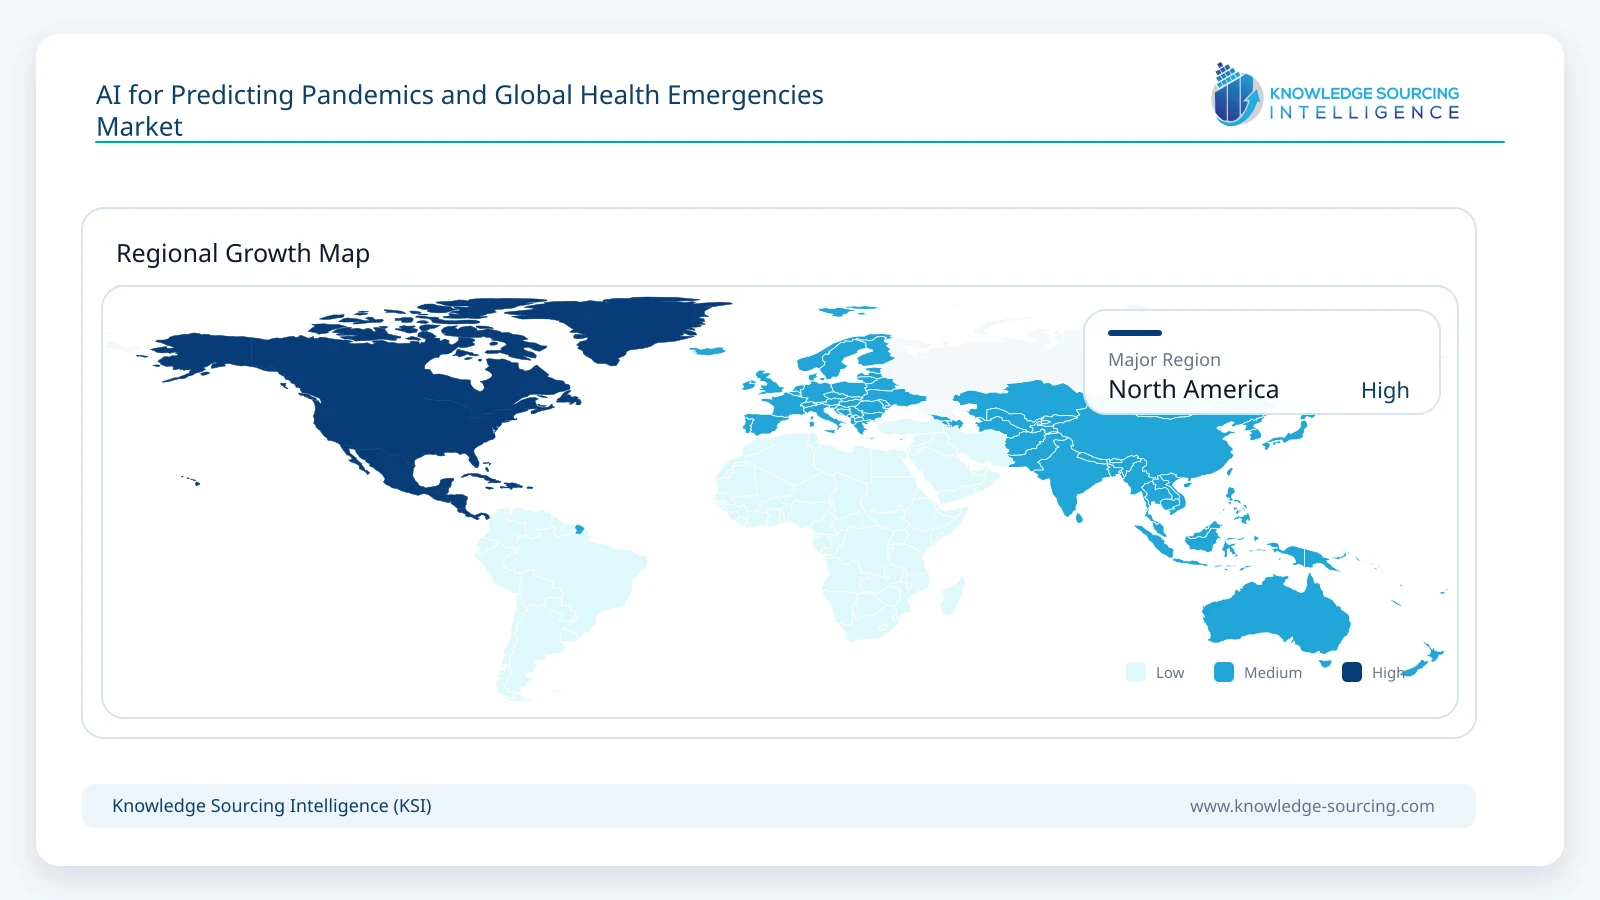
- 5North America retains the largest starting revenue base, while Asia Pacific is expected to record the fastest expansion in the regional model.
- 6Publicly operated surveillance systems remain influential, requiring commercial suppliers to prove additional accuracy, integration capability and decision value.
Commercial offerings in this market include outbreak detection and forecasting applications, continuous epidemiological intelligence subscriptions, risk-analysis services and the software engineering required to link these capabilities with approved health datasets. Hardware is relevant when directly attributable to surveillance sensing or dedicated analytical deployments; complete hospital IT estates, generic compute capacity, laboratory testing turnover and the value of publicly funded health programmes are not interchangeable with AI surveillance sales.
The same product can support different operational decisions. BlueDot supplies geographically specific influenza and vector-borne disease forecasts, while Airfinity combines pathogen risk analysis with disease-burden forecasts and response intelligence. Public institutions use comparable analytical methods for outbreak verification, yet many tools, including WHO EIOS and Boston Children’s Hospital’s HealthMap, are publicly accessible rather than conventional commercial licences.
The buyers most likely to pay recurring fees are public-health authorities, regional emergency coordination centres, pharmaceutical businesses and research organisations with defined surveillance or countermeasure-planning mandates. Procurement involves epidemiologists and data-governance teams as well as IT specialists. Forecast accuracy is judged against real outbreaks, with security, source provenance and a path from alert to intervention influencing renewal decisions.
Market Overview
WHO’s Epidemic Intelligence from Open Sources network now informs a large international community of public-health analysts. The 2025 release of EIOS 2.0 introduced additional data sources and AI-enabled capabilities, strengthening the institutional baseline for multilingual signal screening. Commercial providers operate alongside these publicly funded systems and must justify their fees through distinctive forecasts, disease expertise, integration support, or contracted service levels.
Confirmed cases arrive later than some early indicators. Wastewater results can expose shifts in community circulation, news reports can locate clusters before routine notification catches up, and genomic data can flag unfamiliar variants. None is reliable alone. Models built on these streams must account for changes in testing frequency, reporting behaviour and pathogen prevalence, or they risk treating a surveillance artefact as an emerging outbreak.
Procurement generally adds specialist models and secure integrations to an existing surveillance estate rather than replacing the national reporting system outright. A buyer must also decide who verifies an alert, who can access clinical and mobility information, and which data are shared across borders. Deployment success consequently depends on epidemiological workflows and permissions at least as much as the underlying prediction engine.
Market Trends
Open-source intelligence is being rebuilt for faster human verification
WHO’s EIOS 2.0 release in October 2025 expanded data inputs and introduced AI-supported functions for epidemic intelligence. ECDC followed in May 2026 with episomer, a replacement for epitweetr that monitors disease-related social-media patterns by subject, geography and time. Both initiatives address the same operational bottleneck: analysts need to triage high volumes of weak signals without discarding a rare but important warning.
Natural-language processing, language translation and event de-duplication are commercially relevant where a health authority lacks the capacity to maintain such pipelines internally. However, automated extraction is not verification. Traceable source links, confidence grading and expert escalation remain essential because public reports can be inaccurate, recycled or intentionally misleading.
Environmental sampling gains weight alongside case notification
The CDC described wastewater surveillance in April 2026 as an early-warning input that can be combined with emergency-department and other public-health data. The methodology matters commercially because wastewater coverage can reveal local pathogen circulation when clinical testing falls. Models must normalize laboratory methods and sampling intervals before the series can inform a forecast or a geographic alert.
Environmental and genomic data also introduce specialist integration requirements. Laboratory sample metadata, collection-site geography and changes in assay sensitivity have to remain visible to model users. Providers selling a ready-made dashboard without these controls face a difficult validation process, particularly where early decisions affect vaccine stockpiles or public messaging.
Forecast products are moving toward disease- and location-specific decisions
BlueDot publishes forecasts for seasonal influenza at state or provincial resolution and longer-horizon analysis of mosquito-borne risks. Airfinity offers outbreak risk intelligence and respiratory disease forecasts for planning interventions and demand. These are not interchangeable products: a forecast of influenza admissions for a hospital network serves a different planning horizon from a map of vector expansion or a high-consequence pathogen alert.
Procurement increasingly tests whether the output changes a real decision. Health agencies may need lead time, uncertainty intervals and geographic granularity; pharmaceutical companies examine countermeasure demand and clinical-trial exposure. Suppliers with validated disease models can command specialist engagements even when broader cloud infrastructure is supplied by another company.
Interoperability becomes part of epidemic preparedness
The WHO African Region reported continued expansion of EIOS and use of machine-learning signal classification in its October 2026 intelligence reporting. ECDC separately demonstrated its planned Epi+ open-source surveillance platform in April. Both developments reinforce demand for data systems that work across local, national and regional institutions rather than generate isolated dashboards.
Data dictionaries, case definitions, laboratory message standards and identity permissions affect whether an algorithm can consume operational information. Implementation services therefore remain part of many contracts. A supplier that cannot explain how an alert enters the authorised response workflow may win a demonstration but struggle to scale beyond a pilot.
Public-health AI is moving under stronger operational governance
WHO’s October 2026 Pandemic Hub strategy targets earlier threat recognition and trusted digital foundations. The requirement is not simply for more prediction. Models used in health emergencies require independent review, version tracking, security, and a clear allocation of responsibility when an alert is wrong or incomplete.
Hybrid analytical processes are likely to persist. Automated screening can shortlist anomalies and correlate disparate sources, but public-health experts must evaluate case definitions, confirmatory evidence and local consequences. This limits fully autonomous operation while opening services demand for model monitoring, training and validation.
Segment Analysis
By Component: Software
Software accounts for the largest identifiable commercial product pool, with modeled revenue of approximately USD 2.26 billion by 2031. Its value lies in continuous ingestion of clinical and open-source information, multilingual entity extraction, pattern detection and risk forecasts, rather than a fixed installation of analytical code. BlueDot and Airfinity show how maintained disease models, geographical coverage and expert review can be sold as ongoing intelligence services.
Forecast revisions and source curation are part of the product customers renew, particularly when pathogen characteristics or testing practice change. Separate services remain necessary for systems integration, performance testing and interpretation, but they do not substitute for the continuously maintained software layer. Instrumentation and dedicated sensing hardware form a smaller, more project-specific revenue group.
By Deployment Mode: Cloud-Based
An estimated 16.2% annual growth rate places cloud-based deployment among the more dynamic market categories through 2031. Continuous open-source scanning and the processing of genomic or environmental signals create uneven compute demand, making elastic capacity and shared analytical environments valuable. Distributed public-health teams also need a consistent risk picture during emergencies, even if the evidence originates with different agencies.
Sovereignty requirements still influence architecture. Identifiable records, sensitive geolocation information and pathogen sequence data may need controlled hosting, pseudonymisation or permission-based access. A supplier must preserve traceability when data flow between cloud analytics and nationally managed surveillance systems; low infrastructure costs alone will not settle a public-sector procurement decision.
By Application: Outbreak Prediction and Detection
Outbreak Prediction & Detection is modeled to reach approximately USD 1.12 billion in 2031. Its purchasing case rests on converting scattered early signals into an earlier, verifiable investigation: unusual laboratory activity, clinical syndromes, wastewater results, and local reports may each precede an accepted case count. Event-ranking and geographical risk models can help epidemiologists assess where verification effort is most urgent, but they cannot replace field investigation.
Operational performance is judged by useful warning lead time, false-alert burden and evidence provenance, not only model accuracy on historic test data. Disease surveillance covers routine observation over a longer period, while capacity forecasting informs beds, staff and countermeasure supply. Buyers therefore require outcome measures specific to their principal application rather than a single general-purpose AI benchmark.
By End-User: Government and Public Health Agencies
National public-health institutions continue to anchor procurement because outbreak detection, reporting and emergency coordination are statutory functions. Their purchases range from monitoring subscriptions to multi-year implementation agreements and specialist interpretation support. A single national platform may need to connect provincial laboratories, hospitals, border services and international signals without exposing sensitive patient information across unauthorized systems.
Government and Public Health Agencies are expected to generate approximately USD 1.70 billion of market revenue by 2031, with a modeled CAGR of 13.3%. Hospitals may purchase admissions-oriented forecasts, while pharmaceutical businesses need pathogen burden and countermeasure demand intelligence. These buyers share some data but have different validation, purchasing and service-continuity requirements.
Market Drivers
The cost of delayed outbreak detection is increasing the value of actionable lead time
An agency can spend days reconciling several partial reports before a threat becomes operationally visible. AI-supported event screening makes it possible to examine multilingual announcements, abnormal local signals, and case developments simultaneously. WHO’s October 2026 strategy explicitly seeks the capacity to detect and understand emerging health threats within 24 hours by 2030.
That target does not establish a commercial forecast, but it raises the performance standard against which monitoring software will be judged. Vendors able to document lead time without imposing unmanageable false alarms have a clearer route to procurement.
Diversified surveillance data support better-informed forecasts
Wastewater measurements, sequencing outputs, hospital admissions, and conventional case reports carry different information. The CDC’s 2026 wastewater guidance illustrates why a community-level signal can be useful before a corresponding rise in recorded diagnoses. Combining streams can improve situational awareness, particularly when clinical testing habits change.
Demand consequently extends beyond a forecasting algorithm to cleaning, mapping and reconciling datasets. Software suppliers with proven ingestion pipelines and the ability to explain uncertainty can benefit from that shift, while data collection itself remains a separate activity.
Public-health institutions are formalising digital intelligence programmes
WHO upgraded EIOS in 2025, and ECDC announced new epidemic-intelligence tools in 2026. These projects are public initiatives, but they show that digital analytics is moving into institutional workflows rather than remaining confined to experimental teams.
Once agencies adopt repeatable screening and triage practices, they need maintenance, integration, security review and specialist analytical support. Commercial spending depends on the procurement route, although the underlying operational adoption expands the potential customer base for narrowly defined supplementary products and services.
Cross-border threats are creating demand for shared risk views
A pathogen detected in one transport corridor may alter exposure for several neighbouring countries before official surveillance systems harmonise their records. Outbreak intelligence therefore has value when it connects local evidence with travel patterns, environmental conditions and regional response capacity. BlueDot’s geographic disease risk products exemplify a specialist commercial approach to this problem.
Procurement opportunities are strongest where a platform can support joint exercises, standardised alert thresholds and controlled exchange of information between authorised institutions rather than only display a global heat map.
Response planning is extending the commercial use of epidemiological forecasts
Health emergency teams increasingly need operational forecasts for beds, diagnostic capacity, antiviral inventories and vaccination timing. Airfinity’s disease-specific forecasts illustrate how intelligence can inform those decisions alongside longer-term pharmaceutical demand planning.
Such applications offer repeated planning cycles instead of a single emergency alert. They also require calibration against local population characteristics and healthcare utilisation. Vendors that connect forecasts to concrete resource questions may secure recurring engagements even when public agencies prefer to own their underlying surveillance databases.
Market Restraints
Fragmented reporting systems make model performance inconsistent
Health departments use different case definitions, reporting frequencies and laboratory coding practices. A model calibrated to an established urban surveillance network can become unreliable when transferred to a region with irregular reporting or limited testing. Integration costs often arise before the buyer can judge forecast quality.
Suppliers must maintain provenance, missing-data indicators and jurisdiction-specific mappings rather than assume that a larger data volume automatically means better information. These requirements slow deployment and create ongoing support obligations.
False alarms and missed events carry asymmetric public consequences
An early-warning system may identify numerous unusual patterns that prove harmless. Frequent false alerts can absorb epidemiologist time and damage trust; a missed high-consequence threat may carry greater societal cost.
Model evaluation therefore needs more than generic classification accuracy. Agencies consider sensitivity, timeliness, positive predictive value, and whether a signal prompted useful investigation. Sparse historical examples of rare pathogens complicate validation, and performance can deteriorate when disease ecology or public behaviour changes.
Sensitive health and mobility data limit cross-border interoperability
Identifiable care records, geolocation information and genomic data are subject to legal, ethical and contractual safeguards. Public-health exemptions do not remove the need for access controls, retention rules and documented data purposes. These constraints may require local deployment or the exchange of aggregated results instead of raw information.
A multinational forecasting product must accommodate uneven rules and secure hosting requirements, increasing implementation costs and reducing the speed of standardised commercial rollout.
Procurement budgets do not translate directly into software revenue
Governments fund workforce training, laboratories, sequencing networks and public-sector systems as well as software. WHO EIOS and HealthMap demonstrate the substantial contribution of non-commercial resources to epidemic intelligence. A large preparedness appropriation therefore cannot be treated as addressable AI vendor turnover.
Grant cycles and irregular emergency appropriations further complicate contract renewal. Suppliers need a demonstrable incremental benefit and a procurement category that separates their product from infrastructure already maintained by public institutions.
Clinical and epidemiological accountability limits autonomous deployment
GenAI systems can summarise a signal quickly yet still misstate a location, confuse a suspected case with a confirmed case or reproduce unreliable reporting. Such errors are particularly costly when outputs influence travel advice or emergency resource allocation.
Agencies require expert review, auditable model changes and mechanisms for correcting past alerts. The resulting governance workload can offset some labour savings from automated triage and favours tools designed to assist, rather than replace, professional epidemiological assessment.
Regional Outlook
North America: Established Institutional and Specialist Demand
North America accounts for approximately 41.2% of the modeled global market in 2026, representing USD 700 million. Its comparatively mature public-health information architecture supports purchasing by federal agencies, state and provincial health departments and pharmaceutical companies. The US Centers for Disease Control and Prevention has expanded wastewater surveillance and public-health data integration, while Canada’s published KSI country forecast identifies USD 94 million of relevant demand in 2026.
The region is projected to reach approximately USD 1.27 billion by 2031, an implied CAGR of 12.7%. Private suppliers benefit where they supply capabilities not already maintained by public institutions: disease-specific forecasts, epidemiological interpretation, genomic and environmental integration, and verified risk alerts. Verily’s October 2026 CDC wastewater surveillance award illustrates the role of directly contracted surveillance analytics, although the entire award value is not attributable solely to AI forecasting.
Asia Pacific: Expanding Deployment and Data Infrastructure
Asia Pacific starts from an estimated USD 600 million in 2026, or approximately 35.3% of worldwide revenue, and is projected to reach USD 1.35 billion by 2031. At around 17.6% annually, it is the fastest-growing region in the modeled allocation. China’s separately published KSI market estimate of USD 380 million for 2026 establishes a substantial commercial base within the region; Japan, South Korea, India and other markets have different procurement and disease-monitoring needs.
Regional expansion is uneven because national disease-reporting infrastructure and local data permissions are not standardized. Climate-sensitive infections, respiratory surveillance and cross-border mobility support specialized forecasting, while public cloud deployment cannot compensate for missing laboratory or clinical observations. In India and Southeast Asia, implementation partners capable of interpreting local case definitions and maintaining language-specific monitoring may be as important as the AI model itself.
Competitive Landscape
The competitive landscape is led by firms that deliver identifiable pathogen-intelligence products and analytics services. BlueDot and Airfinity offer geographic disease risk and forecasting products; Biobot Analytics converts wastewater monitoring into population-level predictive signals. Verily Health supplies wastewater surveillance and analysis to public-health partners, while Palantir Technologies provides integrated disease-response data environments for government institutions. Their offerings solve different parts of an outbreak-warning workflow and are not interchangeable merely because each uses AI.
Dataminr provides cross-sector early-event discovery, including detection of disease-related events, while Ginkgo Bioworks has developed biosurveillance capabilities through Concentric and associated epidemiological collaborations. Public networks such as WHO EIOS and ECDC episomer create important technical baselines but are not merchant software suppliers. A commercial contract must therefore deliver additional data, interpreted forecasts, integration assurance or continuity commitments beyond publicly available alerting.
Competitive differentiation increasingly rests on rigorous evaluation of signal timeliness, false positives, source provenance and response handoff. Clinical and laboratory data permissions determine the feasible integration architecture. International procurement also rewards local epidemiology expertise and support arrangements, because an accurate global model can still misinterpret region-specific testing changes or disease seasonality.
Recent Developments
19 October 2026: WHO Regional Office for Africa deployed the AI-enabled Preparedness Data Exchange platform in the Democratic Republic of the Congo, connecting national early-warning information with a regional service covering 47 Member States.
14 October 2026: Verily Health announced a CDC contract to continue national infectious-disease wastewater surveillance through Sightline, combining pathogen testing, sequencing and data analytics for public-health decision-making.
12 October 2026: WHO Pandemic and Epidemic Intelligence Hub introduced a strategy aiming to enable detection and understanding of emerging health threats within 24 hours by 2030, strengthening the policy case for integrated surveillance.
6 May 2026: European Centre for Disease Prevention and Control launched episomer, a customizable, open-source tool for monitoring social-media trends as potential early signals of infectious-disease events.
30 April 2026: European Centre for Disease Prevention and Control demonstrated Epi+, its forthcoming open-source event-based surveillance platform, during piloting; no general commercial launch was implied.
13 October 2025: World Health Organization released EIOS 2.0 with additional data sources and AI-supported screening capabilities for international public-health threat assessment.
Market Outlook
Disease-intelligence budgets are moving from emergency-only software purchases toward persistent surveillance, forecast maintenance, and analytical interpretation. Better integration of wastewater, sequencing and syndromic information should widen the range of credible warning indicators. However, the decision to investigate remains institutional: useful products will have to make uncertainty visible and help epidemiologists choose an action without hiding the limitations of the underlying evidence.
Commercial spending will favour specialised disease forecasting, source normalization, integration services and validated operational support. Growth will remain constrained by inconsistent data quality, public procurement cycles and open-source alternatives. Suppliers able to demonstrate reproducible alert performance in more than one jurisdiction and to sustain local expert support after deployment should be better positioned than companies offering undifferentiated analytics platforms.
AI for Predicting Pandemics and Global Health Emergencies Market Scope:
| Report Metric | Details |
|---|---|
| Total Market Size in 2026 | USD 1.70 billion |
| Total Market Size in 2031 | USD 3.35 billion |
| Forecast Unit | Billion |
| Growth Rate | 14.5% |
| Study Period | 2021 to 2031 |
| Historical Data | 2021 to 2024 |
| Base Year | 2025 |
| Forecast Period | 2026 – 2031 |
| Segmentation | Component, Deployment Mode, Application, End-User |
| Companies |
|
| Customization Scope | 15% Free Customization included with purchase — Request Custom Breakdown → |
| Sample & Data Access | PDF Sample, Excel Databook & Analyst Briefing — Download Free Sample → |
Market Segmentation
By Component
Software
Services
Hardware
By Deployment Mode
Cloud-Based
On-Premise
By Application
Outbreak Prediction & Detection
Disease Surveillance
Contact Tracing
Risk Assessment
Health Trend Forecasting
Public Health Resource Allocation
Others
By End-user
Government & Public Health Agencies
Hospitals & Clinics
Research Institutions
Pharmaceutical & Biotechnology Companies
Academic Institutions
Others
By Geography
North America
United States
Canada
Mexico
South America
Brazil
Argentina
Others
Europe
Germany
United Kingdom
France
Italy
Spain
Others
Middle East and Africa
Saudi Arabia
UAE
South Africa
Others
Asia Pacific
China
India
Japan
South Korea
Australia
Indonesia
Thailand
Taiwan
Others
Table of Contents
1. EXECUTIVE SUMMARY
2. MARKET SNAPSHOT
2.1. Market Overview
2.2. Market Definition
2.3. Scope of the Study
2.4. Market Segmentation
3. BUSINESS LANDSCAPE
3.1. Market Drivers
3.1.1. The cost of delayed outbreak detection is increasing the value of actionable lead time
3.1.2. Diversified surveillance data support better-informed forecasts
3.1.3. Public-health institutions are formalising digital intelligence programmes
3.1.4. Cross-border threats are creating demand for shared risk views
3.1.5. Response planning is extending the commercial use of epidemiological forecasts
3.2. Market Restraints
3.2.1. Fragmented reporting systems make model performance inconsistent
3.2.2. False alarms and missed events carry asymmetric public consequences
3.2.3. Sensitive health and mobility data limit cross-border interoperability
3.2.4. Procurement budgets do not translate directly into software revenue
3.2.5. Clinical and epidemiological accountability limits autonomous deployment
3.3. Market Opportunities
3.4. Porter’s Five Forces Analysis
3.5. Industry Value Chain Analysis
3.6. Policies and Regulations
3.7. Strategic Recommendations
4. TECHNOLOGICAL OUTLOOK
4.1. Open-Source Signal Screening
4.2. Multimodal and Genomic Analytics
4.3. Forecast Validation and Model Governance
5. AI FOR PREDICTING PANDEMICS AND GLOBAL HEALTH EMERGENCIES MARKET BY COMPONENT
5.1. Introduction
5.2. Software
5.3. Services
5.4. Hardware
6. AI FOR PREDICTING PANDEMICS AND GLOBAL HEALTH EMERGENCIES MARKET BY DEPLOYMENT MODE
6.1. Introduction
6.2. Cloud-Based
6.3. On-Premise
7. AI FOR PREDICTING PANDEMICS AND GLOBAL HEALTH EMERGENCIES MARKET BY APPLICATION
7.1. Introduction
7.2. Outbreak Prediction & Detection
7.3. Disease Surveillance
7.4. Contact Tracing
7.5. Risk Assessment
7.6. Health Trend Forecasting
7.7. Public Health Resource Allocation
7.8. Others
8. AI FOR PREDICTING PANDEMICS AND GLOBAL HEALTH EMERGENCIES MARKET BY END-USER
8.1. Introduction
8.2. Government & Public Health Agencies
8.3. Hospitals & Clinics
8.4. Research Institutions
8.5. Pharmaceutical & Biotechnology Companies
8.6. Academic Institutions
8.7. Others
9. AI FOR PREDICTING PANDEMICS AND GLOBAL HEALTH EMERGENCIES MARKET BY GEOGRAPHY
9.1. North America
9.1.1. United States
9.1.2. Canada
9.1.3. Mexico
9.2. South America
9.2.1. Brazil
9.2.2. Argentina
9.2.3. Others
9.3. Europe
9.3.1. Germany
9.3.2. United Kingdom
9.3.3. France
9.3.4. Italy
9.3.5. Spain
9.3.6. Others
9.4. Middle East and Africa
9.4.1. Saudi Arabia
9.4.2. UAE
9.4.3. South Africa
9.4.4. Others
9.5. Asia Pacific
9.5.1. China
9.5.2. India
9.5.3. Japan
9.5.4. South Korea
9.5.5. Australia
9.5.6. Indonesia
9.5.7. Thailand
9.5.8. Taiwan
9.5.9. Others
10. COMPETITIVE ENVIRONMENT AND ANALYSIS
10.1. Major Players and Strategy Analysis
10.2. Market Share Analysis
10.3. Mergers, Acquisitions, Agreements and Collaborations
10.4. Competitive Dashboard
11. COMPANY PROFILES
11.1. BlueDot
11.2. Airfinity
11.3. Biobot Analytics
11.4. Verily Health
11.5. Palantir Technologies Inc.
11.6. Dataminr
11.7. Ginkgo Bioworks Holdings, Inc.
12. APPENDIX
12.1. Currency
12.2. Assumptions
12.3. Base and Forecast Years Timeline
12.4. Key Benefits for Stakeholders
12.5. Research Methodology
12.6. Abbreviations





Frequently asked questions
What is the projected market value for AI in pandemic prediction by 2031?
The AI for Predicting Pandemics and Global Health Emergencies Market will reach USD 3.35 billion by 2031, growing at 14.5% CAGR.
Which component type dominates the AI pandemic prediction market?
Software contributes approximately 65% of the market value.
Which buyer segment drives demand for AI in global health emergencies?
Government and public-health agencies account for 54% of demand.
Which region leads the AI for pandemic prediction market revenue?
North America retains the largest starting revenue base.
Which region shows the fastest growth for AI pandemic prediction solutions?
Asia Pacific is expected to record the fastest expansion.
How do specialist companies differentiate their AI pandemic prediction offerings?
They differentiate through disease-specific forecasts and environmental surveillance.
Cite this report
Knowledge Sourcing Intelligence. (Oct 2026). AI for Predicting Pandemics and Global Health Emergencies Market - Strategic Insights and Forecasts (2026-2031). https://www.knowledge-sourcing.com/report/ai-for-predicting-pandemics-and-global-health-emergencies-market