
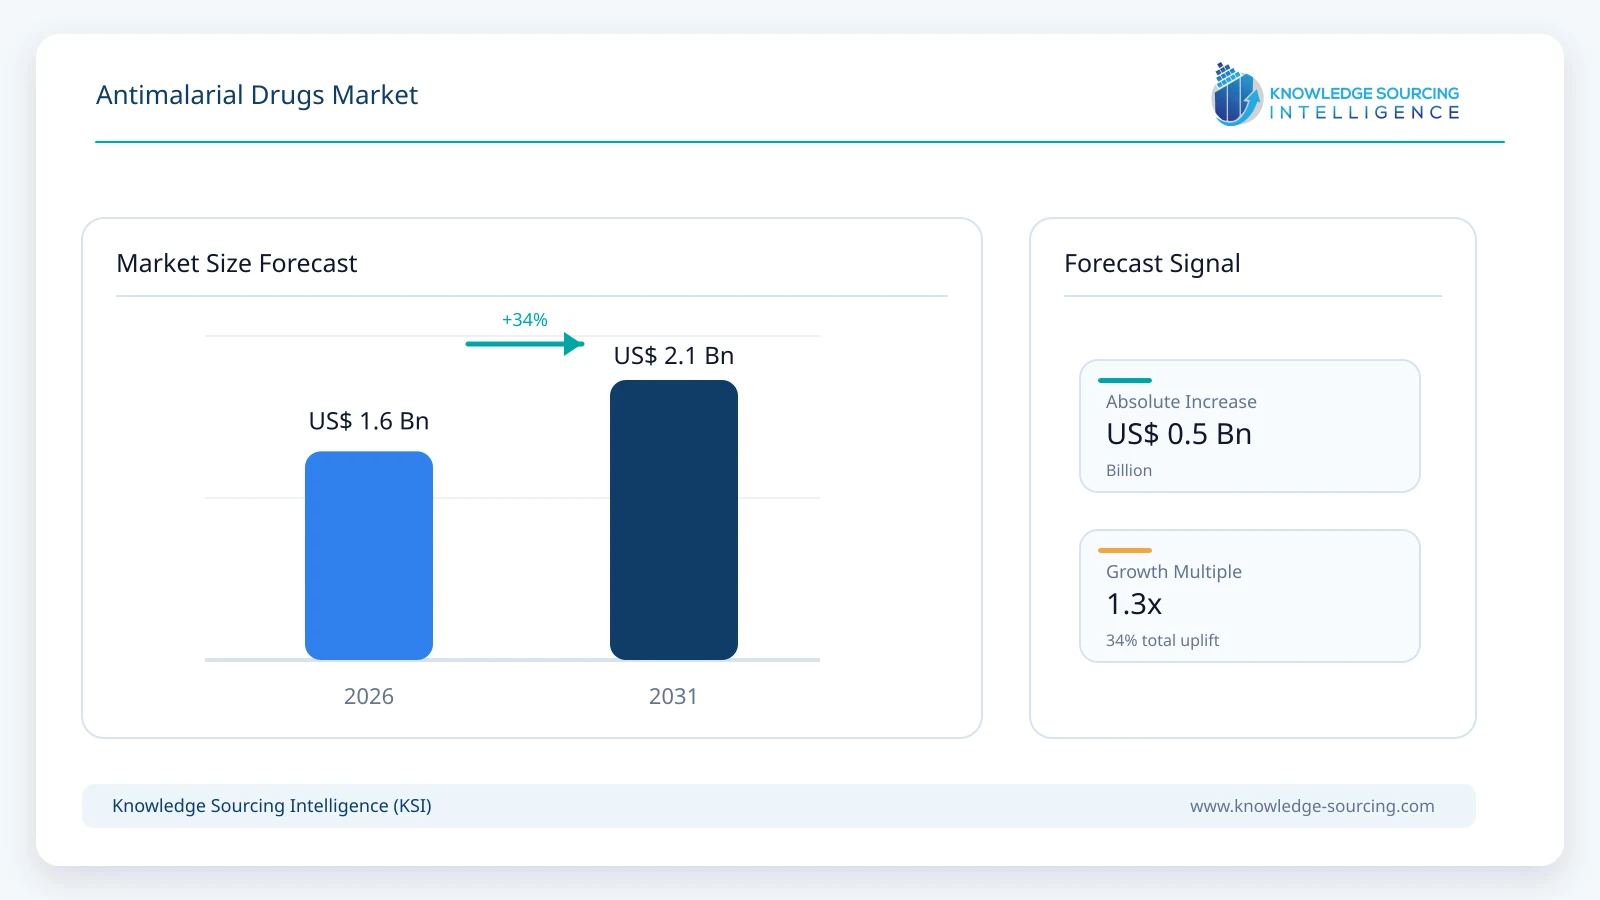
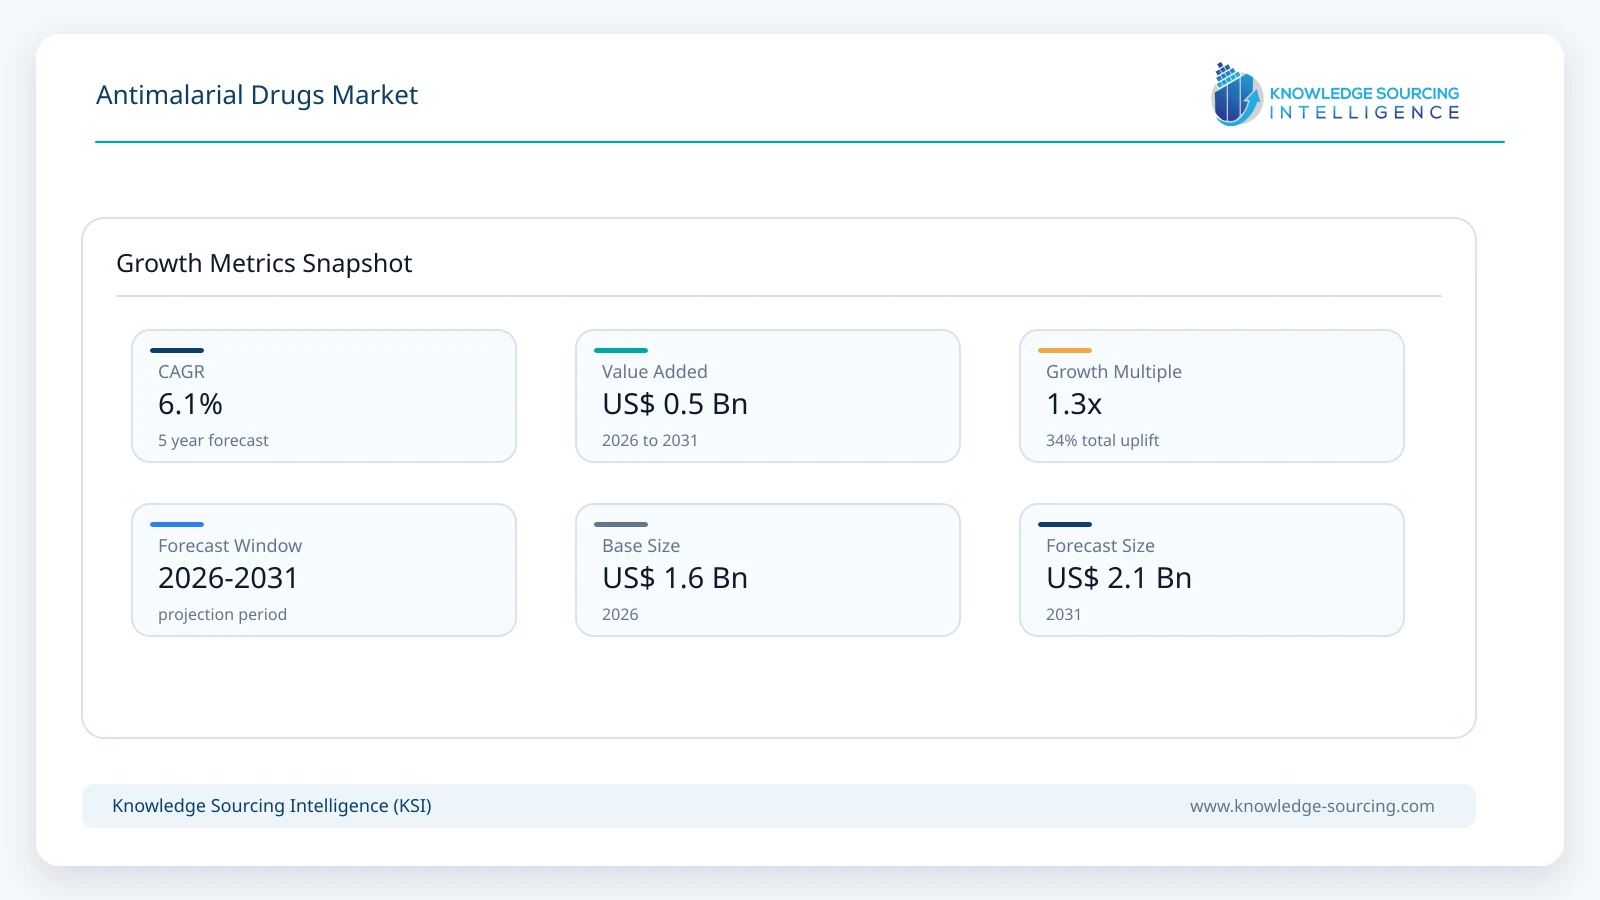
The antimalarial drugs market is estimated at USD 1.55 billion in 2026 and is forecast to reach approximately USD 2.08 billion in 2031, representing a CAGR of 6.1% during the forecast period.
Highlights:
- 1Artemisinin-based combination therapies account for approximately USD 0.84 billion, or 54% of 2026 market value.
- 2Plasmodium falciparum therapies represent approximately USD 1.12 billion, or 72% of global antimalarial medicine spending.
- 3Public and donor-funded procurement contributes roughly USD 0.93 billion, making quality assurance and tender access commercially decisive.
- 4Africa represents approximately USD 0.84 billion of 2026 demand despite substantially lower treatment prices than private travel markets.
- 5Resistance pressure and new radical-cure therapies are shifting value toward differentiated combinations rather than higher mature-ACT pricing.
The market covers medicines used for treatment, radical cure and chemoprevention of human malaria, including artemisinin-based combination therapies (ACTs), quinoline and antifolate therapies, injectable artesunate, 8-aminoquinolines and emerging non-artemisinin combinations. Malaria vaccines, diagnostics, vector-control products and veterinary antiprotozoals are excluded.
Market Overview
Antimalarial medicines operate in an unusual pharmaceutical market in which disease burden is concentrated in low-income settings while much of the purchasing power is organized through governments, multilateral donors and pooled procurement. WHO estimates 282 million malaria cases and 610,000 deaths in 2024, with the African Region carrying the overwhelming majority of the burden. In parallel, Global Fund-supported programs tested 367 million suspected cases and treated 167 million malaria cases in 2025, demonstrating the scale of recurring medicine demand even before privately financed treatment and travel prophylaxis are included.
The commercial model differs sharply from conventional branded pharmaceuticals. Mature first-line therapies are procured at highly compressed prices. UNICEF lists an indicative price of USD 20.10 for a pack containing 30 adult artemether-lumefantrine treatment blisters of 24 tablets, equivalent to roughly USD 0.67 per blister treatment pack before freight, insurance and program costs. The resulting market is volume intensive: supplier economics depend on manufacturing scale, active pharmaceutical ingredient security, WHO prequalification, tender eligibility and reliable delivery rather than high unit margins.
Drug resistance is becoming the most important structural change in product selection. WHO reports confirmed artemisinin partial resistance in Eritrea, Rwanda, Uganda and the United Republic of Tanzania, with suspected resistance in Ethiopia, Sudan, Namibia and Zambia. Artemisinin partial resistance does not automatically mean ACT treatment failure when the partner drug remains effective, but it increases the value of therapeutic-efficacy surveillance, diversified first-line treatment policies and next-generation non-artemisinin combinations.
Innovation is therefore entering a market that has historically been dominated by inexpensive generics. Novartis reported in November 2025 that ganaplacide/lumefantrine met the primary endpoint in Phase III, achieving a 97.4% PCR-corrected cure rate under the estimand method. GSK and Medicines for Malaria Venture have also advanced tafenoquine, a single-dose radical-cure medicine for P. vivax relapse prevention, which received WHO prequalification in 2024. These products do not immediately displace mature ACTs, but they can increase the value contribution from resistance management and relapse prevention through 2031.
Growth is expected to remain moderate in the near term because mature ACTs are highly commoditized and donor procurement prioritizes affordability. Value growth strengthens later in the period as chemoprevention coverage expands, more quality-assured manufacturers enter procurement pools, tafenoquine adoption broadens in P. vivax settings, and next-generation therapies targeting resistance move closer to commercial use.
Antimalarial Drugs Market Trends
Resistance is changing first-line procurement strategy
WHO now treats antimalarial resistance in Africa as a portfolio-management problem rather than an isolated efficacy issue. Its implementation guidance supports multiple first-line therapies as one option to reduce selection pressure on a single ACT. For suppliers, this can fragment national tenders across artemether-lumefantrine, artesunate-amodiaquine, dihydroartemisinin-piperaquine and other locally appropriate regimens, making product breadth and country registration increasingly valuable.
Pooled procurement keeps mature therapy prices structurally compressed
The Global Fund Pooled Procurement Mechanism managed approximately USD 1.02 billion in health-product orders in 2025 across 81 countries, including antimalarial medicines. Procurement pools combine demand, establish quality requirements, and expose suppliers to competitive pricing across large volumes. This lowers acquisition cost for malaria programs but limits pricing power for undifferentiated products, making manufacturing efficiency, working-capital discipline and dependable lead times central to supplier competitiveness.
Chemoprevention creates recurring seasonal demand outside clinical case treatment
Antimalarial demand is not limited to patients with confirmed infection. Global Fund-supported programs provided seasonal malaria chemoprevention to 52.1 million children and preventive treatment to 19.9 million pregnant women in 2025. WHO recommends seasonal malaria chemoprevention for children at high risk in areas with strongly seasonal transmission, with sulfadoxine-pyrimethamine plus amodiaquine widely used. These programs create predictable, campaign-driven procurement cycles with large pediatric volumes.
New therapies are moving the market beyond mature ACT combinations
The innovation pipeline is increasingly focused on resistance, simpler dosing, and relapse prevention. Ganaplacide/lumefantrine combines a novel non-artemisinin mechanism with a once-daily lumefantrine formulation, while tafenoquine offers single-dose radical cure for eligible P. vivax patients when used with blood-stage treatment. Commercial adoption will depend on regulatory approvals, national guideline inclusion, pharmacovigilance, and enabling diagnostics such as G6PD testing, but these products can raise the value mix of a market otherwise dominated by low-priced generics.
Segment Analysis
By Drug Class - Artemisinin-Based Combination Therapies
Artemisinin-based combination therapies are estimated at approximately USD 0.84 billion in 2026, or 54% of market value. ACTs remain the treatment backbone for uncomplicated P. falciparum malaria and for chloroquine-resistant P. vivax malaria because the artemisinin component rapidly reduces parasite biomass while the partner drug clears remaining parasites. Artemether-lumefantrine, artesunate-amodiaquine, dihydroartemisinin-piperaquine and pyronaridine-artesunate are supplied through both public programs and private channels. Commercial value is constrained by competitive procurement pricing, but volumes remain substantial because ACTs sit at the center of national treatment policies in high-burden countries.
By Malaria Type - Plasmodium falciparum
P. falciparum-related therapies are estimated at approximately USD 1.12 billion in 2026, or 72% of the market. The species accounts for nearly all malaria cases in the WHO African Region and is responsible for most severe disease and mortality. Its treatment mix spans oral ACTs for uncomplicated disease and injectable artesunate for severe malaria, while rising artemisinin partial resistance increases the strategic importance of alternate ACT partner drugs and new mechanisms. The segment therefore combines the market's largest treatment volumes with the strongest near-term need for therapeutic innovation.
By Therapeutic Use - Acute Treatment
Acute treatment accounts for approximately USD 1.18 billion in 2026, or 76% of antimalarial medicine spending. This category includes oral first-line treatment for uncomplicated malaria and parenteral treatment for severe disease. Its scale is supported by the continuing global case burden and by test-and-treat programs that channel large patient volumes through public facilities and community health systems. Chemoprevention and radical cure are strategically important growth areas, but acute treatment remains the largest value pool because every confirmed symptomatic infection requires rapid parasite clearance.
By Route of Administration - Oral
Oral therapies are estimated at approximately USD 1.36 billion in 2026, or 88% of the market. Fixed-dose oral combinations dominate uncomplicated malaria because they can be dispensed at community and primary-care level, packaged by weight band and procured efficiently in large volumes. Pediatric dispersible formulations are particularly important in high-burden African markets. Parenteral artesunate commands a smaller share of total value but remains essential for severe malaria and continues to attract new WHO-prequalified strengths and suppliers.
By Procurement and Distribution - Public and Donor-Funded Procurement
Public and donor-funded procurement represents approximately USD 0.93 billion in 2026, or 60% of market value. National malaria programs, the Global Fund, UNICEF and other institutional buyers concentrate large volumes into tenders that typically require WHO prequalification or equivalent quality assurance. This structure makes regulatory status a direct commercial gate: a manufacturer may have technical production capacity yet remain excluded from major funded programs until its finished product is accepted by the relevant procurement system. Private pharmacies and travel-medicine channels remain important, but they do not match the institutional market in volume.
By Geography - Africa
Africa is estimated at approximately USD 0.84 billion in 2026, or 54% of global antimalarial drug value. The share is far below the region's proportion of global malaria cases because public procurement and generic competition compress treatment prices. Even so, Africa remains the commercial center of volume demand: resistance surveillance is influencing first-line therapy choices, chemoprevention programs generate recurring pediatric procurement, and local manufacturing is gaining relevance. In August 2026, Uganda-based Quality Chemical Industries received WHO prequalification for artemether-lumefantrine 20/120 mg tablets, expanding the pool of quality-assured African supply.
Market Drivers
Persistent malaria burden sustains high recurring treatment volumes across endemic countries.
Expansion of seasonal malaria chemoprevention increases predictable pediatric procurement cycles.
Artemisinin partial resistance increases demand for diversified ACT portfolios and novel mechanisms.
WHO prequalification and pooled procurement continue expanding access to quality-assured manufacturers.
New radical-cure and next-generation therapies can increase value per treated patient in selected populations.
Market Restraints
Aggressive pooled-procurement pricing limits margins for mature generic ACT manufacturers.
Drug resistance can shorten product lifecycles and force national treatment-policy changes.
Donor funding volatility can delay tenders, reduce order visibility and disrupt supplier planning.
Tafenoquine and primaquine use is constrained by G6PD-related haemolysis risk and testing requirements.
Substandard and falsified medicines remain a threat to treatment outcomes and quality-assured suppliers.
Competitive Environment
Competition is divided between innovators with differentiated products and high-volume manufacturers competing for quality-assured public procurement. Novartis remains central through Coartem and its ganaplacide/lumefantrine pipeline, while GSK participates through tafenoquine for P. vivax radical cure. Sanofi retains WHO-prequalified artesunate-amodiaquine products. A large manufacturing group led by Cipla, Ipca Laboratories, Guilin Pharmaceutical, Macleods, Ajanta Pharma, Strides, Micro Labs and Viatris supplies mature ACTs, severe-malaria products and preventive combinations into institutional markets.
WHO prequalification is one of the most important competitive filters. Recent additions show that supplier access continues to broaden: Velvet Med-Healthcare Solutions received prequalification for artemether-lumefantrine products in 2025, Ajanta Pharma received prequalification for sulfadoxine-pyrimethamine plus amodiaquine dispersible co-packs in September 2025, and Quality Chemical Industries received prequalification for artemether-lumefantrine in August 2026. The result is greater procurement resilience but also continued price pressure on established generic combinations.
Recent Developments
August 2026: Quality Chemical Industries received WHO prequalification for artemether-lumefantrine 20 mg/120 mg tablets manufactured in Uganda.
November 2025: Novartis reported that Phase III ganaplacide/lumefantrine met its primary endpoint, with a 97.4% PCR-corrected cure rate under the estimand analysis.
September 2025: Ajanta Pharma received WHO prequalification for two dispersible sulfadoxine-pyrimethamine plus amodiaquine co-pack presentations used in malaria chemoprevention.
August 2025: Guilin Pharmaceutical received WHO prequalification for a 30 mg injectable artesunate presentation, adding flexibility for severe-malaria treatment.
Market Outlook
The antimalarial drugs market is expected to remain a high-volume, access-driven pharmaceutical market through 2031. Mature ACTs will continue to dominate treatment volumes, but value creation is gradually shifting toward resistance management, chemoprevention, severe-malaria formulations and differentiated radical-cure or non-artemisinin therapies. Suppliers with WHO-prequalified portfolios, multiple weight-band formulations, dependable API sourcing, and the ability to serve pooled procurement are positioned to retain volume, while innovators can expand value if new products are incorporated into national treatment guidelines without undermining affordability.
Antimalarial Drugs Market Scope:
| Report Metric | Details |
|---|---|
| Total Market Size in 2026 | USD 1.55 billion |
| Total Market Size in 2031 | USD 2.08 billion |
| Forecast Unit | Billion |
| Growth Rate | 6.1% |
| Study Period | 2021 to 2031 |
| Historical Data | 2021 to 2024 |
| Base Year | 2025 |
| Forecast Period | 2026 – 2031 |
| Segmentation | Drug Class, Malaria Type, Therapeutic Use, Route of Administration |
| Companies |
|
Market Segmentation
By Drug Class
Artemisinin-Based Combination Therapies
Quinoline and Related Compounds
Antifolate Combinations
8-Aminoquinolines and Radical-Cure Therapies
Emerging Non-Artemisinin Therapies
Others
By Malaria Type
Plasmodium falciparum
Plasmodium vivax
Plasmodium malariae
Plasmodium ovale
Plasmodium knowlesi and Others
By Therapeutic Use
Acute Treatment
Chemoprevention
Radical Cure / Relapse Prevention
Travel Prophylaxis
By Route of Administration
Oral
Parenteral
Rectal / Other
By Procurement and Distribution
Public and Donor-Funded Procurement
Hospital and Clinic Pharmacies
Retail and Private Pharmacies
Travel-Medicine and Other Channels
By Geography
Africa
Nigeria
Democratic Republic of the Congo
Uganda
Mozambique
Tanzania
Other Africa
Asia Pacific
India
Indonesia
Papua New Guinea
Thailand
Other Asia Pacific
Latin America
Brazil
Colombia
Venezuela
Other Latin America
North America
Europe and Other Markets
Table of Contents
1. INTRODUCTION
1.1. Market Overview
1.2. Market Definition and Scope
1.3. Currency and Assumptions
2. RESEARCH METHODOLOGY
2.1. Secondary Research
2.2. Company and Product Validation
2.3. Market Estimation
3. EXECUTIVE SUMMARY
3.1. Key Findings
3.2. Global Market Size, 2026-2031
4. MARKET DYNAMICS
4.1. Market Drivers
4.2. Market Restraints
4.3. Antimalarial Drug Resistance
4.4. Procurement and Quality-Assurance Environment
5. ANTIMALARIAL DRUGS MARKET BY DRUG CLASS
5.1. Artemisinin-Based Combination Therapies
5.2. Quinoline and Related Compounds
5.3. Antifolate Combinations
5.4. 8-Aminoquinolines and Radical-Cure Therapies
5.5. Emerging Non-Artemisinin Therapies
5.6. Others
6. ANTIMALARIAL DRUGS MARKET BY MALARIA TYPE
6.1. Plasmodium falciparum
6.2. Plasmodium vivax
6.3. Plasmodium malariae
6.4. Plasmodium ovale
6.5. Plasmodium knowlesi and Others
7. ANTIMALARIAL DRUGS MARKET BY THERAPEUTIC USE
7.1. Acute Treatment
7.2. Chemoprevention
7.3. Radical Cure / Relapse Prevention
7.4. Travel Prophylaxis
8. ANTIMALARIAL DRUGS MARKET BY ROUTE OF ADMINISTRATION
8.1. Oral
8.2. Parenteral
8.3. Rectal / Other
9. ANTIMALARIAL DRUGS MARKET BY PROCUREMENT AND DISTRIBUTION
9.1. Public and Donor-Funded Procurement
9.2. Hospital and Clinic Pharmacies
9.3. Retail and Private Pharmacies
9.4. Travel-Medicine and Other Channels
10. ANTIMALARIAL DRUGS MARKET BY GEOGRAPHY
10.1. Africa
10.1.1. Nigeria
10.1.2. Democratic Republic of the Congo
10.1.3. Uganda
10.1.4. Mozambique
10.1.5. Tanzania
10.1.6. Other Africa
10.2. Asia Pacific
10.2.1. India
10.2.2. Indonesia
10.2.3. Papua New Guinea
10.2.4. Thailand
10.2.5. Other Asia Pacific
10.3. Latin America
10.3.1. Brazil
10.3.2. Colombia
10.3.3. Venezuela
10.3.4. Other Latin America
10.4. North America
10.5. Europe and Other Markets
11. COMPETITIVE ENVIRONMENT AND ANALYSIS
11.1. Quality-Assured Procurement Competition
11.2. Innovation and Pipeline Positioning
11.3. Manufacturing and Supply-Security Dynamics
12. COMPANY PROFILES
12.1. Novartis Pharma AG
12.2. GSK plc
12.3. Sanofi
12.4. Cipla Limited
12.5. Ipca Laboratories Limited
12.6. Fosun Pharma
12.7. Macleods Pharmaceuticals Ltd.
12.8. Ajanta Pharma Limited
12.9. Strides Pharma Science Limited
12.10. Shin Poong Pharmaceutical Co., Ltd.
12.11. Micro Labs Limited
12.12. Viatris Inc.
12.13. Quality Chemical Industries Limited
12.14. Universal Corporation Limited
12.15. Velvet Med-Healthcare Solutions S.A.
13. APPENDIX
13.1. Market Definition and Exclusions
13.2. Assumptions
13.3. Abbreviations
Navigate
Trusted by the world's leading organizations











