
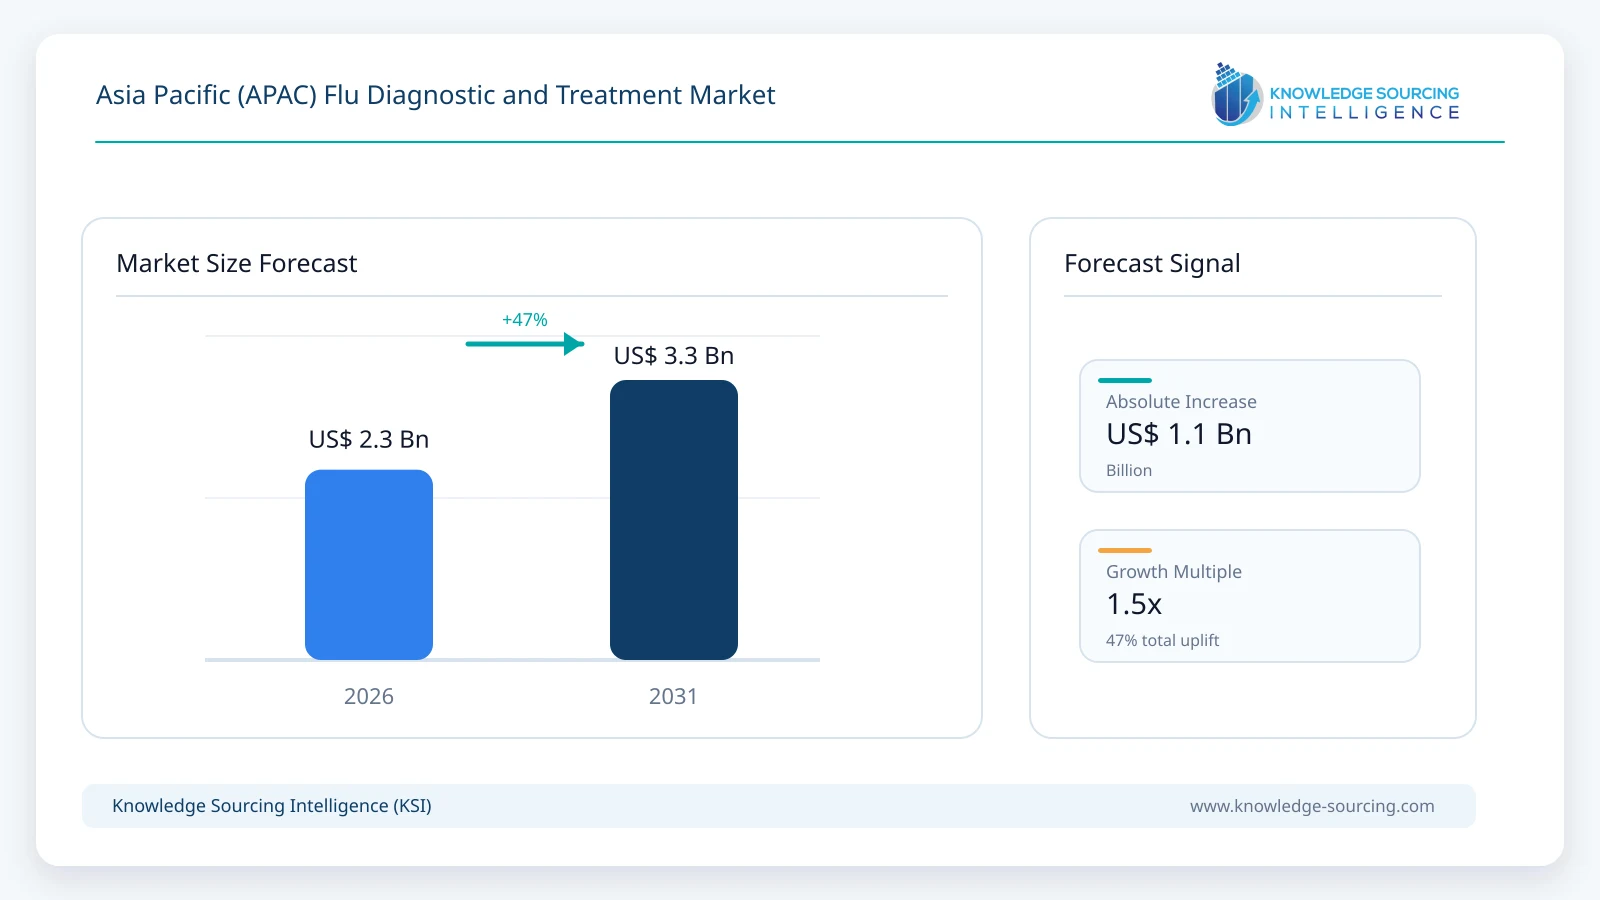
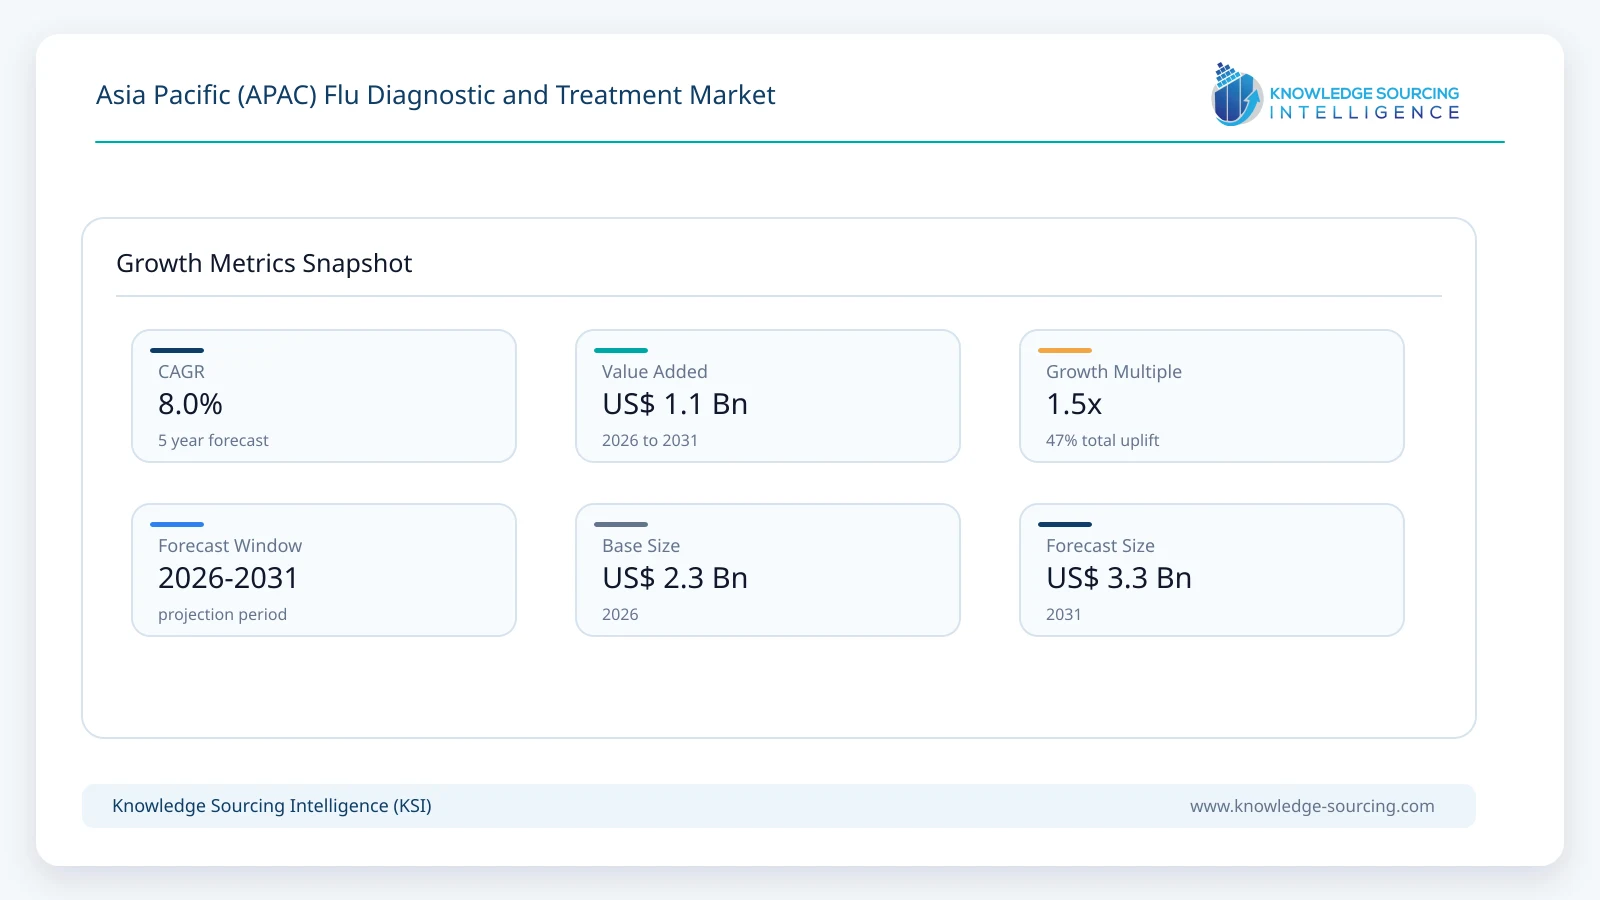
The Asia Pacific (APAC) Flu Diagnostic and Treatment Market is expected to expand at a CAGR of 8.03%, reaching USD 3.31 billion in 2031 from USD 2.25 billion in 2026.
Highlights:
- 1Influenza A represents approximately 76% of the 2026 value, reflecting its circulation and treatment burden.
- 2Rapid molecular testing benefits from broader access to differentiated influenza and respiratory-virus results.
- 3Antiviral prescribing remains highly seasonal, with branded treatment concentrated in selected reimbursed markets.
- 4China leads regional expenditure, while India offers a stronger expansion trajectory from a smaller base.
- 5Multiplex assays require influenza-specific revenue allocation rather than assigning the full panel to influenza.
- 6Supplier competition increasingly combines assay reliability, instrument placement, pricing and medicine access.
Asia Pacific influenza diagnostics and treatment encompass the value of tests directed at influenza A or B and influenza-specific antiviral drugs used to treat or prevent infection. Rapid antigen tests, molecular point-of-care assays, central-laboratory PCR reagents and relevant prescription antivirals constitute the principal commercial categories. Multiplex respiratory panels are included only to the extent of their influenza-attributable value. General cough-and-cold products, routine vaccination, consultation fees and unrelated respiratory pathogens are outside this market.
Clinical value depends on the interval between symptom onset, test result, and treatment decision. Roche's cobas liat, Abbott's influenza assays, BD Veritor and Seegene's Allplex portfolio demonstrate different diagnostic economics, from rapid antigen screening to multiplex PCR. On the treatment side, Shionogi's baloxavir franchise and Roche's commercialization of Xofluza coexist with widely available generic oseltamivir. Healthcare reimbursement, seasonal disease activity, and access to primary care determine how those technologies translate into revenue.
Market Overview
Influenza A(H3N2) circulation and intermittent influenza B activity across Asia Pacific leave healthcare providers balancing fast clinical action against the uncertainty of symptom-based diagnosis. The World Health Organization reported 14% influenza test positivity in the Western Pacific in epidemiological week 5 of 2026, with A(H3N2) predominating and increases in influenza B in some countries. Local surveillance and testing intensity differ widely, so fluctuations in detected cases do not translate mechanically into changes in the region's test market. The most commercially consequential demand comes from hospitals, emergency departments, outpatient clinics and laboratories managing patients whose result can change antiviral prescribing or isolation decisions.
Molecular diagnostics are moving beyond central laboratories, as platforms offering influenza A/B differentiation in approximately 15–30 minutes give physicians a more reliable alternative to antigen-only screening. The revenue opportunity is not uniform: China places considerable pressure on in-vitro diagnostic prices, Japan already has established influenza treatment pathways, and much of South and Southeast Asia is still extending molecular access beyond tertiary hospitals. Abbott's Bioline influenza antigen portfolio, BD's Veritor analyzer, and Roche's cobas liat address different parts of the pathway. Seegene's respiratory panels add central-laboratory throughput, but their total sales cannot be treated as influenza-only demand when several pathogens are detected in one assay.
Influenza therapeutics remain the larger purchasing category because branded cap-dependent endonuclease inhibitors sit alongside generic neuraminidase inhibitors across the region. Roche disclosed CHF 407 million of worldwide Xofluza sales in 2025, with most reported outside the United States; strong Chinese demand helped that result. Its 2026 reporting also showed the seasonal base effect as Chinese demand normalized after a severe influenza period. Shionogi's November 2025 launch of a new Xofluza granule formulation in Japan illustrates efforts to improve dosing options, while supplier revenue still depends on patient eligibility, timing of treatment and national reimbursement decisions. Greater diagnostic availability may improve treatment targeting without guaranteeing a corresponding increase in antiviral courses.
Market Trends
Multiplex PCR Is Shifting Diagnostic Workflows
Roche's cobas liat influenza A/B and RSV assay and Seegene's Allplex respiratory panels place influenza within a broader differential-diagnosis workflow. In a patient presenting with fever and cough, the practical choice is often between confirming influenza and excluding pathogens such as RSV or SARS-CoV-2, rather than ordering sequential single-analyte tests. Multiplex platforms therefore compete on speed, reliability, instrument availability and the usefulness of simultaneous results.
The commercial gain is concentrated in higher-value assay consumables and recurring reagent use, not in the entire list price of every respiratory panel. Laboratories with established molecular infrastructure can expand influenza testing at relatively low additional capital cost; small clinics may still prefer antigen tests because of reagent expense, staffing and throughput. Point-of-care molecular demand consequently expands unevenly across countries and healthcare settings.
Antiviral Demand Is Becoming More Product-Specific
Baloxavir and generic oseltamivir serve the same clinical disease but differ in formulation, course duration and purchasing economics. Shionogi introduced Xofluza granules 2% in Japan on 12 November 2025, adding a treatment and prophylaxis presentation to its established antiviral range. Roche's published 2025 results also showed the significance of Chinese Xofluza sales to the wider influenza franchise.
A strong winter can elevate sales without creating a durable change in underlying treatment penetration. Roche's July and October 2026 releases attributed weaker Chinese Xofluza comparisons partly to milder influenza activity after the preceding season. Forecasting must therefore separate market access, pharmacy stocking and product adoption from transitory epidemic peaks. Generic competition can continue to constrain the realized value of treated courses even as diagnosis improves.
Point-of-Care Screening Remains Economically Important
Rapid influenza antigen tests have a place where facilities need a low-cost result and cannot readily maintain molecular instrumentation. Abbott's Bioline influenza A/B assay and BD's Veritor products illustrate that disposable kits remain a direct competing format rather than a legacy technology that will disappear. Low complexity, immediate availability and established procurement arrangements help sustain these purchases across outpatient practices and smaller hospitals.
The limitation is sensitivity, particularly when viral load is low or samples are collected outside the optimum window. Negative antigen tests may need molecular confirmation in clinically important cases. Hospitals consequently maintain mixed test portfolios: antigen assays for accessible triage and molecular testing when clinical risk or treatment decisions justify higher cost. Vendor opportunities depend on that workflow design as much as aggregate influenza case counts.
Surveillance Networks Are Influencing Assay Readiness
WHO's September 2026 review of South-East Asian influenza surveillance describes progress in virological sampling, laboratory strengthening and external quality assurance. Those activities shape the market indirectly by improving specimen handling and awareness of circulating strains, rather than by turning every public-health sample into a commercial diagnostic sale. Surveillance also informs laboratory menus ahead of expected influenza seasons.
The relationship between public surveillance and private purchases is strongest when laboratories have trained staff, controlled reagent logistics and instruments that can handle both routine clinical tests and outbreak-period demand. Fragmented access elsewhere limits this translation. Producers of reliable assays and integrated sample-to-answer systems are better positioned than companies offering only a single reagent without servicing capability.
Country Pricing and Reimbursement Are Diverging
Influenza medicine sales in China and Japan demonstrate different revenue mechanics. Japanese clinicians have an established antiviral-prescribing pathway, with Shionogi identifying early diagnosis and treatment as central to the market. China's much larger population can generate more potential courses, but procurement and reimbursement policies exert considerable pressure on pricing in diagnostics and medicines.
The resulting supplier mix cannot be inferred from nominal patient counts alone. Manufacturers need local registrations, distribution networks and products suitable for hospital versus retail pharmacy use. Premium molecular assays may expand fastest in selected urban hospital systems while generic antivirals remain the mainstay of treatment in lower-spending settings. Market shares are likely to shift by technology and geography rather than follow one common regional growth rate.
Segment Analysis
By Type of Flu: Influenza A
Influenza A accounts for approximately USD 1.71 billion of regional diagnostic and antiviral expenditure in 2026. This position reflects repeated A(H3N2) and A(H1N1) circulation, large treatment volumes, and the broad inclusion of influenza A targets in commercial assays. The underlying value belongs to the testing and treatment supplied for influenza A, not to disease surveillance budgets or vaccination.
Seasonal shifts in influenza B activity can change the relative value of type A, but influenza A remains the leading revenue category through 2031. Multiplex panels usually test both types together, and their costs are not multiplied by the number of viruses identified. Treatment demand likewise depends on the clinical pathway for the confirmed infection rather than on surveillance totals alone.
By Offering: Rapid Molecular Assay
Rapid molecular influenza assays are projected to reach approximately USD 610 million in 2031, compared with a materially smaller 2026 base. These tests increasingly fit emergency and outpatient decisions where a result returned during the consultation can guide influenza-specific treatment. Roche's cobas liat and Cepheid's Xpert platforms illustrate distinct instrument installed bases that can support recurring assay purchases.
Growth is strongest where buyers can absorb cartridge cost and provide quality assurance, instrument maintenance and staff training. Antigen screening will retain considerable volume, but a higher share of patient encounters may be resolved with molecular testing when influenza, SARS-CoV-2 and RSV circulate concurrently. The greatest supplier gains will accrue to products that combine accuracy with short turnaround times and serviceable instruments.
By Age Group: People Aged 65 Years and Above
Older adults generate a disproportionate need for careful influenza diagnosis because complications and hospitalization risks rise with age and comorbidities. Japan and South Korea are especially relevant markets given their older populations, although age by itself does not determine whether antiviral treatment is clinically indicated. Hospital pathways emphasize timely testing, clinical assessment and prescribing under established guidance.
Expenditure attributable to patients aged 65 and above is modeled at roughly USD 700 million in 2031. Higher healthcare contact rates and use of molecular assays contribute to growth, while the affordability of outpatient care and differing antiviral practice moderate the revenue effect. Hospital-based testing and access to medicine remain the most influential determinants of expenditure for this group.
By End-User: Hospital Laboratory
Hospital laboratories remain the largest end-user category because emergency departments, admitted patients and high-risk outpatient services require dependable testing supported by laboratory protocols. The segment is estimated to represent about 45.8% of 2026 value. Roche, Seegene and Cepheid compete through different combinations of central-laboratory throughput, rapid molecular instruments and multiplex respiratory capability.
Purchasing is shaped by turnaround time, staffing, accreditation and the number of assays supported on a common platform. The category is expected to grow in absolute terms, although outpatient clinics capture a rising fraction of decentralized diagnostic use. Medicines supplied through hospital-associated care are allocated to the treatment setting to avoid double counting outpatient and laboratory demand.
Market Drivers
Clinical Need for Rapid Etiological Differentiation
Influenza A and B, RSV and SARS-CoV-2 can present with overlapping respiratory symptoms, making test availability valuable when the result changes prescribing or infection-control decisions. Rapid molecular platforms give clinicians a route to more sensitive influenza detection within the treatment decision window. CDC's 2026 review identified several influenza molecular assays returning results within approximately 15–30 minutes, supporting the underlying technical proposition.
The growth mechanism is a change in the mix of tests rather than a universal requirement to test every respiratory illness. Hospital laboratories and selected urgent-care settings are more likely to pay for rapid multiplex results. Adoption depends on clinical protocols and the ability to use results during the patient encounter.
Expansion of Formal Diagnostic Capacity
Public and private laboratories in several South and Southeast Asian markets continue to invest in molecular instruments, quality controls and personnel capable of handling respiratory samples. WHO's 2025 South-East Asia surveillance review documents improvements in virological surveillance and laboratory quality processes, which contribute useful infrastructure and technical skills without representing commercial sales themselves.
Reagent purchasing becomes more stable when the same instrument supports multiple assays beyond influenza. Installed instruments can therefore increase the attractiveness of incremental flu testing; conversely, facilities without servicing and reliable cold-chain logistics remain constrained. The resulting opportunity is concentrated in recurring tests and validated workflows.
Greater Antiviral Access and Formulation Choice
Oseltamivir generics provide an established antiviral option, while baloxavir offers a different administration and pharmacological profile. Shionogi's 2025 Japanese launch of Xofluza granules broadened its dosage presentations, addressing patient usability and prescribing options. Roche's 2025 results showed that influenza medicine demand can generate substantial sales in Asia-focused international markets.
Medicine growth will depend on physician prescribing, reimbursement and access to a timely diagnosis. New formulations can expand use within eligible populations, but they do not overcome seasonal demand volatility or justify counting medicines without an influenza-specific indication.
Rising Need to Protect Older and Higher-Risk Patients
Older adults and patients with relevant chronic disease are more likely to receive higher-intensity diagnostic evaluation when influenza is suspected. Hospitals serving these patients value accurate differentiation to reduce inappropriate treatment and support patient management. Japan's established influenza-testing culture demonstrates why demographic risk and care pathways reinforce each other.
The spending effect comes primarily from the frequency and type of clinically justified testing and treatment, not from applying a uniform prevalence rate to the older population. Country differences in access, public coverage and treatment recommendations remain important constraints on the forecast.
Integrated Laboratory Menus and Recurring Consumable Economics
Diagnostic systems that already process respiratory samples can add influenza assays without duplicating all instrument capital. Seegene's multiplex RT-PCR platform, Roche's cobas liat and Cepheid's GeneXpert family are examples of established testing architectures supporting influenza analysis. Laboratories gain purchasing flexibility by sourcing assays within broader instrument ecosystems.
For suppliers, recurring cartridges and reagents provide more visible revenue than isolated instrument installations. However, contracts, servicing and tender pricing determine whether additional testing translates into higher supplier value. The installed-base advantage is material where seasonal peak demand requires rapid capacity adjustment.
Market Restraints
Seasonality and Forecast Instability
A severe influenza season can cause antiviral purchases and laboratory test volumes to rise sharply, followed by a comparatively weak subsequent season. Roche's 2026 reporting attributed lower Xofluza sales in China partly to comparisons with unusually high prior-year influenza activity. This introduces variability into manufacturer revenue that is not explained by annual population changes.
Hospitals and wholesalers must manage expiry risk and inventory while suppliers plan production ahead of uncertain peaks. A multiyear forecast therefore cannot simply extend the strongest reported winter into every subsequent year.
Affordability Gap Between Antigen and Molecular Testing
Molecular cartridges generally require more expensive consumables and instrument support than antigen strips. Outside higher-acuity facilities, the benefit of greater analytical sensitivity may not justify the cost for every uncomplicated respiratory presentation. Lower-cost products consequently remain attractive in community clinics and price-sensitive hospital procurement.
This division slows a uniform transition to molecular testing. Adoption requires a clinically relevant decision pathway, workable reimbursement and trained operators rather than merely purchasing an analyzer.
Procurement Pricing and Reimbursement Pressure
Large diagnostic tenders, reimbursement schedules and public-sector purchasing policies can compress per-test revenue even when test counts rise. Roche noted continuing healthcare pricing reforms in China in its 2026 diagnostics reporting, illustrating the distinction between installed technology and realized sales value.
For antivirals, coverage rules and generic substitution influence whether higher-priced products capture additional market share. A larger treated population need not generate proportionate revenue if average selling prices decline.
Antiviral Timing and Clinical Eligibility
Influenza-specific antivirals offer the greatest benefit when indicated therapy is initiated promptly, but patients may present after the treatment window or without a confirmed influenza infection. Clinicians must weigh symptoms, risk profile, local guidance and the available test result. This limits the commercial translation of every influenza-like illness into a prescription course.
Supply expansion alone therefore cannot support forecasts that presume all infections will be treated. Faster diagnosis is valuable principally where it affects eligible patient management.
Quality Assurance and Supply-Chain Requirements
Respiratory diagnostic assays depend on specimen quality, suitable transport media, instrument maintenance, validated processes and timely reagent replenishment. Laboratories in remote settings may face variable electricity reliability, trained staff shortages or longer delivery lead times. These issues are especially relevant for molecular products that rely on proprietary instruments.
A failed assay or delayed result can prompt repeat testing, but should not be interpreted as sustainable net demand. Manufacturers with servicing networks and resilient distribution can compete more effectively than providers relying solely on reagent availability.
Geographical Outlook
China
China represents approximately 30.2% of Asia Pacific influenza diagnostics and treatment value in 2026, supported by a large patient population, extensive hospital testing and significant demand for branded antivirals. Roche reported strong Xofluza sales in China during 2025, highlighting the commercial importance of influenza-specific prescription therapy when infection activity is high. The country's laboratory infrastructure allows multiple diagnostic formats, from antigen assays to high-throughput PCR.
By 2031, modeled expenditure is approximately USD 970 million. High infection-season variability and procurement pressure constrain growth relative to countries expanding access from a smaller base. Roche's 2026 reporting described a normalization of Xofluza comparisons after the preceding severe season, while diagnostics sales remained subject to local pricing reform. Competitive advantage depends on local product registration, hospital access and cost per actionable result.
India
India is the fastest-growing country in the regional model, with influenza-attributable diagnostics and antiviral revenue expanding at approximately 13.2% annually through 2031. Urban hospital investment, widening molecular-test availability and increased organized outpatient access support growth from a comparatively small commercial base. Public-sector surveillance and case reporting support disease monitoring, but only independently purchased tests and influenza medicines are counted as market revenue.
The modeled market reaches approximately USD 520 million by 2031. Price sensitivity continues to favor rapid antigen testing and affordable generic treatment, while molecular assays gain share where emergency-care pathways and clinical risk justify higher-cost tests. National and state-level differences in reimbursement, laboratory capacity and distribution are likely to remain more important to supplier selection than overall population growth.
Competitive Landscape
The diagnostic market includes multinationals with installed molecular platforms, companies supplying low-cost antigen assays and Asia-based producers offering multiplex PCR reagents. Roche Diagnostics, Cepheid within Danaher and Abbott compete on turnaround time and laboratory workflow, while BD and QuidelOrtho address rapid screening requirements. Seegene and SD Biosensor offer relevant Asian manufacturing and diagnostic portfolios. Specifications and national regulatory status vary, so an internationally available test cannot be assumed to have identical access across every Asia Pacific country.
Influenza therapeutics have a different structure. Shionogi develops and manufactures baloxavir products, Roche commercializes Xofluza in multiple territories, and companies making oseltamivir or other approved influenza antivirals compete in markets where generics dominate volumes. Product selection depends on clinical recommendations, resistance patterns, availability and reimbursement. A supplier of vaccines or nonspecific symptom-relief drugs is not automatically a competitor in this defined treatment market.
The competitive boundary matters particularly for multiplex panels and pharmaceutical distribution. Only the influenza-attributable share of a SARS-CoV-2/flu/RSV test is assigned to the market; the same test cartridge is not valued several times. Similarly, brand-owner sales and distributor resale are not added together. Established hospital relationships and technical support can be decisive for assays, whereas physician familiarity and pharmacy access matter more for antiviral products.
Recent Developments
22 October 2026: Roche reported nine-month 2026 results showing Asia-Pacific diagnostics pressure from Chinese pricing reforms and weaker Chinese Xofluza comparisons after a milder preceding influenza season. The update highlights the importance of seasonality and realized pricing for both sides of the market.
21 October 2026: Danaher released third-quarter results showing a lower respiratory-testing revenue run rate for Cepheid in 2026 than in 2025. The disclosure relates to global respiratory testing, not influenza-only Asia Pacific sales, but provides a direct supplier indicator of platform-utilization volatility.
23 July 2026: Roche stated in its first-half 2026 results that lower Xofluza sales in China reflected the high comparison base created by the previous severe flu season. This illustrates why epidemic peaks should not be carried forward as permanent demand.
12 May 2026: Shionogi presented FY2025 results describing early influenza diagnosis and treatment in Japan and its Xofluza and Rapiacta franchise. The report confirms the continuing role of influenza-specific antivirals in the Japanese treatment pathway.
29 January 2026: Roche published 2025 results showing CHF 407 million of worldwide Xofluza sales and particularly strong demand in China. The company’s figures provide a manufacturer revenue cross-check, although they are not an Asia-Pacific market total.
12 November 2025: Shionogi launched Xofluza granules 2% in Japan for influenza treatment and prophylaxis, widening formulation options within its antiviral portfolio.
Market Outlook
Influenza test purchasing in Asia Pacific is likely to shift gradually toward a higher molecular share, but antigen products will remain commercially important in community and budget-sensitive settings. Laboratories able to use existing platforms for several pathogens will benefit from recurring assay demand, while companies must demonstrate reliable sample-to-answer performance and support. Improved surveillance can inform laboratory readiness without necessarily increasing commercial sales every year.
Antiviral growth will be influenced by the balance between low-cost generic medicines and higher-value branded therapies. China is expected to remain the largest market but face procurement and seasonal volatility, while India gains share as formal care and laboratory access develop. Clinical eligibility, prompt diagnosis and reimbursement will continue to govern the addressable treatment pool. Forecasts predicated solely on headline case counts or a repeat of the strongest flu season risk overstating actual supplier revenue.
Asia Pacific (APAC) Flu Diagnostic and Treatment Market Scope:
| Report Metric | Details |
|---|---|
| Total Market Size in 2026 | USD 2.25 billion |
| Total Market Size in 2031 | USD 3.31 billion |
| Forecast Unit | USD Billion |
| Growth Rate | 8.03% |
| Study Period | 2021 to 2031 |
| Historical Data | 2021 to 2024 |
| Base Year | 2025 |
| Forecast Period | 2026 – 2031 |
| Segmentation | Type of Flu, Offering, Age Group, End-User, Country |
| Companies |
|
| Customization Scope | 15% Free Customization included with purchase — Request Custom Breakdown → |
| Sample & Data Access | PDF Sample, Excel Databook & Analyst Briefing — Download Free Sample → |
Market Segmentation
By Type of Flu
Type A
Type B
By Offering
Diagnostics
Rapid Influenza Diagnostic Test
Rapid Molecular Assay
Others
Therapeutics
By Age Group
0–14 Years
15–64 Years
65 Years and Above
By End-user
Hospital Laboratory
Outpatient Clinic
Reference Laboratory
By Country
China
Japan
South Korea
India
Thailand
Indonesia
Taiwan
Others
Australia
Philippines
Vietnam
Other APAC Markets
Table of Contents
1. EXECUTIVE SUMMARY
1.1. Key Findings
1.2. Market Size and Growth, 2026–2031
1.3. Country and Treatment Outlook
2. MARKET SNAPSHOT
2.1. Market Overview
2.2. Market Definition
2.3. Scope of the Study
2.4. Market Segmentation
2.5. Currency, Base Year and Forecast Period
3. BUSINESS LANDSCAPE
3.1. Market Drivers
3.1.1. Clinical Need for Rapid Etiological Differentiation
3.1.2. Expansion of Formal Diagnostic Capacity
3.1.3. Greater Antiviral Access and Formulation Choice
3.1.4. Rising Need to Protect Older and Higher-Risk Patients
3.1.5. Integrated Laboratory Menus and Recurring Consumable Economics
3.2. Market Restraints
3.2.1. Seasonality and Forecast Instability
3.2.2. Affordability Gap Between Antigen and Molecular Testing
3.2.3. Procurement Pricing and Reimbursement Pressure
3.2.4. Antiviral Timing and Clinical Eligibility
3.2.5. Quality Assurance and Supply-Chain Requirements
3.3. Market Opportunities
3.4. Porter’s Five Forces Analysis
3.5. Industry Value Chain Analysis
3.6. Product Regulation and Clinical Practice
3.7. Strategic Recommendations
4. TECHNOLOGICAL OUTLOOK
4.1. Rapid Antigen Immunoassays
4.2. Rapid Molecular and Point-of-Care PCR
4.3. Multiplex and Central-Laboratory Platforms
4.4. Neuraminidase Inhibitors and Cap-Dependent Endonuclease Inhibitors
4.5. Diagnostic Workflow and Quality Assurance
5. APAC FLU DIAGNOSTIC AND TREATMENT MARKET BY TYPE OF FLU
5.1. Introduction
5.2. Type A
5.3. Type B
6. APAC FLU DIAGNOSTIC AND TREATMENT MARKET BY OFFERING
6.1. Introduction
6.2. Diagnostics
6.2.1. Rapid Influenza Diagnostic Test
6.2.2. Rapid Molecular Assay
6.2.3. Others
6.3. Therapeutics
7. APAC FLU DIAGNOSTIC AND TREATMENT MARKET BY AGE GROUP
7.1. Introduction
7.2. 0–14 Years
7.3. 15–64 Years
7.4. 65 Years and Above
8. APAC FLU DIAGNOSTIC AND TREATMENT MARKET BY END-USER
8.1. Introduction
8.2. Hospital Laboratory
8.3. Outpatient Clinic
8.4. Reference Laboratory
9. APAC FLU DIAGNOSTIC AND TREATMENT MARKET BY COUNTRY
9.1. Introduction
9.2. China
9.3. Japan
9.4. South Korea
9.5. India
9.6. Thailand
9.7. Indonesia
9.8. Taiwan
9.9. Others
9.9.1. Australia
9.9.2. Philippines
9.9.3. Vietnam
9.9.4. Other APAC Markets
10. COMPETITIVE ENVIRONMENT AND ANALYSIS
10.1. Major Players and Strategy Analysis
10.2. Diagnostics Versus Therapeutics Competition
10.3. Market Share and Sourcing Structure
10.4. Agreements, Launches and Collaborations
10.5. Competitive Dashboard
11. COMPANY PROFILES
11.1. F. Hoffmann-La Roche Ltd.
11.2. Shionogi & Co., Ltd.
11.3. Abbott Laboratories
11.4. Cepheid
11.5. Becton, Dickinson and Company
11.6. QuidelOrtho Corporation
11.7. Seegene, Inc.
11.8. SD Biosensor, Inc.
11.9. bioMérieux SA
11.10. Hologic, Inc.
11.11. QIAGEN N.V.
11.12. Daiichi Sankyo Company, Limited
12. APPENDIX
12.1. Currency
12.2. Assumptions
12.3. Base and Forecast Years Timeline
12.4. Research Methodology
12.5. Abbreviations
12.6. Key Benefits for Stakeholders





Frequently asked questions
What is the projected market value of the APAC Flu Diagnostic and Treatment Market by 2031?
The Asia Pacific (APAC) Flu Diagnostic and Treatment Market is projected to reach USD 3.31 billion by 2031, at 8.03% CAGR.
Which influenza type holds the largest market share?
Influenza A represents approximately 76% of the 2026 market value.
Which APAC country leads regional expenditure for flu diagnostics and treatment?
China leads regional expenditure, while India shows strong expansion trajectory.
What are the principal commercial categories in this market?
Rapid antigen, molecular POC, central-lab PCR, and prescription antivirals.
Who are the prominent diagnostic and treatment suppliers mentioned?
Roche, Abbott, BD, Seegene for diagnostics; Shionogi and Roche for antivirals.
What factors influence market revenue generation?
Reimbursement, seasonal disease activity, and primary care access determine revenue.
Cite this report
Knowledge Sourcing Intelligence. (Oct 2026). Asia Pacific (APAC) Flu Diagnostic and Treatment Market - Strategic Insights and Forecasts (2026-2031). https://www.knowledge-sourcing.com/report/asia-pacific-apac-flu-diagnostic-and-treatment-market