Acoustic Neuroma Treatment Market - Strategic Insights and Forecasts (2026-2031)
Acoustic Neuroma Treatment Market Size, Share, Forecasts and Trends Analysis By Device Type (Radiosurgery Devices, Neurosurgical Instruments & Implants, Imaging & Navigation, Others), By Treatment Type (Surgical Intervention, Radiation Therapy, Others), By End-user (Hospitals, Clinics/Specialty Clinics, Others), and Region
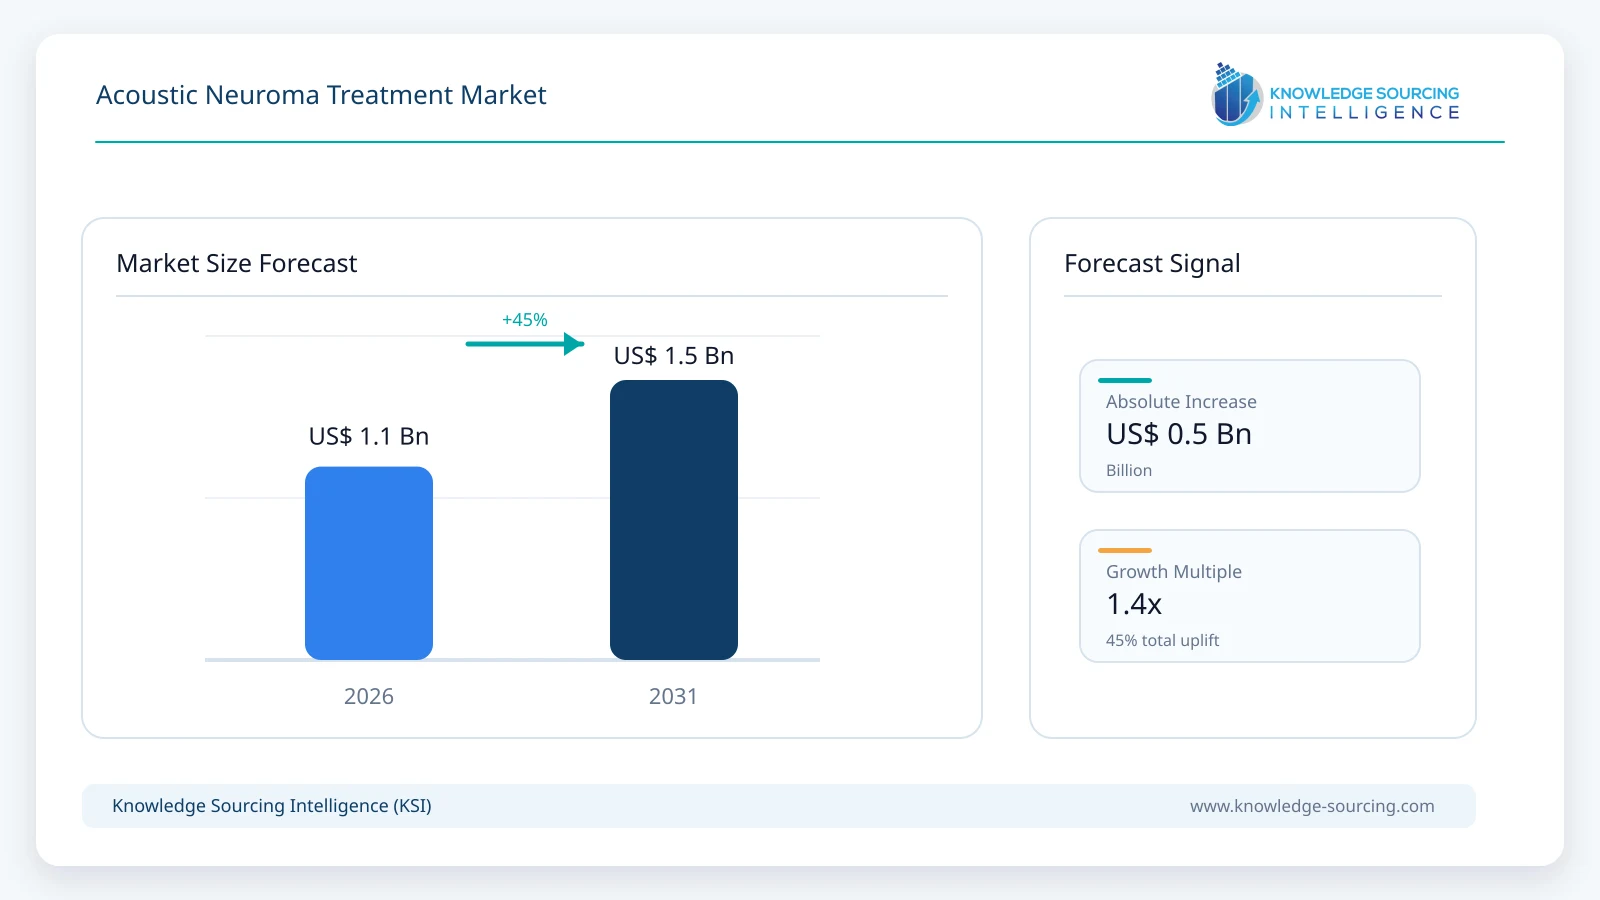
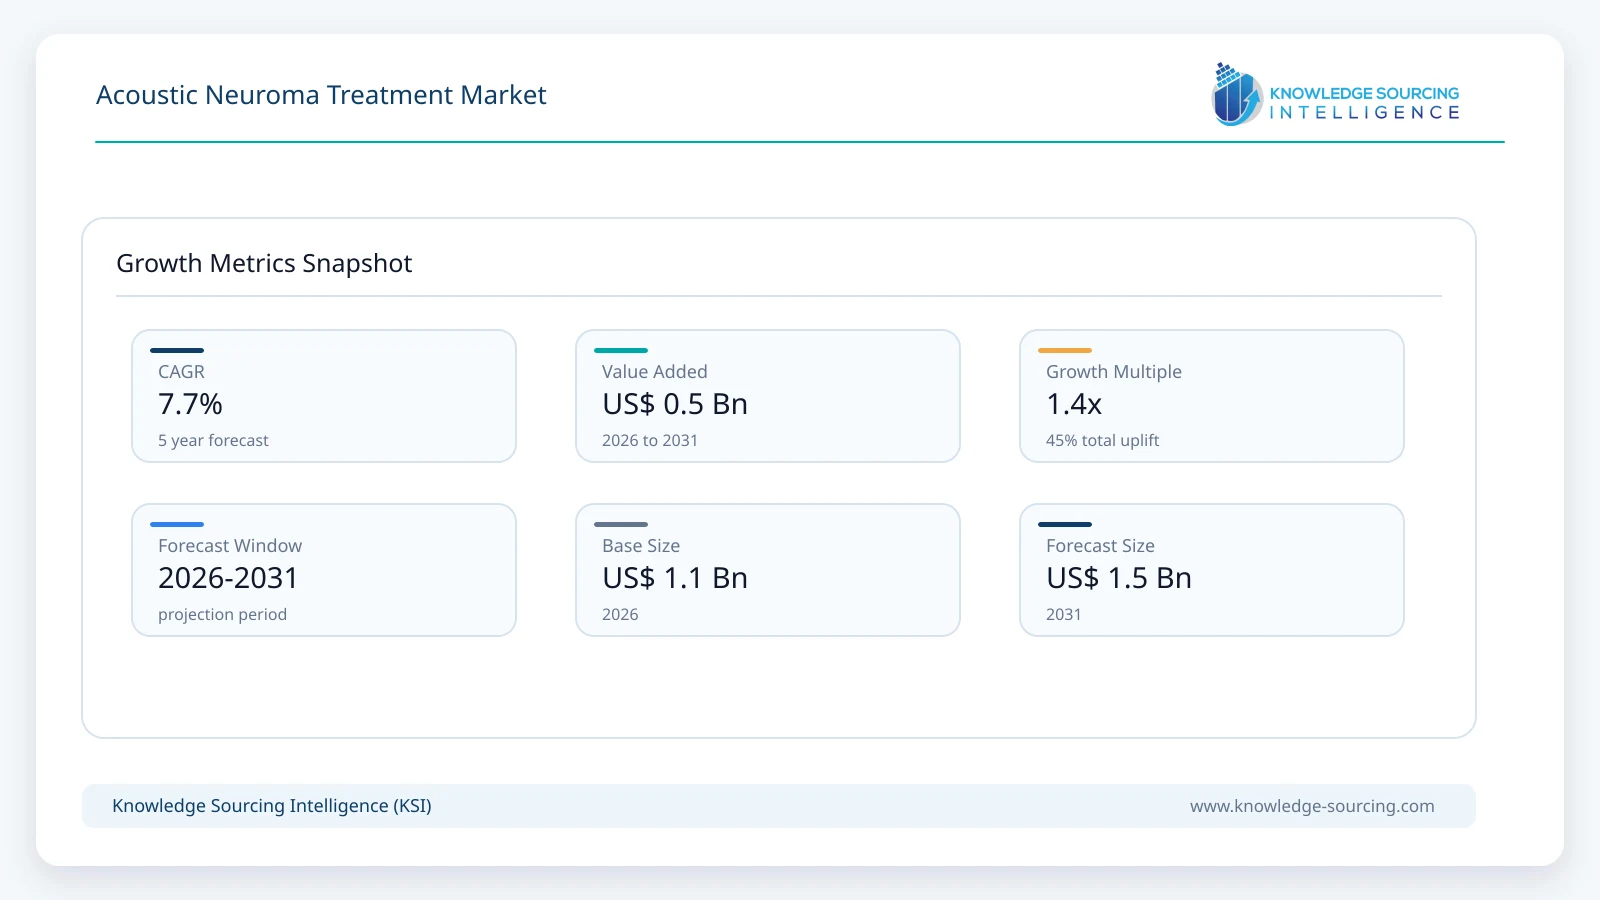
The global Acoustic Neuroma Treatment Market is expected to grow at a CAGR of 7.68%, reaching approximately USD 1.52 billion in 2031 from USD 1.05 billion in 2026.
Highlights:
1
MRI-led detection is increasing the share of patients entering structured surveillance, making serial imaging and follow-up a central component of service demand.
2
Radiosurgery has a strong position in selected small and medium lesions, particularly when a non-invasive strategy is appropriate; clinical choice remains individualized.
3
Complex skull-base operations preserve demand for specialized microscopes, nerve monitoring, navigation and experienced multidisciplinary surgical teams.
4
Functional outcomes, especially serviceable hearing and facial nerve function, increasingly influence treatment protocols and equipment selection.
5
North America benefits from established radiosurgery and referral-center capacity; Asia Pacific has expanding opportunities in diagnostic access and tertiary care.
6
Device suppliers compete through precision, workflow integration, installed-base support and training rather than through acoustic-neuroma-specific platforms alone.
Acoustic neuroma treatment involves medical services and technology used to manage a usually benign tumor arising from the vestibular division of the eighth cranial nerve. The pathway begins with MRI and hearing assessment and may continue with periodic monitoring, stereotactic radiation or microsurgical removal. At the provider level, the most important expenditures relate to skull-base procedures, radiosurgery delivery, specialist imaging and follow-up. Selection depends on tumor location and size, interval growth, neurological deficits, hearing status and patient preference rather than on one universal treatment protocol.
Elekta’s Leksell Gamma Knife, Accuray’s CyberKnife and linear-accelerator-based platforms support different approaches to conformal irradiation. Microsurgical programs rely on operating microscopes, navigation tools, nerve-monitoring equipment and experienced neuro-otology and neurosurgery teams. Brainlab’s cranial radiosurgery planning tools and ZEISS’s KINEVO visualization platform demonstrate the importance of software and image quality alongside the principal intervention. Hospitals generally purchase these capabilities for many neurological indications, so acoustic-neuroma demand is one part of the clinical utilization underpinning equipment investment.
Market Overview
Vestibular schwannomas are often discovered during investigation of asymmetric hearing loss, tinnitus or balance symptoms. Modern MRI reveals small intracanalicular tumors that might previously have remained undiagnosed until later presentation. This changes the treatment mix: more patients can be offered observation with defined imaging intervals, although surveillance is an active clinical commitment rather than a guarantee that treatment will never be necessary. An English registry study reported 2.2 newly diagnosed cases per 100,000 person-years, while a systematic review found higher rates in several well-characterized populations. Differences in registry capture and access to MRI must be considered when comparing patient volumes across countries.
Radiosurgery and microsurgery address different clinical needs. Congress of Neurological Surgeons guideline updates published in 2025 reinforce careful assessment of lesion features and patient circumstances, without establishing blanket superiority of one modality. Gamma Knife, CyberKnife and suitable linear-accelerator systems support highly conformal radiation delivery; surgical resection remains important for large lesions causing mass effect or for cases requiring decompression. Integrated skull-base programs increasingly coordinate neurosurgical, otological, radiation oncology and neuro-radiology expertise so that patients are assessed across available options rather than channeled toward the technology owned by an individual department.
Treatment capacity depends on the wider market for neurological procedures. A high-volume Gamma Knife center may treat vascular lesions, metastases and meningiomas alongside schwannomas, and the same applies to advanced surgical microscopes. For technology providers, clinical utilization, equipment renewal, software compatibility and maintenance therefore matter more than standalone acoustic-neuroma unit shipments. Longer follow-up also creates recurring requirements for MRI interpretation, audiometry and post-treatment assessments, linking the patient pathway to imaging and specialty clinical services.
Market Trends
MRI Detection Is Enlarging the Monitored Patient Population
Greater availability of high-resolution MRI has changed the profile of vestibular schwannoma referrals. Small intracanalicular tumors account for an important proportion of contemporary diagnoses, and clinicians may monitor stable lesions rather than initiate immediate radiation or surgery. This increases the need for imaging protocols that produce reproducible measurements and for coordinated review of hearing function. The clinical aim is to identify growth or deterioration early enough to reconsider treatment without subjecting every patient to an intervention.
For hospitals, surveillance entails repeat scanner time, image reporting and specialist consultations, but the number and frequency of visits depend on clinical risk and local protocols. The prevalence of observation in population-based studies also cautions against estimating procedure revenue by applying a treatment price to every new diagnosis. Providers with organized multidisciplinary surveillance pathways may retain patients over several years while intervening selectively.
Radiosurgery Procurement Is Shifting Toward Planning Accuracy and Workflow
Gamma Knife and robotic or conventional LINAC radiosurgery platforms increasingly compete on target definition, image registration, conformity and efficient delivery rather than simply on maximum radiation output. Cochlear and facial-nerve preservation concerns place additional scrutiny on treatment plans for vestibular schwannoma, particularly when patients retain serviceable hearing. Brainlab’s indication-specific cranial SRS platform illustrates how automation-assisted contouring and dose planning can support consistent workflows.
A single acquisition is rarely justified by acoustic-neuroma throughput alone. Purchasers examine the combined intracranial case mix, clinical staffing, quality assurance and post-installation support. Accuray’s 2025 account of long-term CyberKnife experience for vestibular schwannoma adds clinical evidence, but study-specific outcomes should not be interpreted as comparative proof that one system is superior for every patient.
Nerve-Preserving Skull-Base Surgery Favors Integrated Visualization
Microsurgical management remains indispensable where the tumor threatens brainstem structures or where decompression is necessary. Surgeons balance completeness of removal against facial and cochlear nerve function, particularly when the tumor capsule adheres to delicate anatomy. ZEISS’s KINEVO 900 S combines magnified optics with 4K three-dimensional visualization, while intraoperative electrophysiological monitoring supports nerve identification during complex cases.
Adoption depends on surgeon familiarity, an operating-room team trained in skull-base techniques, and institutional case volumes. Digital views can improve teaching and team communication, but they do not independently establish better hearing or facial-nerve outcomes. Hospitals consequently assess microscope upgrades alongside navigation compatibility, maintenance cost and the broader neurosurgical procedures that share the equipment.
Combined Surgery and Radiation Is Receiving More Structured Guidance
Planned subtotal resection followed by stereotactic irradiation is being studied for large lesions when aggressive excision threatens neurological function. International Stereotactic Radiosurgery Society practice recommendations outline scenarios for a staged approach, emphasizing cranial-nerve preservation, multidisciplinary timing and MRI assessment of residual disease. Such management requires coordinated care rather than a simple substitution of one modality for another.
The care pathway can extend beyond a single hospital department and may involve referral from a regional surgical center to a radiation facility. Commercially, this rewards dependable image transfer, compatible planning data and clear handover responsibilities. The clinical evidence remains heterogeneous, so combined treatment is unlikely to become an automatic protocol for every large schwannoma.
Long-Term Outcomes Are Becoming Central to Technology Assessment
Vestibular schwannoma management is evaluated over years because tumor growth, hearing changes and radiation effects can evolve long after the initial decision. Contemporary guidance places emphasis on serial MRI, hearing preservation and adverse-effect monitoring, narrowing the usefulness of short-term control statistics as standalone procurement arguments. The priority is durable tumor management with acceptable neurological function.
For suppliers, better plan documentation and longitudinal outcome collection may become more valuable than adding isolated automation features. Hospitals comparing treatment pathways must also account for ongoing follow-up, revision procedures and rehabilitation needs. This favors technology that fits documented clinical protocols and provides reproducible information for the entire patient journey.
Segment Analysis
By Device Type: Radiosurgery Devices
Radiosurgery systems represent a major device-related expenditure category because stereotactic radiation requires precise positioning, image guidance and dedicated planning. Treatment is especially relevant for selected smaller lesions and for patients for whom an open operation carries substantial risk. Elekta’s dedicated Gamma Knife architecture and Accuray’s robotic LINAC system compete alongside LINAC-based stereotactic programs deployed in broader radiation oncology departments.
Equipment selection depends on the whole intracranial treatment portfolio and available expertise. A dedicated system may offer specialized workflow, while a multipurpose platform can spread capital costs across several indications. Patient-specific planning, commissioning and longitudinal imaging are integral to value, but system-wide sales should not be treated as attributable acoustic-neuroma receipts.
By Treatment Type: Surgical Intervention
Surgical intervention retains a significant position because large tumors may compress the brainstem and require decompression that radiation cannot provide quickly. Retrosigmoid, translabyrinthine and middle fossa approaches serve different anatomical and functional requirements. The appropriate technique depends on tumor extension, existing hearing and the likelihood of preserving nerve integrity rather than on a single dominant method.
High-volume skull-base centers tend to concentrate specialized expertise and related purchases, including nerve monitors, drills, microscopes and operative navigation. Some operations deliberately leave residual tumor when complete removal would jeopardize nerve function, with subsequent surveillance or irradiation decided case by case. Complex treatment therefore maintains demand for both surgical capacity and multidisciplinary follow-up.
By End User: Hospitals
Hospitals represent the principal treatment setting because radiosurgery and skull-base operations require imaging, anesthesia or radiation physics support, multidisciplinary decision-making and emergency care access. University hospitals and specialist referral centers commonly manage more complex lesions, including patients with previous radiation or recurrent tumors. Their procurement decisions shape installed bases for high-end treatment systems.
Specialty clinics nevertheless contribute through diagnosis, patient counseling, audiology and follow-up. Hospital leadership evaluates technology against case mix, procedure scheduling, reimbursement and staff availability, rather than projecting an entire institution’s neurosurgery revenue onto one benign-tumor indication. Regional referral agreements also influence where patients receive surgery, radiation and longer-term surveillance.
Market Drivers
Rising Detection of Small and Previously Unrecognized Tumors
Contemporary MRI availability has increased identification of vestibular schwannomas that might otherwise have been diagnosed later. Smaller lesions often enter structured observation, creating demand for neuroradiology reporting, audiology and periodic specialist review. Population-based evidence indicates that tumor registration relying only on surgical or pathology records misses a substantial proportion of monitored patients.
Detection growth does not generate immediate surgery or radiosurgery in every case. It broadens the pool requiring management and may lead to later intervention if growth or symptoms change. Providers able to maintain reliable follow-up protocols benefit from a longer clinical relationship, while payers favor imaging schedules tied to documented risk.
Need to Preserve Hearing and Facial Nerve Function
Hearing outcomes and facial nerve function strongly influence decisions among observation, radiation and surgery. The updated Congress of Neurological Surgeons guidance emphasizes functional follow-up and the limitations of comparative evidence, reinforcing the importance of individualized care. This supports investment in high-resolution planning and operative monitoring across specialist programs.
Device suppliers must demonstrate compatibility with careful dose planning or nerve-sparing surgical techniques. Claims of improved outcomes require clinical validation, but hospitals already place commercial value on tools that help clinicians work consistently in anatomically constrained regions. Training and maintenance therefore form part of the purchase decision.
Increasing Use of Stereotactic Treatment in Suitable Patients
Stereotactic radiosurgery offers a non-invasive alternative for appropriately selected lesions and patients, avoiding prolonged post-operative recovery associated with open cranial surgery. Dedicated Gamma Knife units, robotic radiosurgery platforms and LINAC-based systems provide different pathways for hospitals seeking advanced care. Evidence from longer-term follow-up contributes to clinical confidence.
Commercial growth depends on the installed base of qualified centers and on patients being referred early enough for radiotherapy to remain appropriate. Large tumors and selected symptomatic cases still need surgical assessment, so radiosurgery expands the treatment toolkit rather than replacing microsurgical capacity.
Investment in Specialist Neurosurgical Infrastructure
Skull-base surgery requires experienced personnel and connected equipment for visualization, neuromonitoring and image guidance. As tertiary hospitals modernize operating rooms, vendors supplying microscopes, instruments and planning systems can serve acoustic neuroma together with a much broader cranial surgery case mix. ZEISS has reported strong wider demand for its neurosurgical visualization technology.
Institutional economics matter as much as clinical technology. A center must sustain case throughput, surgical training and biomedical support after buying the equipment. Providers often concentrate highly complex patients into referral hospitals, creating opportunities for specialist networks rather than indiscriminate installation of high-end systems.
Expansion of Multidisciplinary Long-Term Care Pathways
Patients may require repeated MRI assessments, audiometry or rehabilitation during observation and after definitive intervention. Multidisciplinary pathways link otology, neurosurgery, radiation oncology and neuroradiology so that changes in tumor behavior or functional status are acted on consistently. Such organization supports continuing demand for specialist clinical services and imaging capacity.
Digital image comparison and standardized follow-up also improve the information available to clinicians. The economic effect arises from sustained service provision and better coordination, not from assuming that every surveillance visit leads to a high-value procedure.
Market Restraints
Capital Cost and Limited Utilization in Smaller Centers
Dedicated radiosurgery suites and complex cranial operating rooms carry substantial acquisition, shielding, commissioning and maintenance requirements. Acoustic neuroma is a relatively uncommon indication, so hospital investment must typically be justified across other intracranial conditions as well. Low expected case volumes make dedicated systems difficult to support outside referral centers.
Facilities may prefer referral arrangements or multipurpose equipment rather than purchasing a new platform. Smaller clinics also face ongoing physicist, imaging and technical-support obligations, which can constrain the geographic spread of advanced treatment capability.
Shortage of Experienced Skull-Base and Radiosurgery Teams
Treatment quality depends on specialists able to interpret complex imaging, assess hearing, plan conformal radiation and perform nerve-preserving surgery. Training pathways are long, and institutional case volume influences skill maintenance. A technically capable hospital may therefore remain unable to offer the complete care pathway without multidisciplinary staff.
Centralization improves specialist expertise but can impose travel and waiting burdens on patients. Vendors supplying instruments or software cannot overcome workforce limits through automation alone, and procurement cycles frequently include lengthy training and credentialing requirements.
Clinical Uncertainty in Selecting and Timing Treatment
Many newly detected lesions remain stable, while others grow or cause neurological impairment. Available evidence does not support one intervention as universally superior, and patients may weigh tumor control against risks to hearing and facial function differently. This variability limits the use of uniform treatment algorithms and makes procedure volumes difficult to forecast from incidence alone.
Clinicians may favor observation for selected patients, reducing near-term interventional demand. Conversely, inappropriate delay can complicate later management. Hospitals must support careful follow-up and shared decision-making rather than treating additional imaging findings as automatic procedure candidates.
Reimbursement and Geographic Access Differences
Patient access to microsurgery, radiosurgery and surveillance depends on national insurance arrangements, referral geography and available public hospital capacity. High-cost procedures are more concentrated in well-funded facilities, while rural and lower-income communities may face imaging delays or limited access to specialized teams.
Payment rules can also distinguish single-session radiosurgery, fractionated treatment and the imaging needed before and after care. Financial uncertainty slows equipment procurement and affects which modality can be offered without creating excessive patient costs.
Long Follow-Up and Functional Outcome Requirements
Clinical success cannot be judged solely by early tumor shrinkage. Surveillance after radiation or surgery may continue for years, and patients can experience hearing deterioration, imbalance or other neurological effects even when the lesion remains controlled. Providers must maintain imaging records, specialist appointments and outcome assessment beyond the initial episode.
Longitudinal care adds operational expense and complicates comparative evaluation of treatment systems. Hospitals procuring new technology increasingly demand reliable data exchange and planning documentation, while suppliers cannot present isolated short-term study outcomes as proof of durable superiority.
Regional Outlook
North America
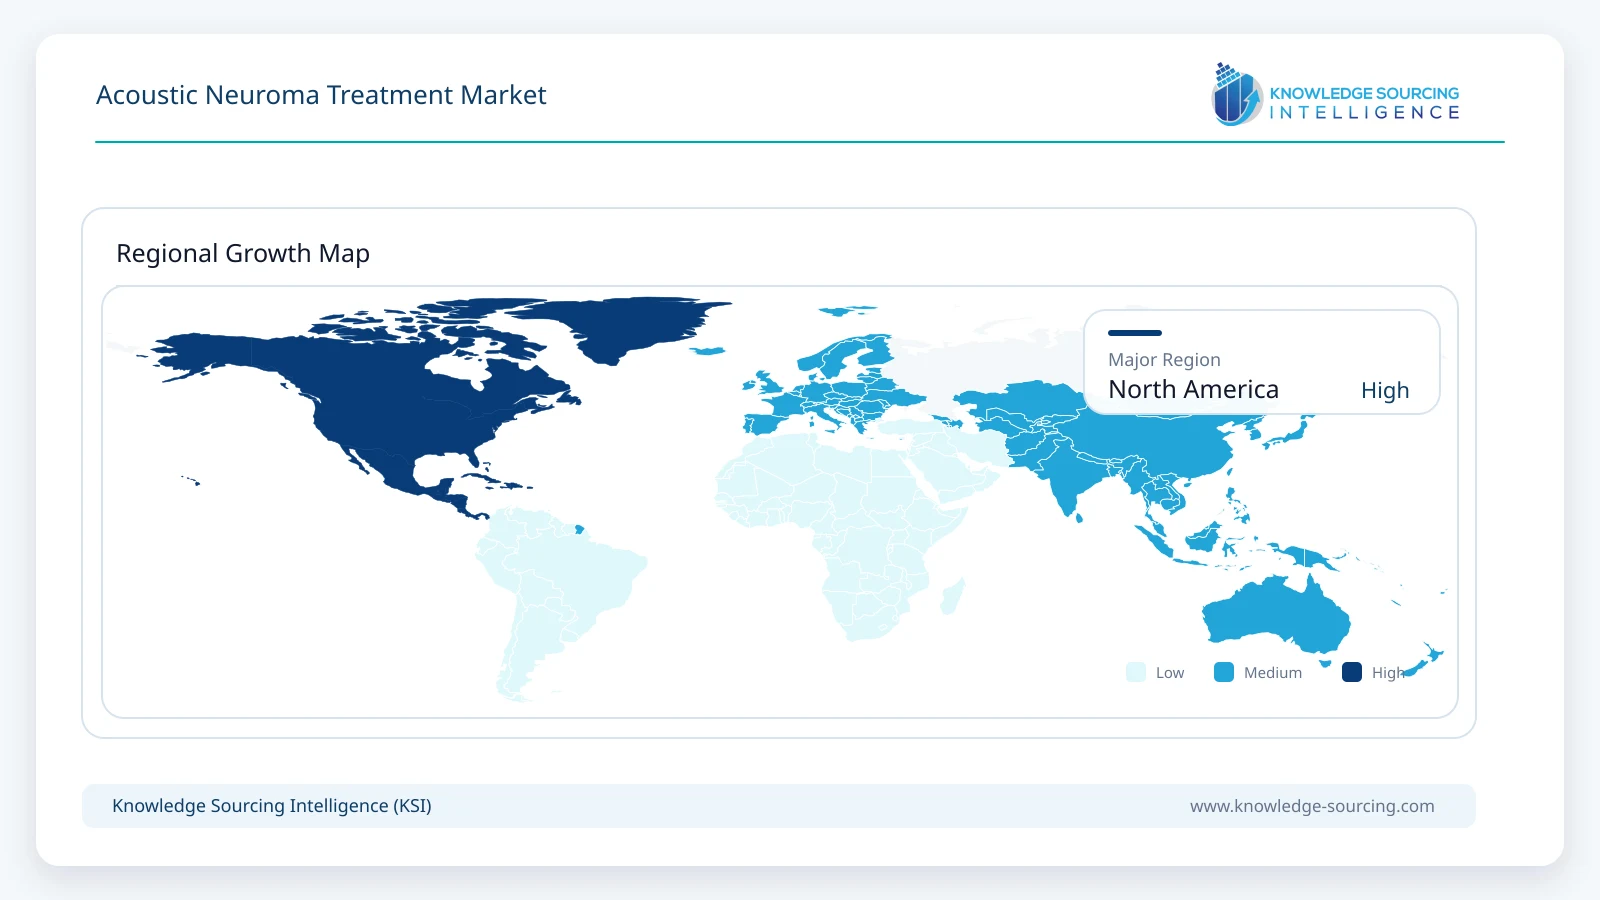
North America has the strongest concentration of established multidisciplinary skull-base and radiosurgery services, supported by the United States’ network of university hospitals, dedicated centers and broad availability of advanced imaging. The region hosts major research programs and clinical guideline development that influence treatment selection worldwide. Patients may access Gamma Knife, CyberKnife, LINAC radiosurgery or microsurgical expertise through specialized referral networks, although distribution is uneven outside large metropolitan areas.
Commercial opportunities arise in system replacement, software planning, image-guidance upgrades and long-term specialist follow-up. Payer policy and institutional case volumes remain decisive: new equipment is most economically attractive where a center treats several cranial indications and can retain experienced teams. Canada contributes publicly funded specialist programs, while Mexico has a more uneven mix of advanced private and public facilities.
Asia Pacific
Asia Pacific offers the fastest modeled expansion as access to diagnostic MRI and tertiary neurological services develops across China, India and Southeast Asia. Japan and South Korea already maintain sophisticated neurosurgical and radiation oncology infrastructure, while the needs of larger populations are driving investment in hospital specialization elsewhere. Greater detection of small lesions should increase monitored-care activity alongside selective use of surgery and radiosurgery.
Regional spending will not rise uniformly. Advanced systems remain concentrated in major urban centers, reimbursement arrangements differ substantially, and shortages of experienced skull-base personnel can limit the practical use of purchased technology. Suppliers able to provide education, local service support and interoperable planning systems may be better positioned than firms offering equipment without a supporting clinical ecosystem.
Competitive Landscape
Precision-radiation suppliers compete through delivery technology, intracranial treatment experience and supporting software. Elekta has a dedicated Gamma Knife franchise, Accuray supplies the robotic CyberKnife system, and Siemens Healthineers’ Varian business supports LINAC-based radiation oncology platforms. Brainlab operates in image fusion and cranial planning, creating a different commercial relationship with institutions than manufacturers that provide the full radiation delivery system. These products serve many neurological indications, so company revenue cannot be interpreted as acoustic-neuroma market share.
Microsurgical equipment suppliers form another competitive group. ZEISS and Leica Microsystems supply visualization technologies; Medtronic, Stryker and Integra LifeSciences participate in cranial instruments, equipment and operating-room workflows, while nerve monitoring specialists address functional protection during complex surgery. Buyers evaluate installed compatibility, service access and training alongside image quality. Concentration of procedures at specialist hospitals can favor established supplier relationships, although new platforms can gain consideration when evidence and economics justify replacement.
Pharmaceutical development remains a distinct research field, not a substitute for current procedural management. The KSI source page identifies several hearing-oriented biotechnology companies, but their presence should not be taken as proof of approved disease-modifying drugs for sporadic vestibular schwannoma. Commercial competition is consequently centered on procedural technology and the multidisciplinary capabilities that support treatment and monitoring.
Recent Developments
February 2026: The Congress of Neurological Surgeons hearing-preservation guideline update appeared in Neurosurgery, compiling contemporary evidence on functional outcomes after observation, surgery and radiation. It reinforced the importance of long-term hearing measures when comparing management strategies.
September 2025: Elekta announced that cumulative global treatment with Leksell Gamma Knife had passed two million patients across indications. The milestone demonstrates the platform’s installed clinical history, without establishing acoustic-neuroma-specific procedure volume.
June 2025: The Congress of Neurological Surgeons issued an updated evidence review for surgical resection of sporadic vestibular schwannoma, addressing hearing preservation, surgical approaches and salvage procedures after radiation.
June 2025: The Congress of Neurological Surgeons updated its guidance on stereotactic radiosurgery and radiotherapy for vestibular schwannoma, emphasizing evidence limitations, follow-up and treatment considerations.
April 2025: Accuray highlighted a 25-year single-institution CyberKnife experience in vestibular schwannoma at the Radiosurgery Society meeting, reporting long-term local-control results for that cohort rather than a randomized technology comparison.
Market Outlook
Acoustic neuroma care through 2031 is likely to involve a greater proportion of small tumors managed under structured observation, alongside continued demand for radiotherapy and surgery in selected patients. Referral networks will place more weight on evidence of hearing and facial-nerve outcomes, making sustained multidisciplinary expertise a critical differentiator. Expanding MRI availability can increase case identification, but the commercial effect will vary according to the proportion of patients whose tumors require intervention.
Technology investment should favor reliable cranial planning, accurate radiation delivery and integrated visualization for complex surgery. North America will remain an established technology and service market, while the Asia Pacific opportunity will depend on the pace of tertiary-care expansion and specialist workforce development. Manufacturers with strong service networks and software interoperability are likely to remain important partners to hospitals, but procedural growth will be constrained by capital cost and clinical selection rather than by diagnosis volumes alone.
Acoustic Neuroma Treatment Market Scope
Report Metric
Details
Total Market Size in 2026
USD 1.05 billion
Total Market Size in 2031
USD 1.52 billion
Forecast Unit
Billion
Growth Rate
7.68%
Study Period
2021 to 2031
Historical Data
2021 to 2024
Base Year
2025
Forecast Period
2026 – 2031
Segmentation
Device Type, Treatment Type, End User, Geography
Companies
Acousia Therapeutics GmbH
Decibel Therapeutics
Rinri Therapeutics
Eli Lily
Astellas Pharma
Market Segmentation
By Device Type
Radiosurgery Devices
Neurosurgical Instruments & Implants
Imaging & Navigation
Others
By Treatment Type
Surgical Intervention
Radiation Therapy
Others
By End User
Hospitals
Clinics/Specialty Clinics
Others
By Geography
North America
United States
Canada
Mexico
South America
Brazil
Argentina
Others
Europe
United Kingdom
Germany
France
Spain
Others
Middle East and Africa
Saudi Arabia
United Arab Emirates
Israel
Others
Asia Pacific
China
India
Japan
South Korea
Taiwan
Thailand
Indonesia
Others
Table of Contents
1. EXECUTIVE SUMMARY
1.1. Key Findings
1.2. Market Outlook
1.3. Regional Opportunity Summary
2. MARKET SNAPSHOT
2.1. Market Overview
2.2. Market Definition
2.3. Scope of the Study
2.4. Market Segmentation
3. BUSINESS LANDSCAPE
3.1. Market Drivers
3.1.1. Rising Detection of Small and Previously Unrecognized Tumors
3.1.2. Need to Preserve Hearing and Facial Nerve Function
3.1.3. Increasing Use of Stereotactic Treatment in Suitable Patients
3.1.4. Investment in Specialist Neurosurgical Infrastructure
3.1.5. Expansion of Multidisciplinary Long-Term Care Pathways
3.2. Market Restraints
3.2.1. Capital Cost and Limited Utilization in Smaller Centers
3.2.2. Shortage of Experienced Skull-Base and Radiosurgery Teams
3.2.3. Clinical Uncertainty in Selecting and Timing Treatment
3.2.4. Reimbursement and Geographic Access Differences
3.2.5. Long Follow-Up and Functional Outcome Requirements
3.3. Market Opportunities
3.4. Porter’s Five Forces Analysis
3.5. Industry Value Chain Analysis
3.6. Policies and Regulations
3.7. Strategic Recommendations
4. TECHNOLOGICAL OUTLOOK
4.1. High-Resolution MRI and Surveillance
4.2. Gamma Knife and Robotic Radiosurgery
4.3. LINAC-Based Stereotactic Radiation
4.4. Cranial Navigation and Treatment Planning
4.5. Surgical Visualization and Nerve Monitoring
5. ACOUSTIC NEUROMA TREATMENT MARKET BY DEVICE TYPE
5.1. Introduction
5.2. Radiosurgery Devices
5.3. Neurosurgical Instruments & Implants
5.4. Imaging & Navigation
5.5. Others
6. ACOUSTIC NEUROMA TREATMENT MARKET BY TREATMENT TYPE
6.1. Introduction
6.2. Surgical Intervention
6.3. Radiation Therapy
6.4. Others
7. ACOUSTIC NEUROMA TREATMENT MARKET BY END USER
7.1. Introduction
7.2. Hospitals
7.3. Clinics/Specialty Clinics
7.4. Others
8. ACOUSTIC NEUROMA TREATMENT MARKET BY GEOGRAPHY
8.1. Introduction
8.2. North America
8.2.1. United States
8.2.2. Canada
8.2.3. Mexico
8.3. South America
8.3.1. Brazil
8.3.2. Argentina
8.3.3. Others
8.4. Europe
8.4.1. United Kingdom
8.4.2. Germany
8.4.3. France
8.4.4. Spain
8.4.5. Others
8.5. Middle East and Africa
8.5.1. Saudi Arabia
8.5.2. United Arab Emirates
8.5.3. Israel
8.5.4. Others
8.6. Asia Pacific
8.6.1. China
8.6.2. India
8.6.3. Japan
8.6.4. South Korea
8.6.5. Taiwan
8.6.6. Thailand
8.6.7. Indonesia
8.6.8. Others
9. COMPETITIVE ENVIRONMENT AND ANALYSIS
9.1. Major Players and Strategy Analysis
9.2. Market Share Analysis
9.3. Mergers, Acquisitions, Agreements and Collaborations