
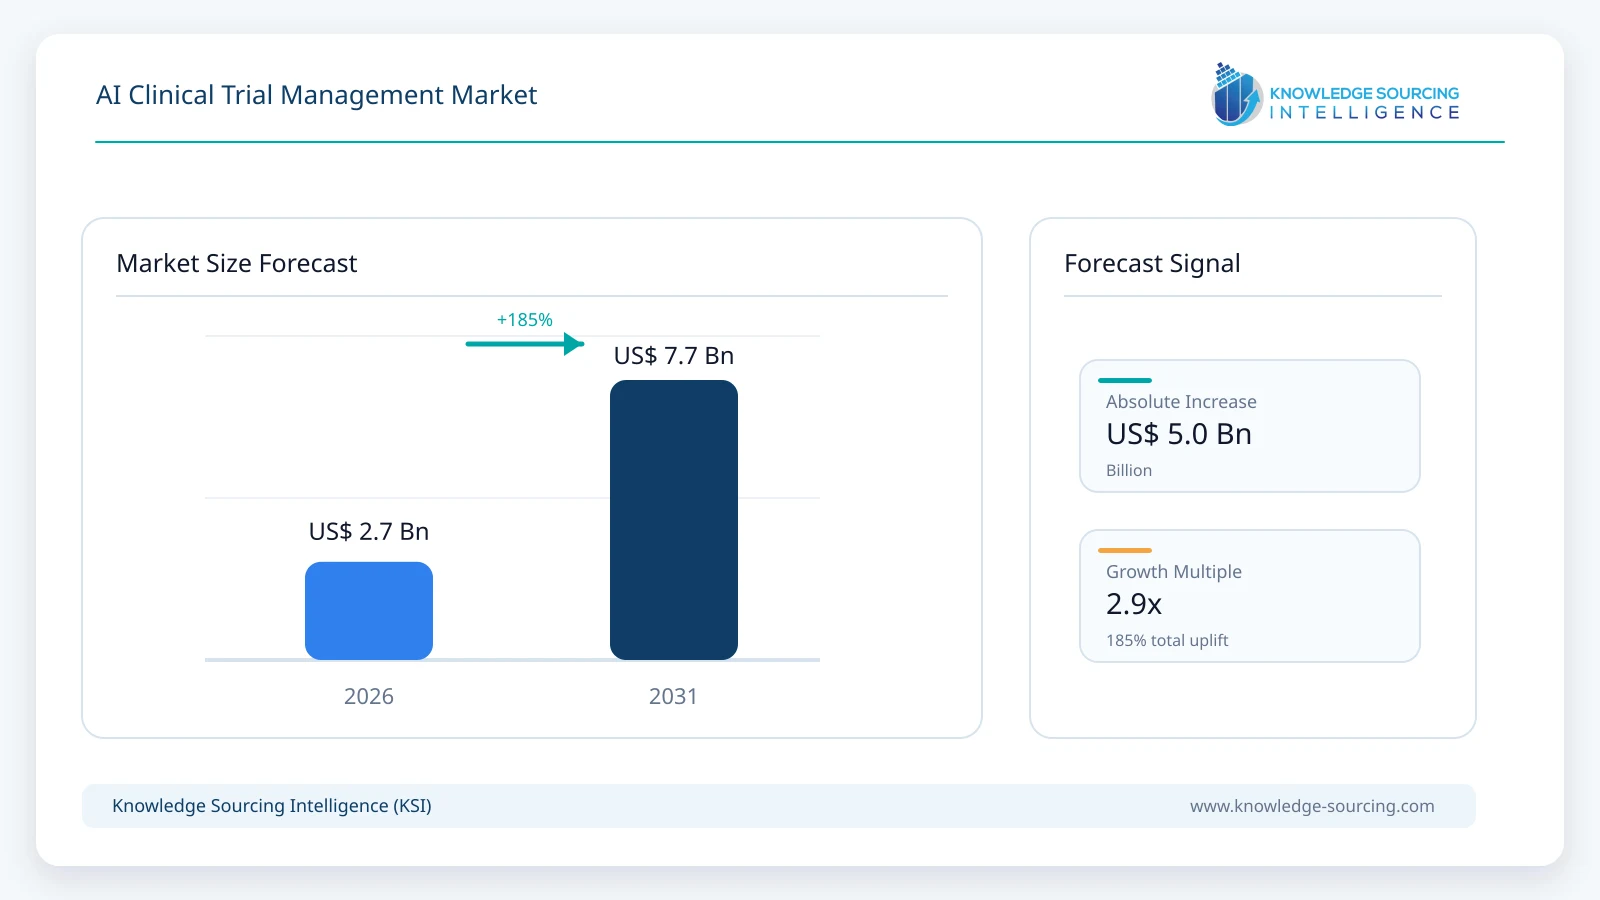
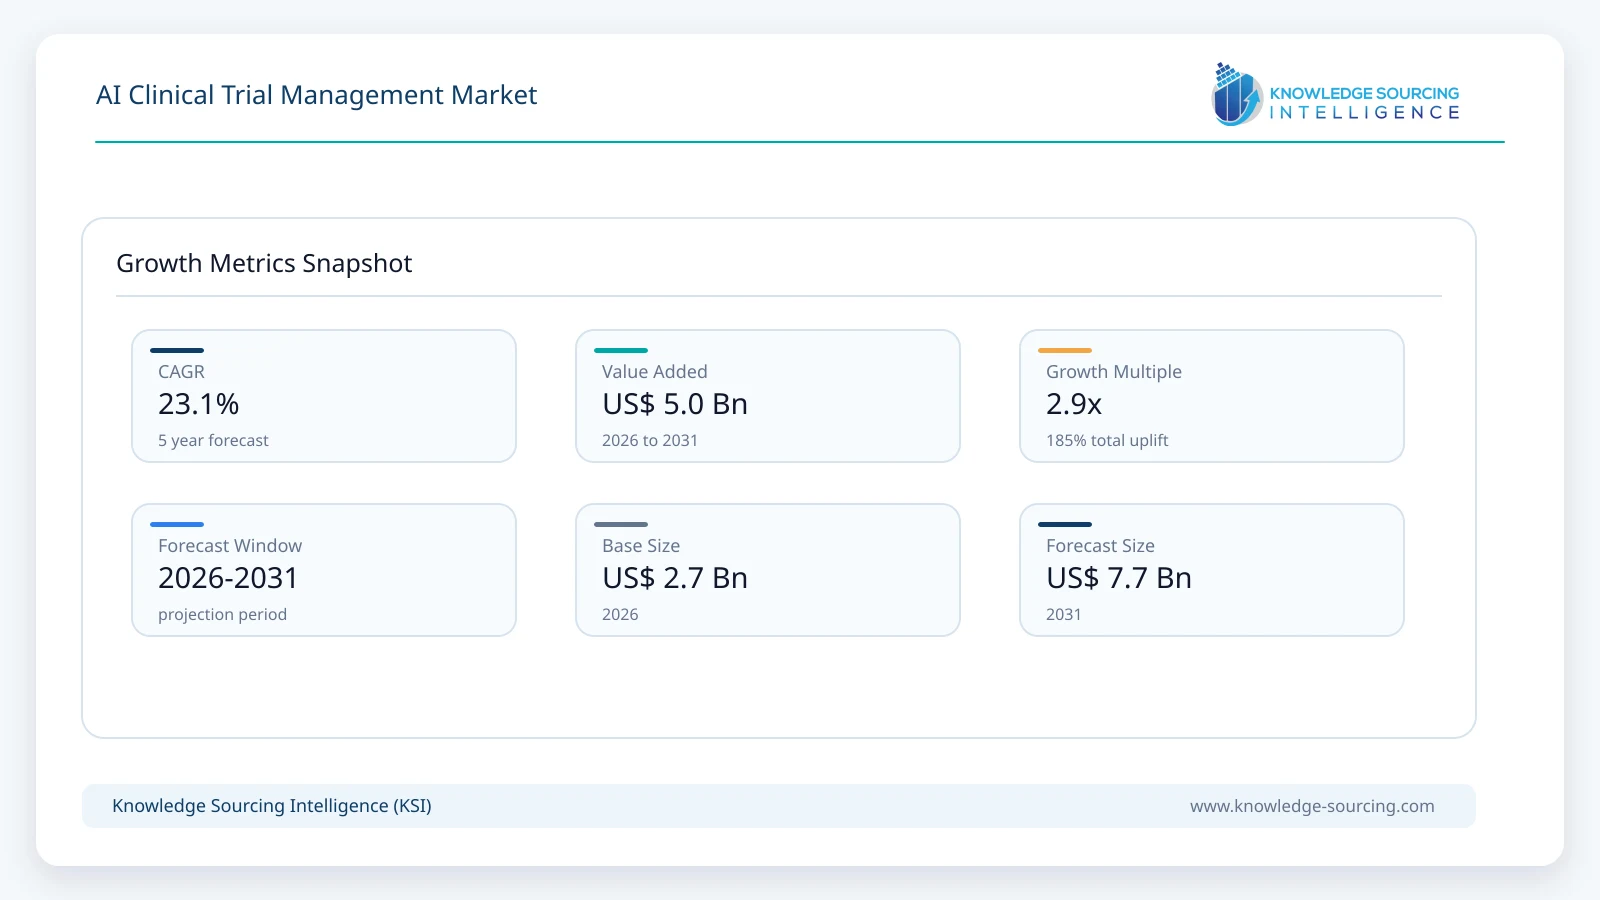
The AI-Powered Clinical Trial Management Market is projected to grow from USD 2.7 billion in 2026 to USD 7.7 billion by 2031, at a CAGR of 23.1% over the forecast period.
Highlights:
- 1Protocol-to-study configuration is receiving investment as sponsors seek to reduce manual setup and amendments.
- 2AI-supported data review and medical imaging can address specific bottlenecks when supported by validation and human oversight.
- 3Predictive Analytics contributes to feasibility, enrollment forecasting and risk-based site monitoring.
- 4Pharmaceutical companies set enterprise technology standards, while CROs influence implementation and integration.
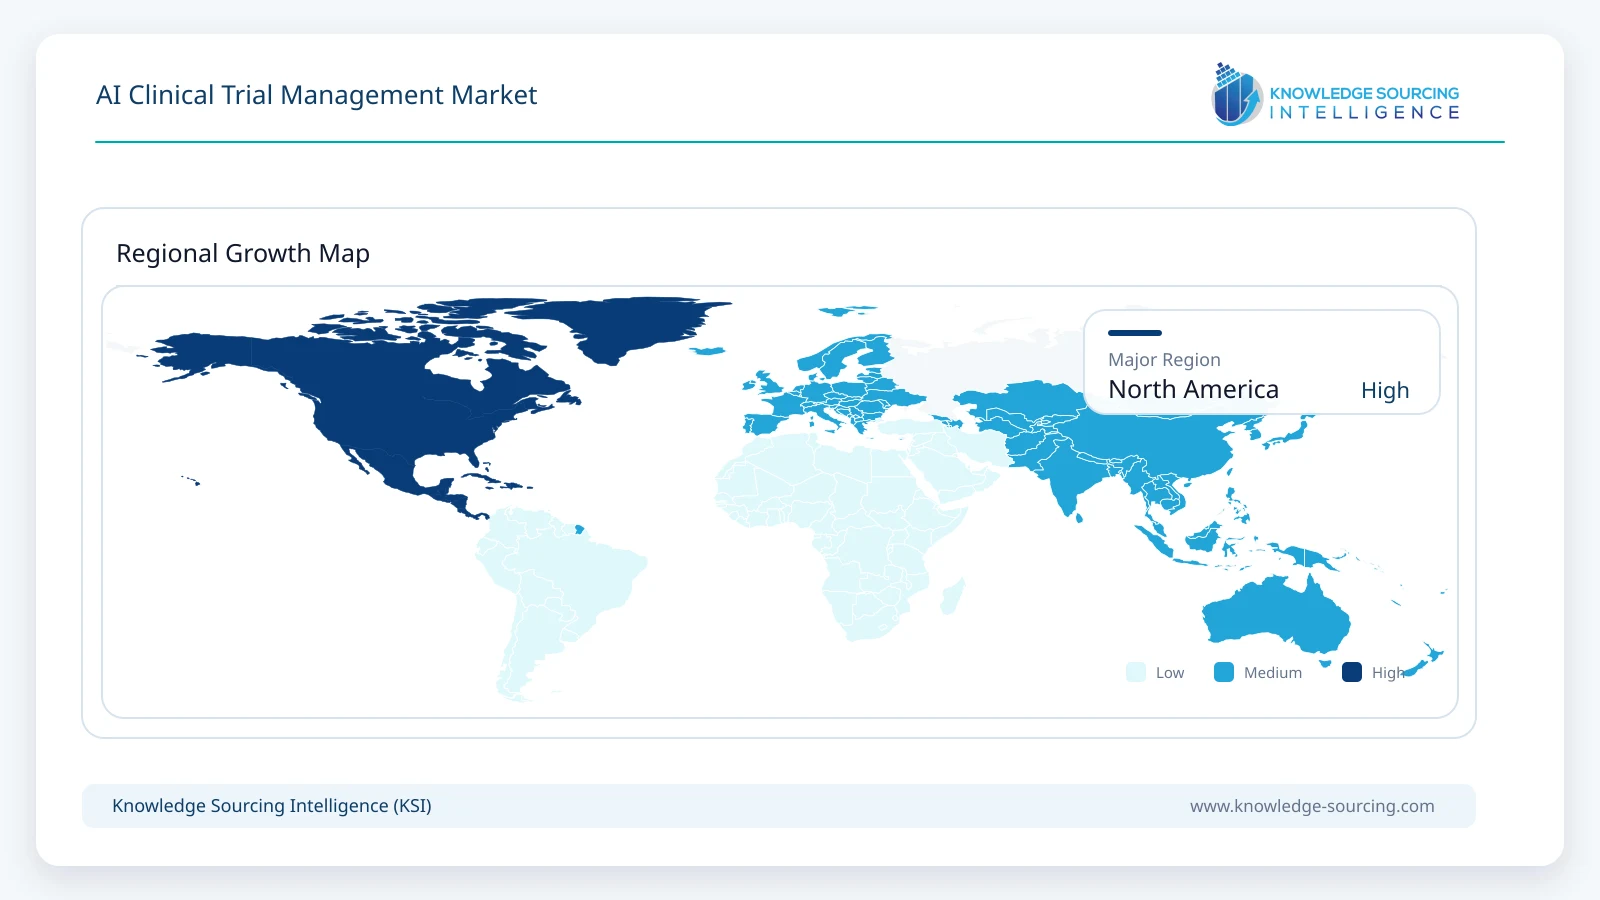
- 5North America benefits from a substantial sponsor and trial-software ecosystem; Asia Pacific is expanding through research capacity and global studies.
- 6Trial oversight, model-change control, data traceability and participant protection remain decisive adoption requirements.
The market comprises identifiable AI-enabled software and specialist services used to plan, operate, monitor and analyze interventional clinical trials. Relevant products include protocol intelligence, feasibility and recruitment analytics, data-review automation, risk-based monitoring, medical-image interpretation and safety-signal analysis. Entire drug-development budgets, ordinary CRO labor receipts and conventional EDC or CTMS subscriptions without attributable AI functionality are not automatically equivalent to AI market revenue.
Trial technology is sold into a highly controlled operating environment. A sponsor may outsource execution to a CRO while retaining accountability for trial quality. Investigative sites capture patient information, laboratories provide endpoint results and sponsors consolidate evidence in systems that can undergo inspection. An AI model must fit this chain of responsibility, especially where it changes participant eligibility interpretation, protocol implementation, critical data flags or safety review.
Clinical Trial Planning and Design, Patient Recruitment and Enrollment, Data Management and Analysis, Monitoring and Oversight, and Safety and Pharmacovigilance form the solution taxonomy. The functional axis includes Predictive Analytics, NLP, Machine Learning, RPA, and Image and Signal Processing. Most modern products use several functions, so these independent axes should not be totaled together.
In October 2026, IQVIA selected Veeva CTMS, eTMF, Study Startup and Site Connect as enterprise-standard applications across its clinical development studies. The procurement extends their earlier EDC partnership and points toward integrated operating records rather than isolated AI plug-ins. It should not be interpreted as evidence that the complete software contract represents artificial-intelligence revenue. The value for a sponsor lies in reducing reconciliation among site start-up, trial documentation, data capture and operational oversight, with consistent rights and inspection-ready records.
The FDA’s April 2026 real-time trial initiative provides another test of clinical information flows. AstraZeneca and Amgen launched proof-of-concept studies to share selected endpoint and safety signals more promptly with the agency. Such programs encourage clearer data definitions and faster exception handling, but they do not relax responsibility for participant protection or protocol compliance. Predictive alerts need qualified reviewers, threshold controls and a documented response. A system that identifies an anomaly without helping the study team investigate it may simply increase work.
Market Trends
Protocol intelligence is entering validated study configuration
Veeva announced its Study Builder Agent on September 24, 2026, for converting a protocol and an organization’s standards into EDC forms, visit schedules, edit checks and data-quality listings. It uses the CDISC Unified Study Definitions Model to reduce repeated interpretation between clinical operations and study-build teams. Early-adopter availability is planned for December 2026, so the announcement should not be mistaken for evidence of broad current deployment. Sponsor validation of the generated configuration, change history and acceptance tests remains a necessary step before production use.
AI layers are consolidating around clinical platform data
Medidata launched Medidata Plus in July 2026 as an AI layer intended to operate across clinical portfolios. Its value proposition depends on connecting protocol, site, patient and data workflows that already use different applications. Platform integration reduces duplicated data transfers and helps build consistent monitoring views. The trade-off is deeper dependence on the vendor’s data model and change-management procedures. Specialist products continue to compete when they deliver superior evidence for a defined clinical task.
Medical imaging workflows are becoming a practical automation target
At ESMO in October 2026, Medidata described enhancements to imaging quality control and protected-health-information redaction, reporting more than 97% accuracy for its anatomy verification capability and 32% faster automated redaction in its own testing. Both are vendor-reported performance measures, not independently established outcomes for every clinical study. For oncology programs, the potential benefit is fewer unusable scans and faster correction of technical problems. Planned automated tumor measurements for 2027 are separate from functions offered in 2026, and image-workflow automation is not the same as an autonomous clinical reading.
Risk-based data management is replacing uniform manual review
A large trial can generate thousands of site records, and inspecting every field with equal intensity is neither economical nor necessarily the best protection for critical endpoints. Veeva’s 2026 Clinical Data Trend Report highlights risk-based review and the coordination of data-management work. Algorithms can prioritize inconsistent entries, missing assessments or abnormal site patterns, freeing staff to evaluate consequential deviations. Sponsors still need to predefine thresholds, establish escalation ownership and retain the ability to reconstruct why a record was cleared or challenged.
Governance requirements are moving into platform purchasing decisions
Advarra’s 2026 work on responsible clinical research AI and FDA E6(R3) guidance place model governance within ordinary trial quality management. Sponsors are examining who owns a model, how training data were selected, how outputs change after updates and which recommendations need physician or data-manager sign-off. On October 7, IQVIA introduced Life Science Models for trial simulation and protocol assessment, reporting early evaluations across 50 trials and 270 endpoints; these remain supplier findings that require context-specific confirmation. Commercial adoption is more credible when technical improvements can be reproduced within an inspectable trial process.
AI-Powered Clinical Trial Management Market Segment Analysis
By Type of AI Solution
Data Management and Analysis
Data Management and Analysis is one of the clearest paid AI solution groups because every study generates queries, monitoring records, safety information and endpoint evidence that must be cleaned and reconciled. The segment is estimated at USD 837 million, or 31% of the global market in 2026, increasing to USD 2.464 billion by 2031. The economic case rests on faster resolution of exceptions without degrading the integrity of the record. Medidata’s data and imaging products are examples of tools supplied inside established clinical workflows; the value of ordinary EDC software without an attributable AI function should not be included in this category.
By Function
Predictive Analytics
Predictive Analytics is applied before and during a study to estimate feasible recruitment, assess protocol burden, monitor dropout and identify sites that need attention. The segment is valued at an estimated USD 783 million in 2026 and USD 2.310 billion by 2031, implying roughly 24.2% annual growth. IQVIA’s October 2026 Life Science Models show the direction of investment in simulated clinical outcomes, while the purchasing decision still depends on calibration against new populations. NLP and Machine Learning support many predictive products, so the functional categories describe the primary purchased capability rather than mutually exclusive algorithm architectures.
By End-User
Pharmaceutical Companies
Pharmaceutical Companies remain the principal contracting end-user group, procuring AI tools across multi-study portfolios and setting standards that CROs and investigative sites must follow. Spending by this group is estimated at USD 1.323 billion in 2026, or 49% of the global market, and USD 3.619 billion by 2031. Large sponsors can evaluate one platform over repeated studies, whereas small biotechnology firms often procure capabilities through CRO or software-service contracts. The practical differentiator is not the number of AI functions advertised but whether clinical, data-management and quality teams can rely on the same controlled source of evidence.
Market Drivers
Protocol complexity and repeated amendments create expensive rework
Trial protocols frequently impose intricate eligibility criteria, visit schedules and endpoint assessments. Translating them into operational systems involves manual interpretation by clinical operations, data management and programming staff. Veeva’s September 2026 Study Builder Agent directly targets that burden. AI can reduce repeated transcription and generate initial study configurations from approved standards, provided every output is checked. This creates a tangible purchasing case because errors during setup propagate to sites and later require costly corrections; improvement must be documented against actual study build and amendment outcomes.
Operational failure during study setup is often discovered far from the initial configuration decision. A visit window encoded incorrectly can affect site schedules, edit checks and data reconciliation for months. Sponsors assessing a build agent therefore need to compare the full release cycle: time to an accepted system, number of corrections after user acceptance testing, and the effort required when the protocol is amended. A fast first draft has limited value if it increases downstream validation work.
Sponsors are seeking more reliable recruitment forecasts
Late enrollment and poor site selection consume clinical budgets and can delay decisions about investigational therapies. Historical screening rates, location-specific patient availability and eligibility rules can be analyzed to make study planning more realistic. NLP may help interpret records and criteria, while predictive models estimate achievable recruitment under different assumptions. The process remains sensitive to missing health data and site-specific access limits. Vendors that demonstrate external validation, transparent inclusion criteria and fair performance across participant groups can support sponsor adoption more convincingly than tools promising automatic patient selection.
Recruitment forecasts can be improved without automating the final eligibility decision. Historical site performance is useful only after adjusting for changes in inclusion criteria, referral patterns and competing studies. Hospitals may also restrict export of patient records, requiring feasibility systems to work with aggregated counts or locally controlled matching. Procurement will favor tools that explain where predicted enrollment could fail and show the cost of activating an additional site before the shortfall becomes irreversible.
Larger clinical data flows justify targeted automation
Remote assessments, wearables, imaging and electronic patient outcomes increase the variety of trial evidence. Manual checks on every record become difficult when data are generated continuously or arrive in different formats. Medidata’s 2026 Imaging and Data Experience releases address defined processing and review tasks rather than replacing clinical judgment. The benefit is strongest where the algorithm reduces repetitive work and returns exceptions for skilled review. Sponsor demand depends on reliable workflow integration, secure handling of identifiable health information and clearly documented confidence in automated flags.
Imaging illustrates the distinction between administrative automation and medical assessment. Detecting a missing sequence, patient-identifier leak or inconsistent follow-up scan can save days without asking the model to determine clinical response. Similar opportunities exist in wearable-data completeness and laboratory reconciliation. Suppliers that expose confidence, error types and the person responsible for final review give data managers something measurable to purchase. Those controls matter more than the quantity of records processed automatically.
Regulators are accepting risk-based technology use within quality systems
The FDA’s September 2025 final E6(R3) GCP guidance supports modern trial approaches with quality-by-design and proportionate oversight principles. Its flexibility can support better targeted data review and technology-enabled monitoring when sponsors maintain appropriate responsibilities and documentation. The FDA’s April 2026 real-time trial initiative similarly signals interest in faster evidence flows. These are not blanket authorizations for autonomous AI decisions; they establish a context in which validated systems can contribute to operational improvements without abandoning participant protection or scientific integrity.
Regulatory flexibility still operates within a documented quality system. Sponsors must decide which processes are critical to safety or endpoint reliability, validate the technology proportionately and preserve evidence of oversight. Standardized protocol formats and data exchange rules can make AI implementations less bespoke, but they also reveal inconsistent terminology across sponsors and sites. Vendors with controlled testing, release management and retrievable model versions will face fewer obstacles in global studies than those relying on opaque black-box changes.
Clinical software vendors are consolidating functionality
AI adoption can be accelerated when sponsors do not have to integrate numerous stand-alone tools into their trial environments. Medidata Plus and Veeva’s study-configuration developments illustrate product strategies built around existing platform relationships. IQVIA’s October 2026 adoption of Veeva operations applications highlights demand for shared technology standards between sponsors and outsourced service providers. Consolidation reduces interfaces and procurement complexity for some customers, although it can raise switching costs. The economic benefit arises from connected operations rather than the number of AI features advertised.
The integrated-platform strategy does not end competition from specialists. A recruitment provider may have superior hospital access, while an imaging vendor may offer stronger modality-specific checks than the incumbent trial suite. Sponsors will weigh those gains against integration obligations and the risk of fragmented data lineage. The resulting market is likely to support a small set of foundational platforms with a narrower group of validated, interoperable applications rather than a separate AI tool for every clinical task.
Market Restraints
Validation and inspection readiness limit rapid model change
Trial software operates under controlled procedures intended to protect participants and preserve evidence quality. A generative model that changes output after an update can create uncertainty about whether two sites or study periods were treated consistently. Sponsors must consider version control, validation records, documented overrides and retrievable decision histories. These requirements lengthen implementation and may discourage use of unproven features in pivotal trials. A high model benchmark score is not sufficient when critical outputs cannot be reproduced or linked to a qualified reviewer.
Validation plans must also anticipate changes the supplier controls. A new model version can alter summaries or alert rates without any modification to the underlying clinical record. Change notices, regression testing against representative studies and an agreed rollback procedure should be part of service terms. This is particularly important in long-running studies where a different output standard midway through enrollment could compromise consistency. Organizations with weak internal software validation capacity may defer deployment even when the tool performs well in a pilot.
Patient records remain fragmented and difficult to standardize
Eligibility and monitoring tools depend on electronic health records, imaging, lab results and site-entered observations that differ in format and completeness. Local workflows, coding conventions and consent restrictions complicate data transfer. Models trained on one source may perform poorly elsewhere, particularly for rare diseases or underrepresented patient populations. The cost of mapping records, resolving duplicates and managing cross-border transfers can offset some automation savings. Trial sponsors must confirm whether a vendor can operate within the available evidence perimeter rather than assuming unified patient data.
Record-matching difficulties are especially consequential for eligibility screening. A language model may identify a diagnosis but fail to distinguish a ruled-out condition from an active disease, or mistake historical treatment for current therapy. Hospitals also differ in how diagnoses, adverse events and laboratory units are coded. Clinically supervised sampling of errors across participating sites is therefore essential. Suppliers whose performance depends on unrestricted access to identifiable records may not be able to scale across countries with different privacy requirements.
Algorithms can introduce bias into enrollment and surveillance
Historic trial datasets may underrepresent older adults, minority populations, rural sites or particular disease severities. An enrollment model based on those records can perpetuate uneven recruitment if its recommendations are not reviewed. In monitoring, false-positive anomaly alerts may also burden already overstretched sites. Teams need performance evaluation by relevant population and site characteristics, with documented procedures for correcting inequitable or clinically implausible recommendations. These safeguards require expertise and ongoing measurement, limiting the case for unattended automation.
Algorithmic fairness requires measurement rather than assurances. If a model repeatedly suggests high-enrolling urban sites, it may miss patients served by smaller rural centers and compound existing representation problems. Sponsors need to examine which populations were represented in training and validation datasets and whether predicted eligibility agrees with clinician assessment across subgroups. Extra monitoring can create operational cost, but it is preferable to screening processes that quietly exclude people for reasons unrelated to the protocol.
Integration costs and contractual responsibilities remain unresolved
A study can involve separate vendors for EDC, CTMS, imaging, patient outcomes, randomization and data hosting. Adding AI may require new agreements covering access, processing, privacy, audit evidence and incident response. CROs and sponsors can disagree about ownership of validation tasks or model outputs. Enterprises may favor broad platform contracts, but a switch can disrupt ongoing multi-year studies. Smaller biopharmaceutical companies face more acute budget constraints and may be reluctant to purchase an AI layer whose productivity gains are difficult to isolate.
Contract boundaries become particularly visible during inspection. A sponsor may assume the CRO has tested a prediction service while the CRO expects the software vendor to supply that evidence. Neither assumption resolves responsibility for deviations or missing audit trails. Agreements need named owners for data access, model maintenance, incident response and validated configurations. Vendor consolidation can simplify these interfaces, but switching an active trial to another platform may require substantial migration and comparability work.
Operational gains do not automatically establish better trial outcomes
Faster screening reports, fewer data queries or improved image-processing times are useful operational measures, but they do not directly prove increased trial success or better participant outcomes. Vendor case studies may depend on a particular therapeutic area, technical configuration or early-adopter team. Sponsors require controlled comparisons and evidence that speed improvements do not degrade endpoint reliability. Discrepancies between performance claims and daily site experience can slow purchasing, particularly when models add another layer of alerts rather than removing work.
Buyers are beginning to separate efficiency metrics from clinical efficacy. Reducing the number of data queries is meaningful only if critical data remain accurate and missingness is not concealed by automated closure. Similarly, higher recruitment-screening throughput matters only when suitable participants enter and remain in the study. Commercial contracts may increasingly reference accepted build time, query aging, avoidable imaging rework and site burden. Those measures encourage investment in products that improve completed work rather than create impressive but unusable dashboards.
Regional Outlook
North America: sponsor concentration and mature research technology
North America leads current purchasing, reflecting the concentration of pharmaceutical sponsors, CRO operations, established trial-software suppliers and research centers in the United States. Regional revenue is estimated at USD 1.215 billion in 2026, representing 45% of the global market, and USD 3.080 billion in 2031, or 40%. This corresponds to an implied 20.5% regional CAGR across the five-year forecast. The United States accounts for most enterprise procurement, while Canada has a significant role in multicenter studies and specialist trial services. The region benefits from sophisticated electronic records, mature sponsor quality systems and a large installed base of clinical operations platforms.
The pace of procurement remains constrained by validation and information access. FDA E6(R3) and real-time trial initiatives support proportionate, evidence-based technology adoption, but trial sponsors retain accountability. North American leaders have an advantage when they can demonstrate performance across several studies without requiring each clinical program to rebuild its integrations. Connected environments can shorten onboarding, yet a specialist may still win if its data-quality or recruitment capability is demonstrably stronger.
Asia Pacific: trial execution scale and regional implementation growth
Asia Pacific is projected to be the fastest-growing regional market, rising from USD 594 million in 2026, or 22% of the worldwide market, to USD 2.156 billion by 2031, representing 28%. The resulting implied CAGR is approximately 29.4%, outpacing North America. China, Japan, South Korea and Australia support extensive clinical research programs, while Indian biotechnology and outsourced-development capacity create additional demand for study planning and data review tools. The region is not a single purchasing market: sponsor presence, site digitization, clinical research regulations and language requirements differ considerably.
A vendor expanding across the region must adapt eligibility matching to local data conventions, support compliant transfers between trial sites and sponsors, and offer implementation assistance to research teams with uneven technology resources. Growth prospects are strongest where a global study platform can connect to local investigators without replacing their established systems. Rising trial activity alone does not guarantee AI subscriptions; the conversion depends on funded studies, clinical evidence, usable integrations and governance that satisfies both local and multinational sponsors.
Competitive Landscape
Medidata, Veeva and Oracle occupy influential positions because they supply systems of record for clinical data and operations, creating natural distribution for AI modules. Medidata Plus links functions across its portfolio; Veeva’s Study Builder Agent illustrates the movement toward controlled protocol-to-system configuration; Oracle has established clinical research applications. IQVIA combines CRO delivery with analytics and software partnerships. None of these models is directly comparable with a specialist AI licence, and there is insufficient public evidence to assign company-level shares of strictly attributable AI management revenue.
Specialist vendors compete where the value of an application can be isolated: Saama in clinical data intelligence, Unlearn in digitally augmented study design, AiCure in treatment-adherence monitoring, Clinerion and TriNetX in cohort finding, and ArisGlobal in safety workflows. Advarra and Medable address other aspects of the research operating environment. Market maps must reflect ownership: Medidata is part of Dassault Systèmes, and Thermo Fisher completed its purchase of Clario, which incorporates the earlier Bioclinica business, on March 24, 2026. That acquisition should not be confused with a fresh sale of clinical AI software.
When purchasers test rival solutions, the decisive criteria are often mundane: how a system acquires permitted records, whether its output can be reproduced, how failures reach a qualified reviewer and how upgrades are controlled during an active protocol. Bundling can lower procurement friction while reducing a sponsor’s negotiating leverage. A supplier with stronger evidence in a narrow workflow can still retain a role if it integrates cleanly with the chosen trial platform.
Recent Developments
October 2026: Medidata reports updated AI imaging performance
At ESMO 2026, Medidata reported greater than 97% anatomy-verification accuracy and 32% faster protected-health-information redaction in its AI-assisted imaging workflow. The results are supplier-reported and concern imaging process controls; tumor measurement functions described for 2027 are not counted as currently launched products.
October 2026: QVIA expands use of Veeva clinical applications
IQVIA selected Veeva CTMS, eTMF, Study Startup and Site Connect as enterprise-standard applications. The announcement builds on an earlier EDC partnership and signals demand for connected trial operations, without identifying the share of contract revenue attributable to artificial intelligence.
October 2026: IQVIA introduces Life Science Models for clinical prediction
IQVIA launched models for trial simulations and protocol optimization built with domain data and external computing infrastructure. An initial internal evaluation covered 50 trials and 270 endpoints. These results are useful evidence of product direction but are not a validated general success rate across clinical trial types.
September 2026: Veeva announces Study Builder Agent
Veeva described an agent that configures EDC forms, visits and data-quality checks from protocols and customer standards. The company planned availability for early adopters in December 2026; the announcement should not be treated as general commercial deployment in September.
July 2026: Medidata launches Medidata Plus
Medidata introduced an AI-native layer for using common intelligence capabilities across its clinical portfolio. The commercial positioning favors platform-level access and consistent data context over separate, disconnected AI point solutions.
May 2026: Medidata unveils enhanced clinical trial imaging
Medidata presented upgraded AI-supported imaging quality-control and redaction features at ASCO 2026. The release addresses imaging data processing and study operations; it does not establish authorization for independent automated cancer diagnosis.
Market Outlook
The next competitive stage will be decided by evidence of completed operational work. Sponsors want trial configurations accepted sooner, recruitment forecasts that improve enrollment decisions, imaging files that clear quality checks promptly, and risks presented while action is still possible. Higher model accuracy is useful but insufficient unless systems produce reproducible, accountable results. Longitudinal studies will favor tools with a controlled update path and durable data records, particularly where models influence endpoint or safety decisions.
Integrated providers can expand across portfolios by embedding AI into the established clinical record, while specialists may earn a premium for stronger performance in a defined trial task. Regulatory modernization and structured-protocol initiatives create opportunities for scaling, but neither eliminates the cost of validation. Sustainable adoption through 2031 will be governed by the relationship between measurable operating gains, the work required to prove them and a sponsor’s obligation to protect participants and preserve credible evidence.
AI-Powered Clinical Trial Management Market Scope:
| Report Metric | Details |
|---|---|
| Total Market Size in 2026 | USD 2.7 billion |
| Total Market Size in 2031 | USD 7.7 billion |
| Forecast Unit | Billion |
| Growth Rate | 23.1% |
| Study Period | 2021 to 2031 |
| Historical Data | 2021 to 2024 |
| Base Year | 2025 |
| Forecast Period | 2026 – 2031 |
| Segmentation | AI solution, Function, End-User, Geography |
| Companies |
|
Market Segmentation
By Type of AI Solution
Clinical Trial Planning and Design
Patient Recruitment and Enrollment
Data Management and Analysis
Monitoring and Oversight
Safety and Pharmacovigilance
By Function
Predictive Analytics
Natural Language Processing (NLP)
Machine Learning
Robotic Process Automation (RPA)
Image and Signal Processing
By End-User
Pharmaceutical Companies
Contract Research Organizations (CROs)
Academic and Research Institutions
Biotechnology Companies
Medical Device Manufacturers
By Geography
North America
United States
Canada
Mexico
South America
Brazil
Argentina
Others
Europe
Germany
United Kingdom
France
Italy
Spain
Others
Middle East and Africa
Saudi Arabia
UAE
Others
Asia Pacific
China
India
Japan
South Korea
Indonesia
Thailand
Taiwan
Others
Table of Contents
1. EXECUTIVE SUMMARY
1.1. Key Findings
1.2. CXO Perspective
2. MARKET SNAPSHOT
2.1. Market Definition and Scope
2.2. Global Market Size and Forecast
2.3. Segmentation and Regional Overview
3. BUSINESS LANDSCAPE
3.1. Market Drivers
3.1.1. Protocol complexity and repeated amendments create expensive rework
3.1.2. Sponsors are seeking more reliable recruitment forecasts
3.1.3. Larger clinical data flows justify targeted automation
3.1.4. Regulators are accepting risk-based technology use within quality systems
3.1.5. Clinical software vendors are consolidating functionality
3.2. Market Restraints
3.2.1. Validation and inspection readiness limit rapid model change
3.2.2. Patient records remain fragmented and difficult to standardize
3.2.3. Algorithms can introduce bias into enrollment and surveillance
3.2.4. Integration costs and contractual responsibilities remain unresolved
3.2.5. Operational gains do not automatically establish better trial outcomes
3.3. Market Opportunities
3.4. Porter’s Five Forces Analysis
3.5. Industry Value Chain Analysis
3.6. Policies and Regulations
3.7. Strategic Recommendations
4. TECHNOLOGICAL OUTLOOK
4.1. Current Technology Base
4.2. Emerging Architectures and Deployment Models
4.3. Technology Risks and Governance
5. AI-POWERED CLINICAL TRIAL MANAGEMENT MARKET BY TYPE OF AI SOLUTION
5.1. Introduction
5.2. Clinical Trial Planning and Design
5.3. Patient Recruitment and Enrollment
5.4. Data Management and Analysis
5.5. Monitoring and Oversight
5.6. Safety and Pharmacovigilance
6. AI-POWERED CLINICAL TRIAL MANAGEMENT MARKET BY FUNCTION
6.1. Introduction
6.2. Predictive Analytics
6.3. Natural Language Processing (NLP)
6.4. Machine Learning
6.5. Robotic Process Automation (RPA)
6.6. Image and Signal Processing
7. AI-POWERED CLINICAL TRIAL MANAGEMENT MARKET BY END-USER
7.1. Introduction
7.2. Pharmaceutical Companies
7.3. Contract Research Organizations (CROs)
7.4. Academic and Research Institutions
7.5. Biotechnology Companies
7.6. Medical Device Manufacturers
8. AI-POWERED CLINICAL TRIAL MANAGEMENT MARKET BY GEOGRAPHY
8.1. Introduction
8.2. North America
8.2.1. By Type of AI Solution
8.2.2. By Function
8.2.3. By End-User
8.2.4. By Country
8.2.4.1. United States
8.2.4.2. Canada
8.2.4.3. Mexico
8.3. South America
8.3.1. By Type of AI Solution
8.3.2. By Function
8.3.3. By End-User
8.3.4. By Country
8.3.4.1. Brazil
8.3.4.2. Argentina
8.3.4.3. Others
8.4. Europe
8.4.1. By Type of AI Solution
8.4.2. By Function
8.4.3. By End-User
8.4.4. By Country
8.4.4.1. Germany
8.4.4.2. United Kingdom
8.4.4.3. France
8.4.4.4. Italy
8.4.4.5. Spain
8.4.4.6. Others
8.5. Middle East and Africa
8.5.1. By Type of AI Solution
8.5.2. By Function
8.5.3. By End-User
8.5.4. By Country
8.5.4.1. Saudi Arabia
8.5.4.2. UAE
8.5.4.4. Others
8.6. Asia Pacific
8.6.1. By Type of AI Solution
8.6.2. By Function
8.6.3. By End-User
8.6.4. By Country
8.6.4.1. China
8.6.4.2. India
8.6.4.3. Japan
8.6.4.4. South Korea
8.6.4.6. Indonesia
8.6.4.7. Thailand
8.6.4.8. Taiwan
8.6.4.9. Others
9. COMPETITIVE ENVIRONMENT AND ANALYSIS
9.1. Major Players and Strategy Analysis
9.2. Market Share Analysis
9.3. Mergers, Acquisitions, Agreements and Collaborations
9.4. Competitive Dashboard
10. COMPANY PROFILES
10.1. Medidata Solutions (Dassault Systèmes)
10.2. Veeva Systems Inc.
10.3. IQVIA Holdings Inc.
10.4. Oracle Corporation
10.5. Saama Technologies
10.6. Medable Inc.
10.7. ArisGlobal LLC
10.8. Advarra Inc.
10.9. Clinerion Ltd.
10.10. Thermo Fisher Scientific Inc. (Clario)
10.11. Unlearn.AI Inc.
10.12. TriNetX LLC
11. APPENDIX
11.1. Currency
11.2. Assumptions
11.3. Base and Forecast Years Timeline
11.4. Key Benefits for Stakeholders
11.5. Research Methodology
11.6. Abbreviations
Navigate
Trusted by the world's leading organizations











